Related Experiment Video
Updated: Jan 30, 2026
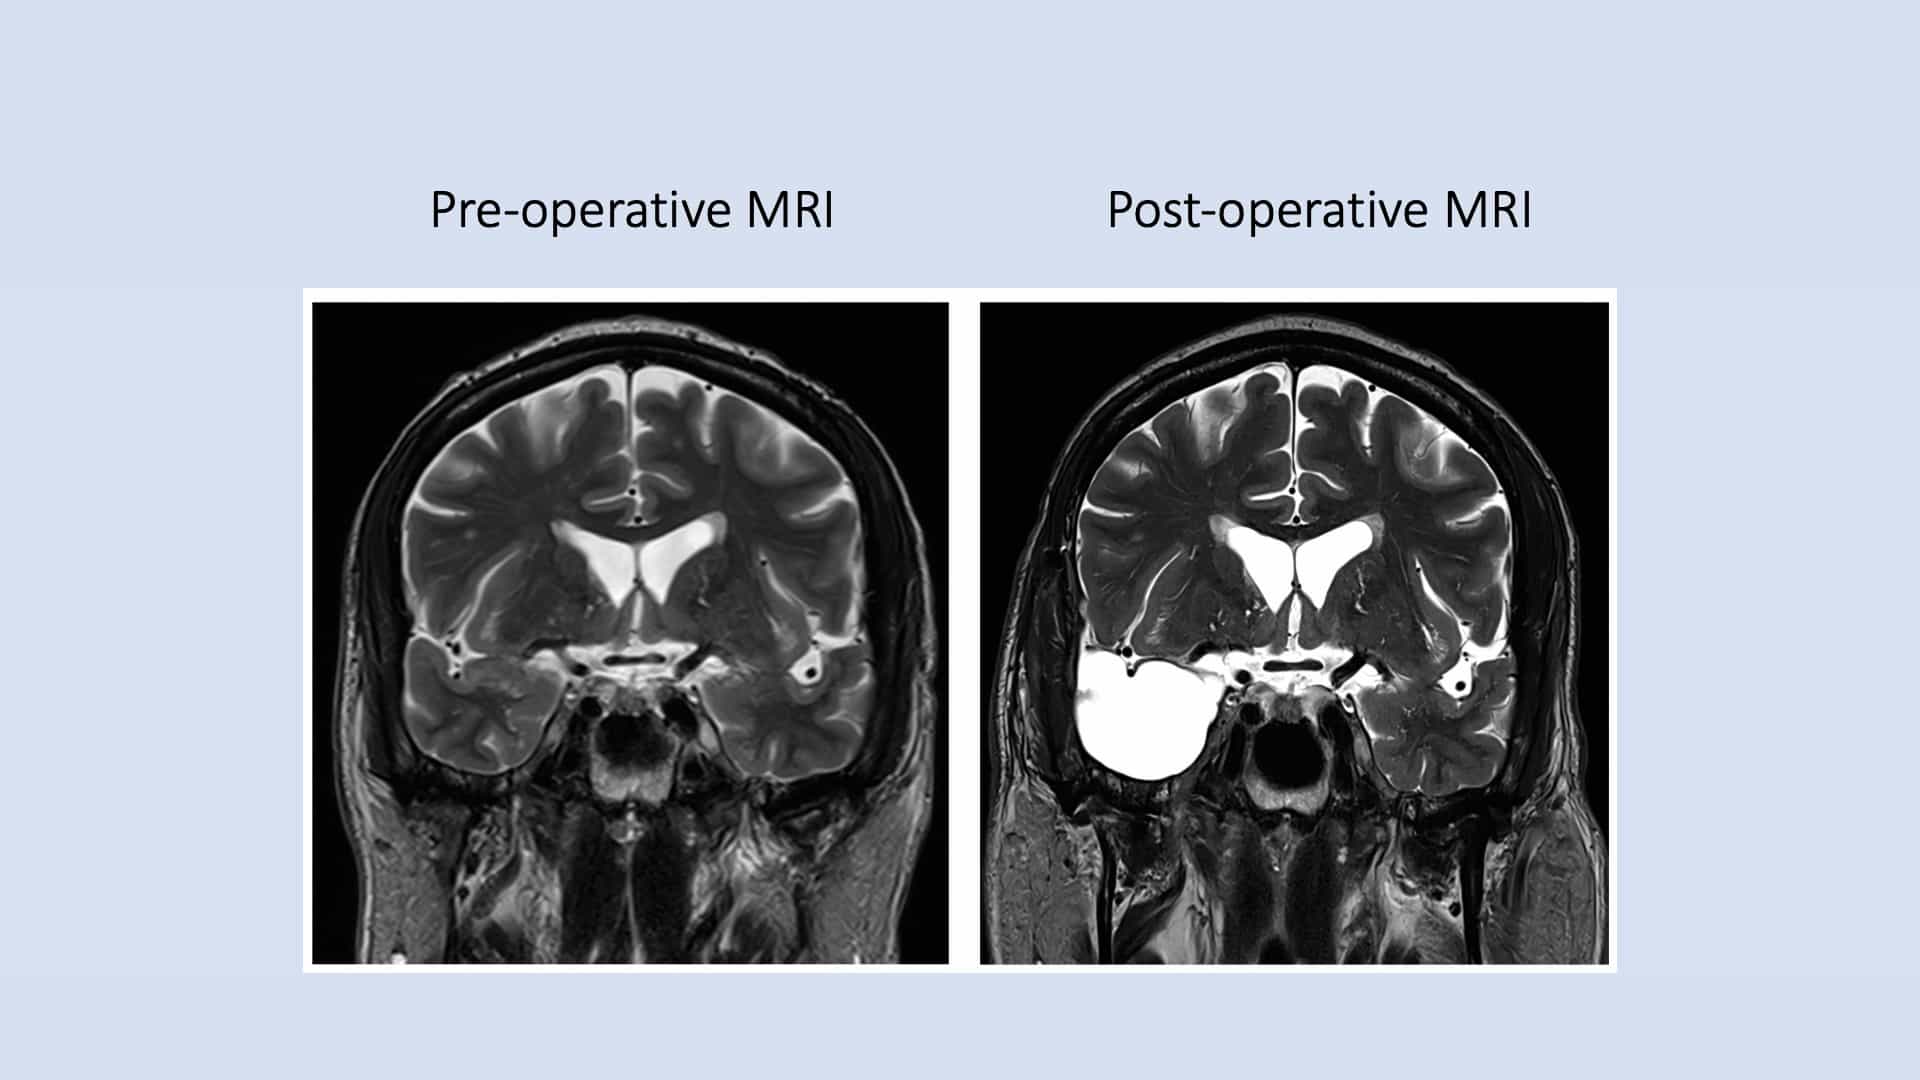

Anteromesial Temporal Lobectomy for Medically Intractable Temporal Lobe Epilepsy: An Operative Study
Published on: August 15, 2025
Is additional mesial temporal resection necessary for intractable epilepsy with cavernous malformations in the
Yumi Kashida1, Naotaka Usui2, Kazumi Matsuda2
1Department of Neurosurgery, Graduate School of Medical and Dental Sciences, Kagoshima University, Kagoshima, Japan; National Epilepsy Center, Shizuoka Institute of Epilepsy and Neurological Disorders, Shizuoka, Japan.

Purpose:
Cavernous malformation (CM) in the temporal neocortex causes intractable epilepsy. Whether to resect additional mesial temporal structures in addition to the lesionectomy is a still controversial issue. To clarify the need for the procedure, we retrospectively analyzed pre- and postoperative clinical data of patients with surgically removed CM.
Subjects And Methods:
We included data from 18 patients with CM in the temporal neocortex who presented with intractable epilepsy. Eleven patients of our early series were treated with extended resection, i.e., lesionectomy and the resection of additional mesial temporal structures. Seven patients underwent lesionectomy, i.e., removal of the CM and of hemosiderin-stained surrounding brain tissue. Pathological assessments of the resected hippocampus were performed. Chronic intracranial electroencephalography (EEG) recordings were obtained in 6 patients. We performed perioperative neuropsychological assessments in all patients.
Results:
The seizure outcome was recorded as Engel class I in 17 patients (94.4%); Ia = 12 (66.7%) Ib = 2 (11.1%), Ic = 1 (5.6%), Id = 2 (11.1%), and class IIb in one patient (5.6%). Adding resection of the mesial temporal structures to lesionectomy did not alter the seizure outcome. Pathology of hippocampus revealed limited neuronal loss in CA4. Ictal onsets in the ipsilateral lateral cortex were detected in all 6 patients who underwent intracranial EEG. In 4 patients each, we also detected ictal onsets from the ipsilateral mesial temporal structures and from the contralateral temporal lobe. Postoperatively, in the patients where their CM was located in the language-dominant hemisphere (n = 10), the full-scale intelligence quotient (IQ) and the performance IQ increased (p < 0.05), whereas the verbal memory (WMS-R) deteriorated in two of 5 patients.
Conclusion:
Excellent seizure outcomes were obtained even the lesionectomy alone. To confirm appropriate surgical strategy for lateral temporal CM with intractable epilepsy, further studies in large sample size are needed.
More Related Videos

Related Concept Videos
 01:10
¹H NMR of Labile Protons: Temporal Resolution
The –OH proton in alcohols typically appears in the range of δ 2 to 5 ppm but can vary depending on the specific...
 01:19
Assessing Body Temperature - Temporal Artery
Step 1: Perform hand hygiene and don a fresh pair of gloves to prevent cross-infection and ensure patient safety.
Step 2: Explain the procedure to the patient to establish trust. Clear communication establishes trust with the patient, ensures they understand what to expect, promotes cooperation, and enhances comfort during the procedure.
Step 3: Assess the patient's...
 00:52
¹H NMR of Conformationally Flexible Molecules: Temporal Resolution
 01:27
Conjugate Addition (1,4-Addition) vs Direct Addition (1,2-Addition)
Conjugate addition results in a thermodynamically stable product. The reaction retains the stronger C=O bond at the expense of the weaker C=C π bond. The process is slow as the β carbon is less electrophilic than the carbonyl carbon.
Direct addition products are...
 01:08
Conjugate Addition of Enolates: Michael Addition
 01:24
Epilepsy and Seizures: Overview
Various factors can trigger epilepsy, including genetic factors, brain damage, metabolic causes, and unknown etiology. Diagnosis of epilepsy involves electroencephalography (EEG), which...