Related Experiment Video
Updated: Jan 30, 2026
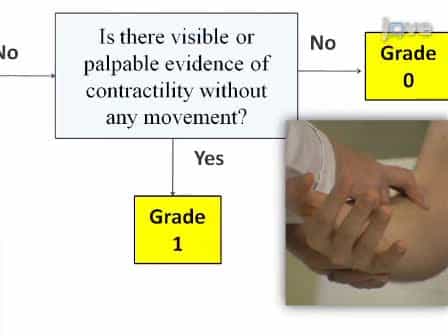

Manual Muscle Testing: A Method of Measuring Extremity Muscle Strength Applied to Critically Ill Patients
Published on: April 12, 2011
Oxidative stress, caloric intake and outcomes of critically ill patients
Yaseen Arabi1, Dunia Jawdat2, Abderrezak Bouchama3
1College of Medicine, King Saud bin Abdulaziz University for Health Sciences, King Abdullah International Medical Research Center, Intensive Care Department, King Abdulaziz Medical City, Riyadh, Saudi Arabia.

Insights
Critically ill patients exhibit distinct oxidative stress patterns. Permissive underfeeding may protect against kidney injury, but its effect on mortality varies by oxidative stress profile.
Area of Science:
- Critical care medicine
- Biochemistry
- Nephrology
Background:
- Investigating oxidative stress patterns in critically ill patients is crucial for understanding disease progression.
- Oxidative stress markers, including total antioxidant capacity (TAC), protein carbonyls, and 8-hydroxy-7,8-dihydro-2'-deoxyguanosine (8-OHdG), were examined.
- The study explored the association between oxidative stress, caloric intake, and patient outcomes in the ICU.
Purpose of the Study:
- To identify distinct patterns of oxidative stress in critically ill patients.
- To explore the relationship between these oxidative stress patterns and patient outcomes, specifically renal replacement therapy and mortality.
- To assess the impact of permissive underfeeding on outcomes within different oxidative stress clusters.
Main Methods:
- A sub-study of the PermiT trial included ICU patients with expected stays of ≥14 days.
- Serum samples were analyzed for TAC, protein carbonyls, and 8-OHdG on multiple days.
- Principal component analysis (PCA) and hierarchical cluster analysis (HCA) were used to categorize patients based on oxidative stress profiles.
Main Results:
- PCA identified two components explaining 79% of variance; HCA revealed three distinct oxidative stress clusters.
- Cluster 1 (78.6%) had the lowest oxidative stress markers, while Cluster 3 (5.4%) had the highest protein carbonyl levels.
- Incident renal replacement therapy was significantly higher in Cluster 2 (50.0%) compared to Clusters 1 (9.5%) and 3 (33.3%). Permissive underfeeding was linked to lower incident renal replacement therapy (aOR 0.02).
Conclusions:
- Distinct oxidative stress patterns exist in critically ill patients, influencing outcomes.
- Incident renal replacement therapy rates varied significantly across the identified oxidative stress clusters.
- Permissive underfeeding demonstrated a potential protective effect on incident renal replacement therapy, possibly modulated by individual oxidative stress patterns.
Background:
The aim of this study was to investigate the patterns of oxidative stress in critically ill patients and the association with caloric intake and outcomes.
Methods:
In this pre-planned sub-study of the PermiT (Permissive Underfeeding versus Target Enteral Feeding in Adult Critically Ill Patients Trial- ISRCTN68144998), we included patients expected to stay in the ICU for ≥14 days. Serum samples were collected on days 1, 3, 5, 7 and 14 of enrollment. We measured total anti-oxidant capacity (TAC), protein carbonyl concentration (a measure of protein oxidation) and 8-hydroxy-7,8-dihydro-2'-deoxyguanosine (8-OHdG) (a measure of DNA oxidation). We used principal component analysis (PCA) and hierarchical cluster analysis (HCA) to group patients according to oxidative stress.
Results:
Principal component analysis identified 2 components that were responsible for 79% of the total variance, and cluster analysis grouped patients in three statistically distinct clusters. Majority of patients 78.6% (44/55) were included in cluster 1 with lowest TAC, protein carbonyl and 8-OHdG levels and cluster 2 which accounted for 16.1% (9/55) of patients had the highest levels of TAC and intermediate levels of protein carbonyl levels. Cluster 3 patients 5.4% (3/56) had the highest protein carbonyl levels. Incident renal replacement therapy was highest in cluster 2 (4/8, 50.0%), compared to cluster 1 (4/42, 9.5%) and cluster 3 (1/3, 33.3%, p 0.01). When adjusted to oxidative stress cluster membership, permissive underfeeding was not associated with 90-day mortality (adjusted odds ratio, aOR 1.37, 95% CI 0.36, 5.25, p 0.64) but was associated significantly with lower incident renal replacement therapy (aOR 0.02, 95% CI < 0.001, 0.57, p 0.02).
Conclusions:
There are different distinct patterns of oxidative stress in critically ill patients. Incident renal replacement therapy was different among the three clusters. Our data suggest a protective effect of permissive underfeeding on incident renal replacement therapy that may differ by clusters of oxidative stress.
More Related Videos

Related Concept Videos
 03:14
Oxidation Numbers
 01:25
Regulation of Water Intake
 01:30
Regulation of Food Intake
 01:16
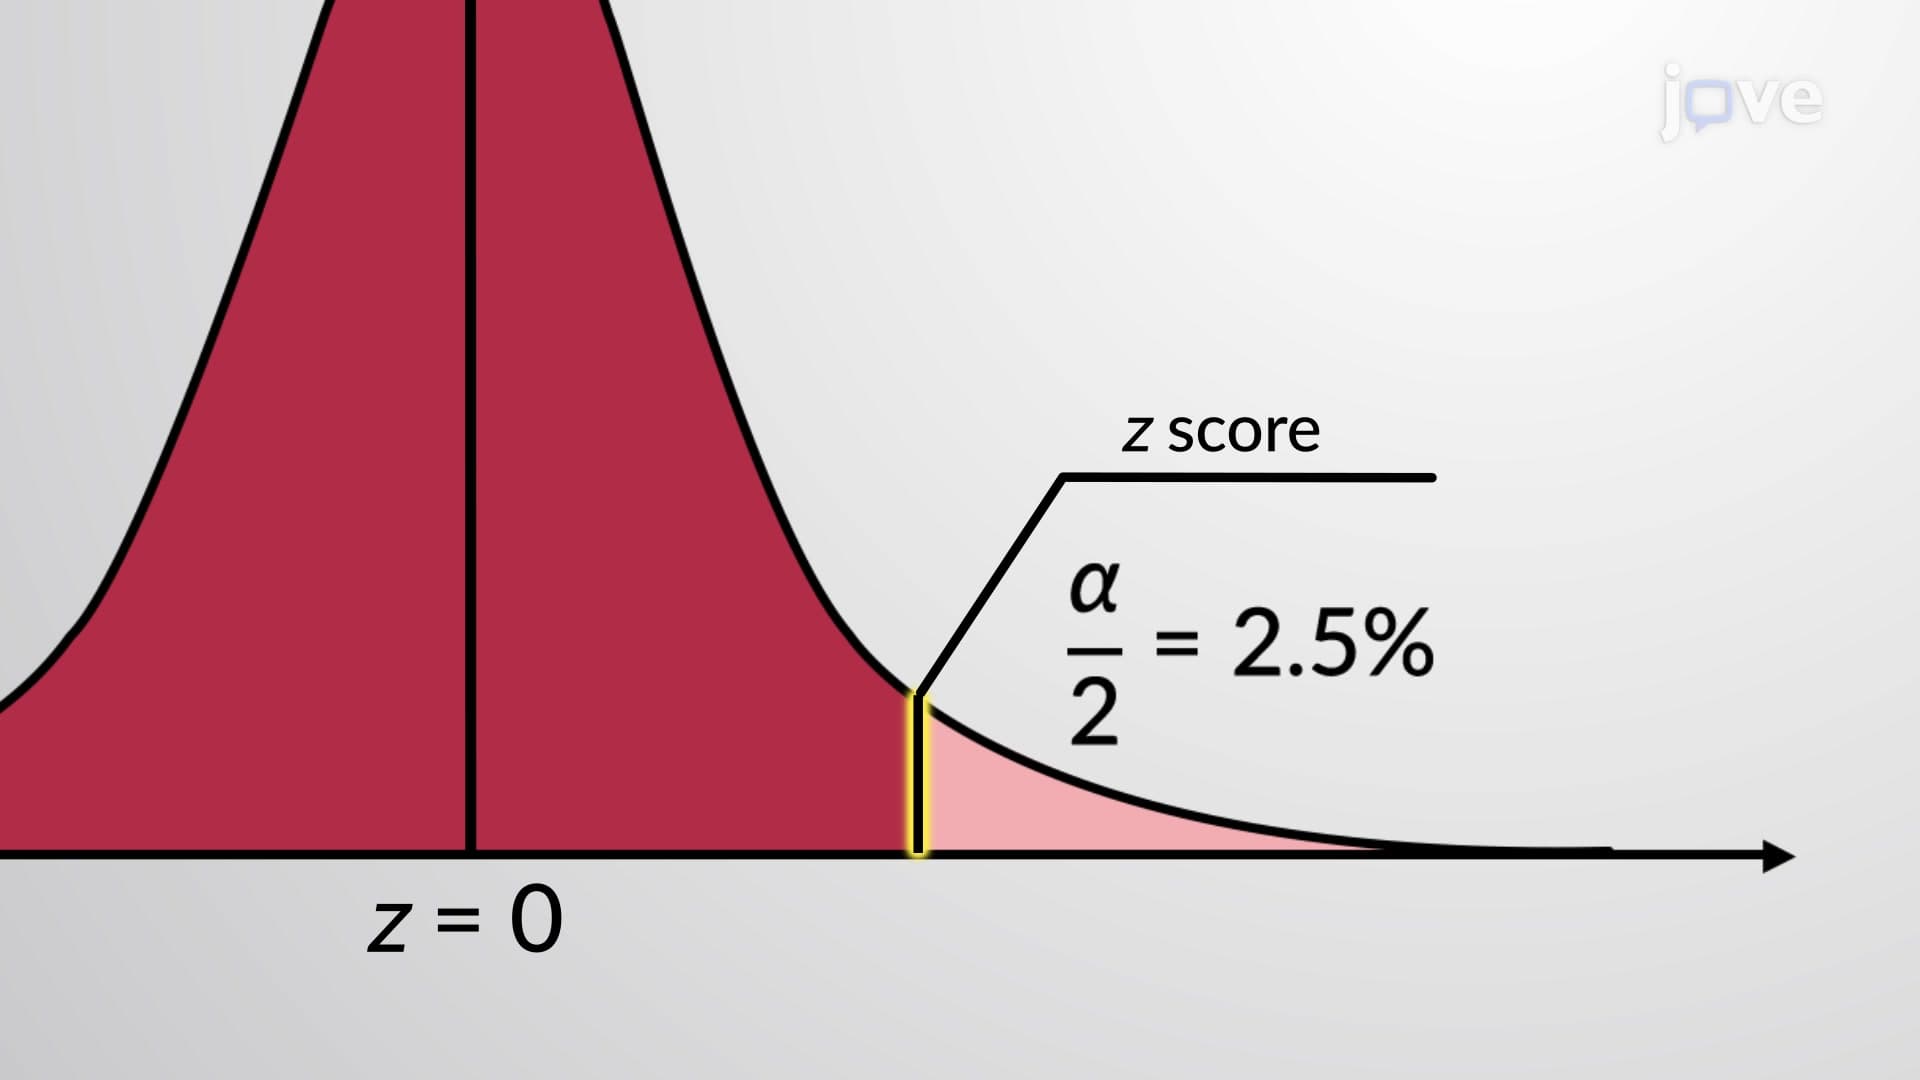
Critical Region, Critical Values and Significance Level
In hypothesis testing, a sample statistic is converted to a test statistic using z, t, or chi-square distribution. A critical region is an area under the curve in probability distributions demarcated by the critical value. When the test statistic falls in this region, it suggests that the null hypothesis must be rejected. As this region contains all those values of the...
 02:24
Predicting Reaction Outcomes
 01:31
Critical Values