Related Experiment Video
Updated: Jan 30, 2026

Project-Based Learning Guidelines for Health Sciences Students: An Analysis with Data Mining and Qualitative Techniques
Published on: December 9, 2022
What, why and how do health systems learn from one another? Insights from eight low- and middle-income country case
Sophie Witter1, Ian Anderson2, Peter Annear3
1ReBUILD and Institute for Global Health and Development, Queen Margaret University Edinburgh, Musselburgh, EH21 2UU, United Kingdom. switter@qmu.ac.uk.

Background:
All health systems struggle to meet health needs within constrained resources. This is especially true for low-income countries. It is critical that they can learn from wider contexts in order to improve their performance. This article examines policy transfer and evidence use linked to it in low- and middle-income settings. The objective was to inform international investments in improved learning across health systems.
Methods:
The article uses a comparative case study design, drawing on case studies conducted in Bangladesh, Burkina Faso, Cambodia, Ethiopia, Georgia, Nepal, Rwanda and Solomon Islands. One or two recent health system reforms were selected in each case and 148 key informants were interviewed in total, using a semi-structured tool focused on different stages of the policy cycle. Interviewees were selected for their engagement in the policy process and represented political, technical, development partner, non-governmental, academic and civil society constituencies. Data analysis used a framework approach, allowing for new themes to be developed inductively, focusing initially on each case and then on patterns across cases.
Results:
The selected policies demonstrated a range of influences of externally imposed, co-produced and home-grown solutions on the development of initial policy ideas. Eventual uptake of policy was strongly driven in most settings by local political economic considerations. Policy development post-adoption demonstrated some strong internal review, monitoring and sharing processes but there is a more contested view of the role of evaluation. In many cases, learning was facilitated by direct personal relationships with local development partner staff. While barriers and facilitators to evidence use included supply and demand factors, the most influential facilitators were incentives and capacity to use evidence.
Conclusions:
These findings emphasise the agency of local actors and the importance of developing national and sub-national institutions for gathering, filtering and sharing evidence. Developing demand for and capacity to use evidence appears more important than augmenting supply of evidence, although specific gaps in supply were identified. The findings also highlight the importance of the local political economy in setting parameters within which evidence is considered and the need for a conceptual framework for health system learning.
Related Concept Videos
 01:14
Avoidance Learning and Learned Helplessness
Avoidance learning occurs when an organism learns that a specific behavior can prevent an unpleasant outcome. For example, a student who receives a bad grade may start studying harder to avoid future poor grades. This behavior persists even when the negative outcome is no longer present. Avoidance learning is powerful because it maintains behavior in the absence of the...
 01:21
Health Literacy
 01:18
Second Order systems II
 01:21
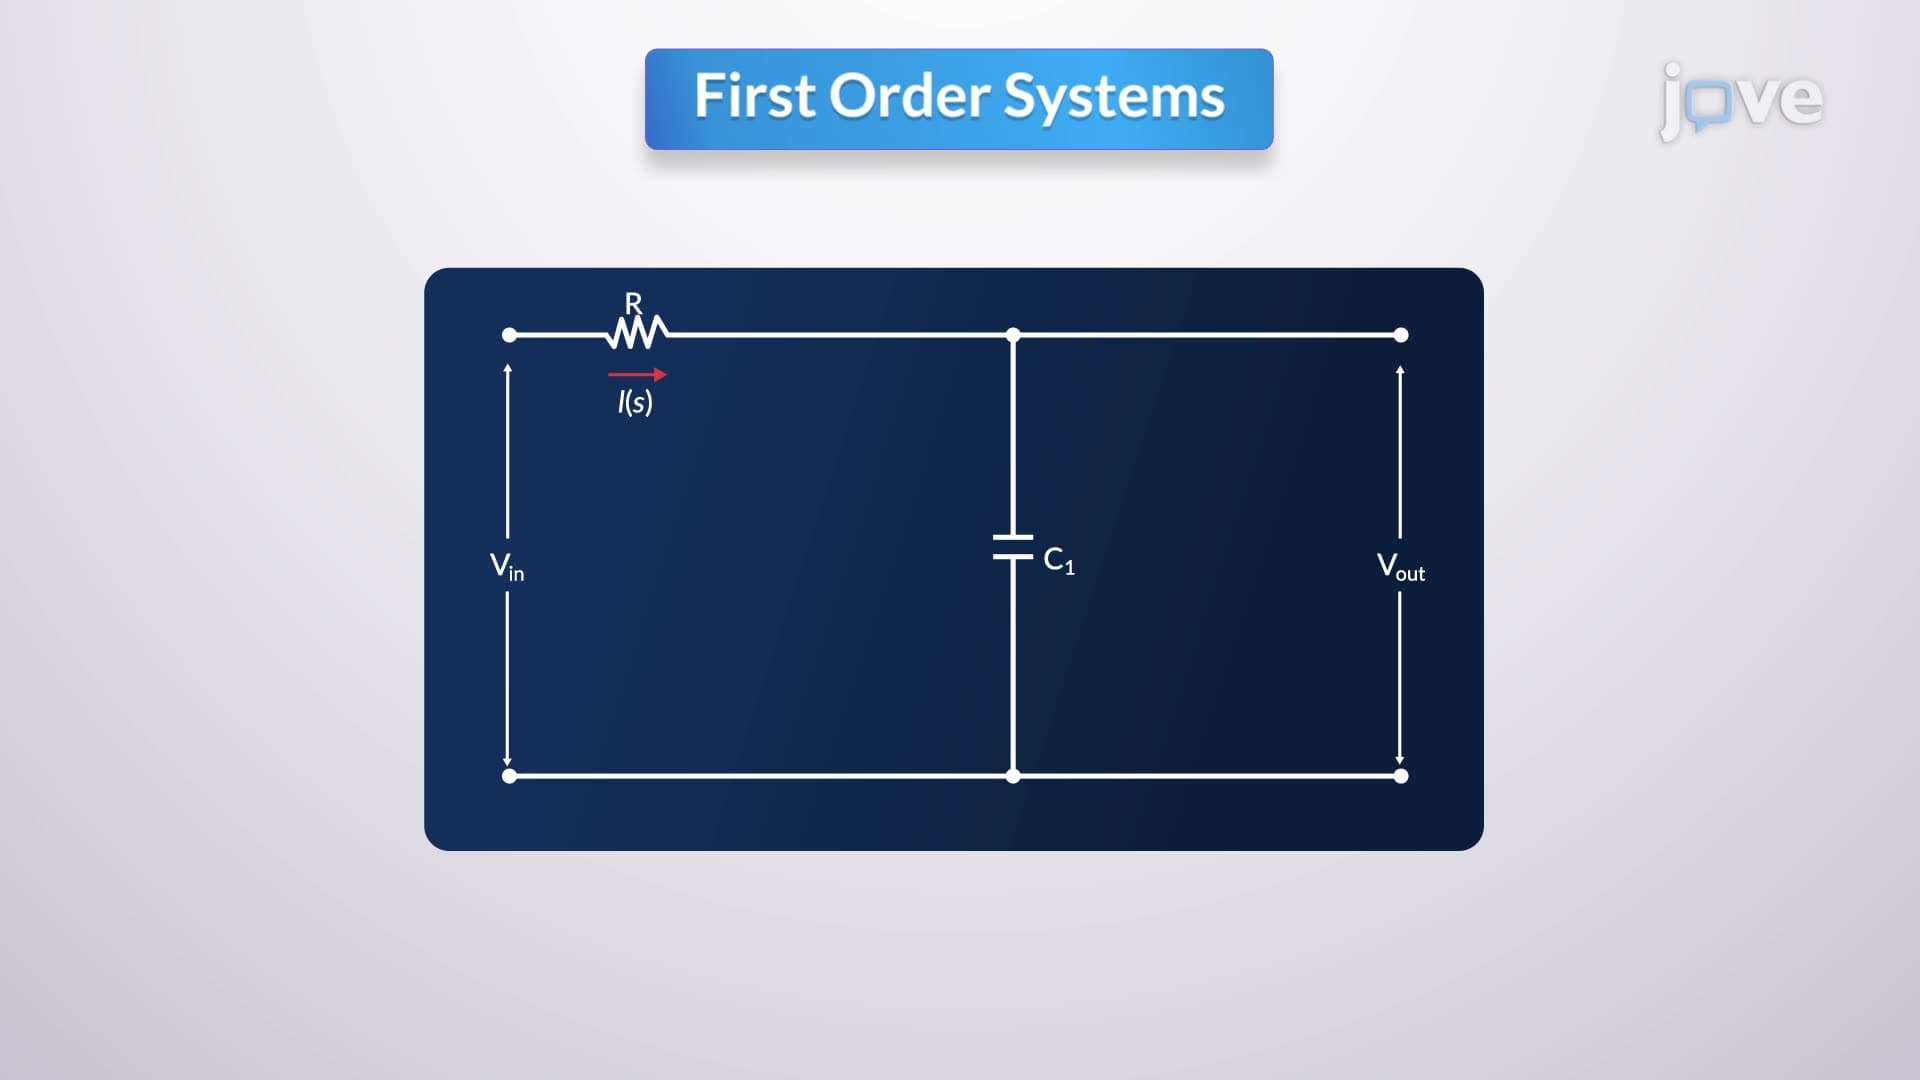
First Order Systems
When a first-order system is subjected to a unit-step input, its response is characterized by its transfer function. By applying the Laplace transform of the unit-step input to the transfer function, expanding the...
 01:20
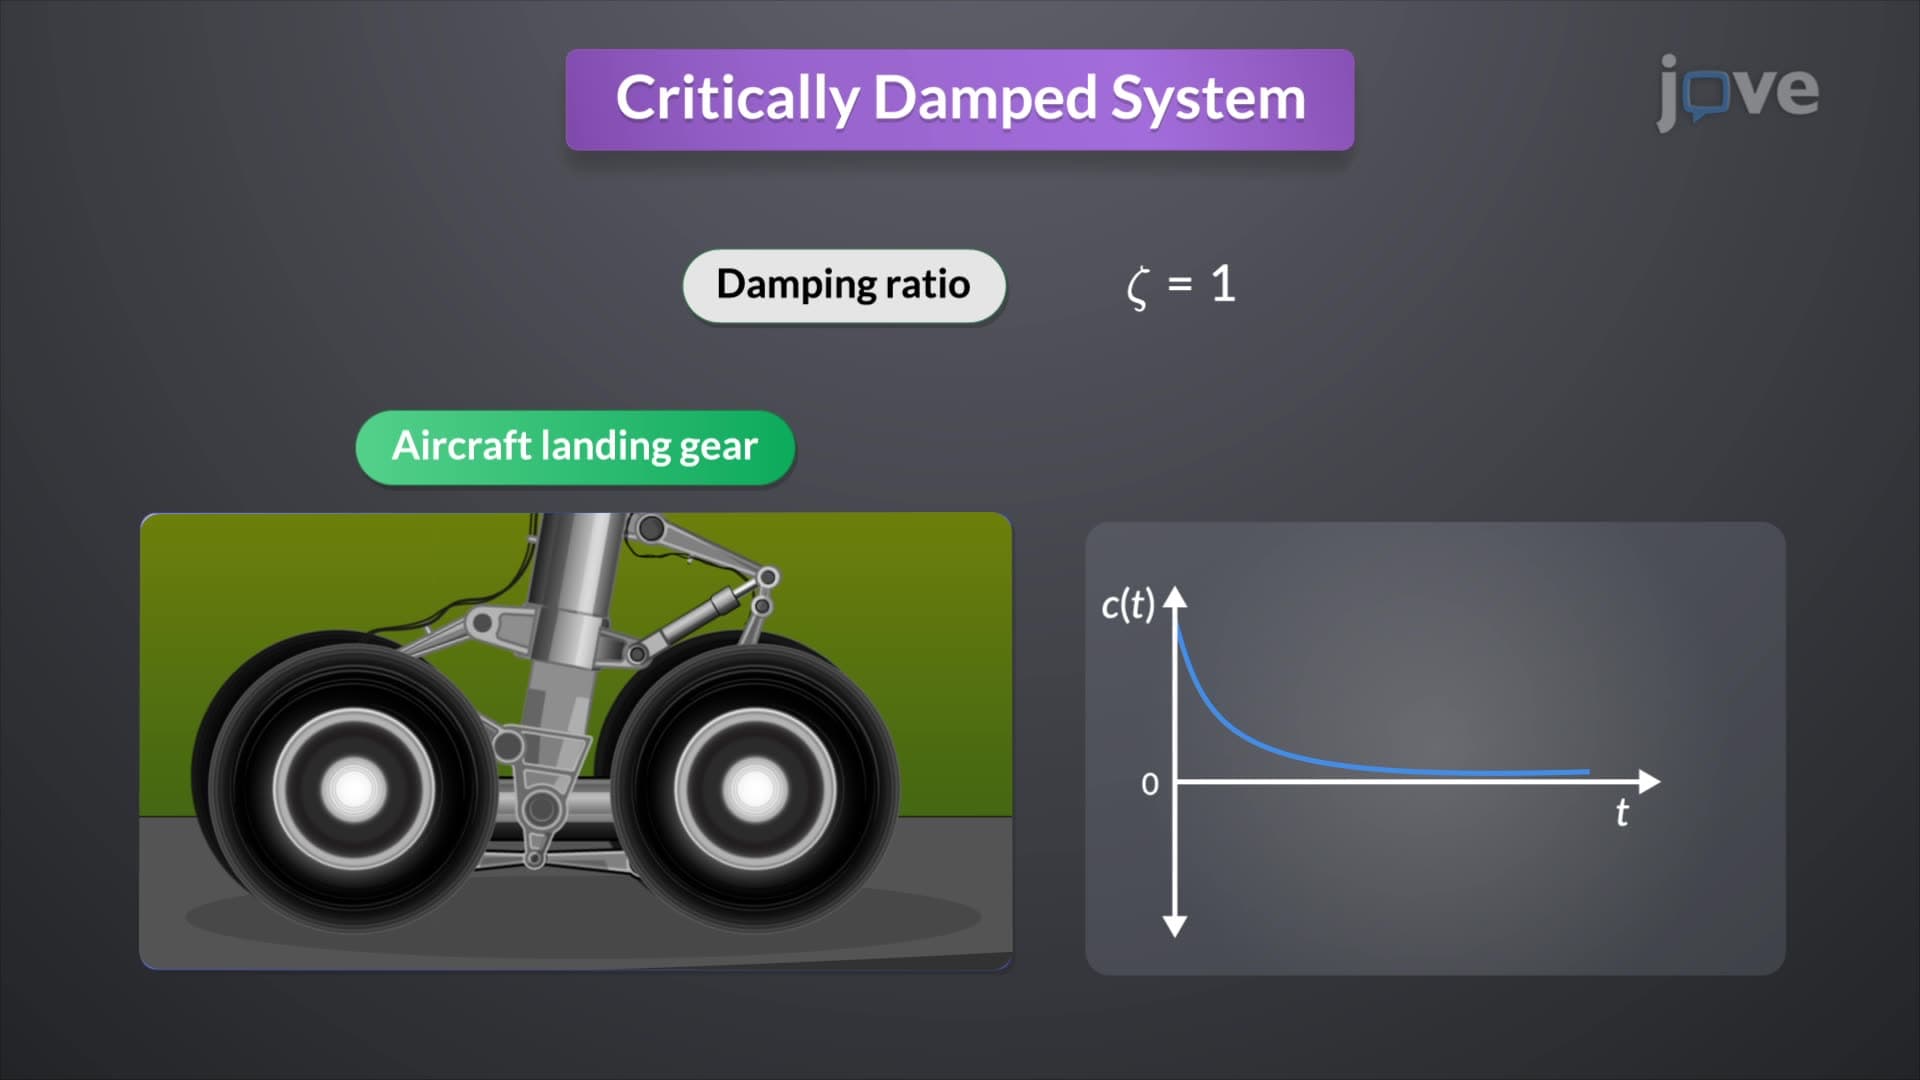
Second Order systems I
By reinterpreting the system, one can derive the closed-loop transfer function, which...
 01:11
Purpose of Health Records I
Here's a breakdown of how health records serve these purposes: