Related Experiment Video
Updated: Jan 30, 2026

Pupillary Response as Assessment of Effective Seizure Induction by Electroconvulsive Therapy
Published on: April 11, 2019
Quantification of RAPD by an automated pupillometer in asymmetric glaucoma and its correlation with manual pupillary
Manju R Pillai1, Sapna Sinha1, Pradeep Aggarwal1
1Department of Glaucoma, Aravind Eye Hospital, Madurai, Tamil Nadu, India.

Purpose:
The relative afferent pupillary defect (RAPD) is an important sign of asymmetrical retinal ganglion cell damage. The purpose of this study was to quantify RAPD by a pupillometer (RAPiDo, Neuroptics) and assess its correlation with asymmetric glaucoma and manual pupillary assessment.
Methods:
A total of 173 subjects were enrolled in the study and categorized into glaucoma, n = 130, and control, n = 43. Subjects were all recruited in the Glaucoma Clinic of the Aravind Eye Hospital in Madurai during their follow-up. They were 18 years and older, with best corrected visual acuity of 6/36 or better. Exclusion criteria included all retinal pathologies, optic atrophies, ocular injuries, severe uveitis, cloudy corneas, dense cataracts, or use of mydriatics or miotic drugs. RAPD was assessed in all subjects using an automated pupillometer and the results were compared with the swinging flash light test conducted on the same subjects by an experienced ophthalmologist. We looked at the correlation between RAPD and the intereye difference in cup-to-disc ratio (CDR), mean deviation (MD) of visual field testing, and retinal nerve fiber layer (RNFL) thickness. Sensitivity and specificity were assessed by area under the receiver operator characteristic (AUROC) analysis.
Results:
Glaucoma patients had significant RAPD (0.55 ± 0.05 log units) when compared with the controls (0.25 ± 0.05 log units), P < 0.001. Significant intereye differences in CDR, MD, and RNFL between glaucoma and control (P < 0.001) were seen. There was a good correlation between the magnitude and sign of RAPD and these intereye differences in CDR (r = 0.52, P < 0.001), MD (r = 0.44, P < 0.001) and RNFL thickness (r = 0.59, P < 0.001). When compared with the experienced ophthalmologist, AUROC was 0.94, with 89% sensitivity and 91.7% specificity.
Conclusion:
The good correlation between the magnitude of RAPD, as measured by the automated pupillometer, and intereye differences in MD, CDR, and RNFL thickness in glaucomatous, and the good sensitivity and specificity when compared with the experienced ophthalmologist, suggest that pupillometry may be useful as a screening tool to assess asymmetric glaucoma.


Related Concept Videos
 02:20
Correlations
 01:27
Correlation and Causation
Correlation versus Causation
If the dependent variable increases or decreases when the independent variable increases, there is a positive or negative...
 01:25
Glaucoma: Overview
 01:11
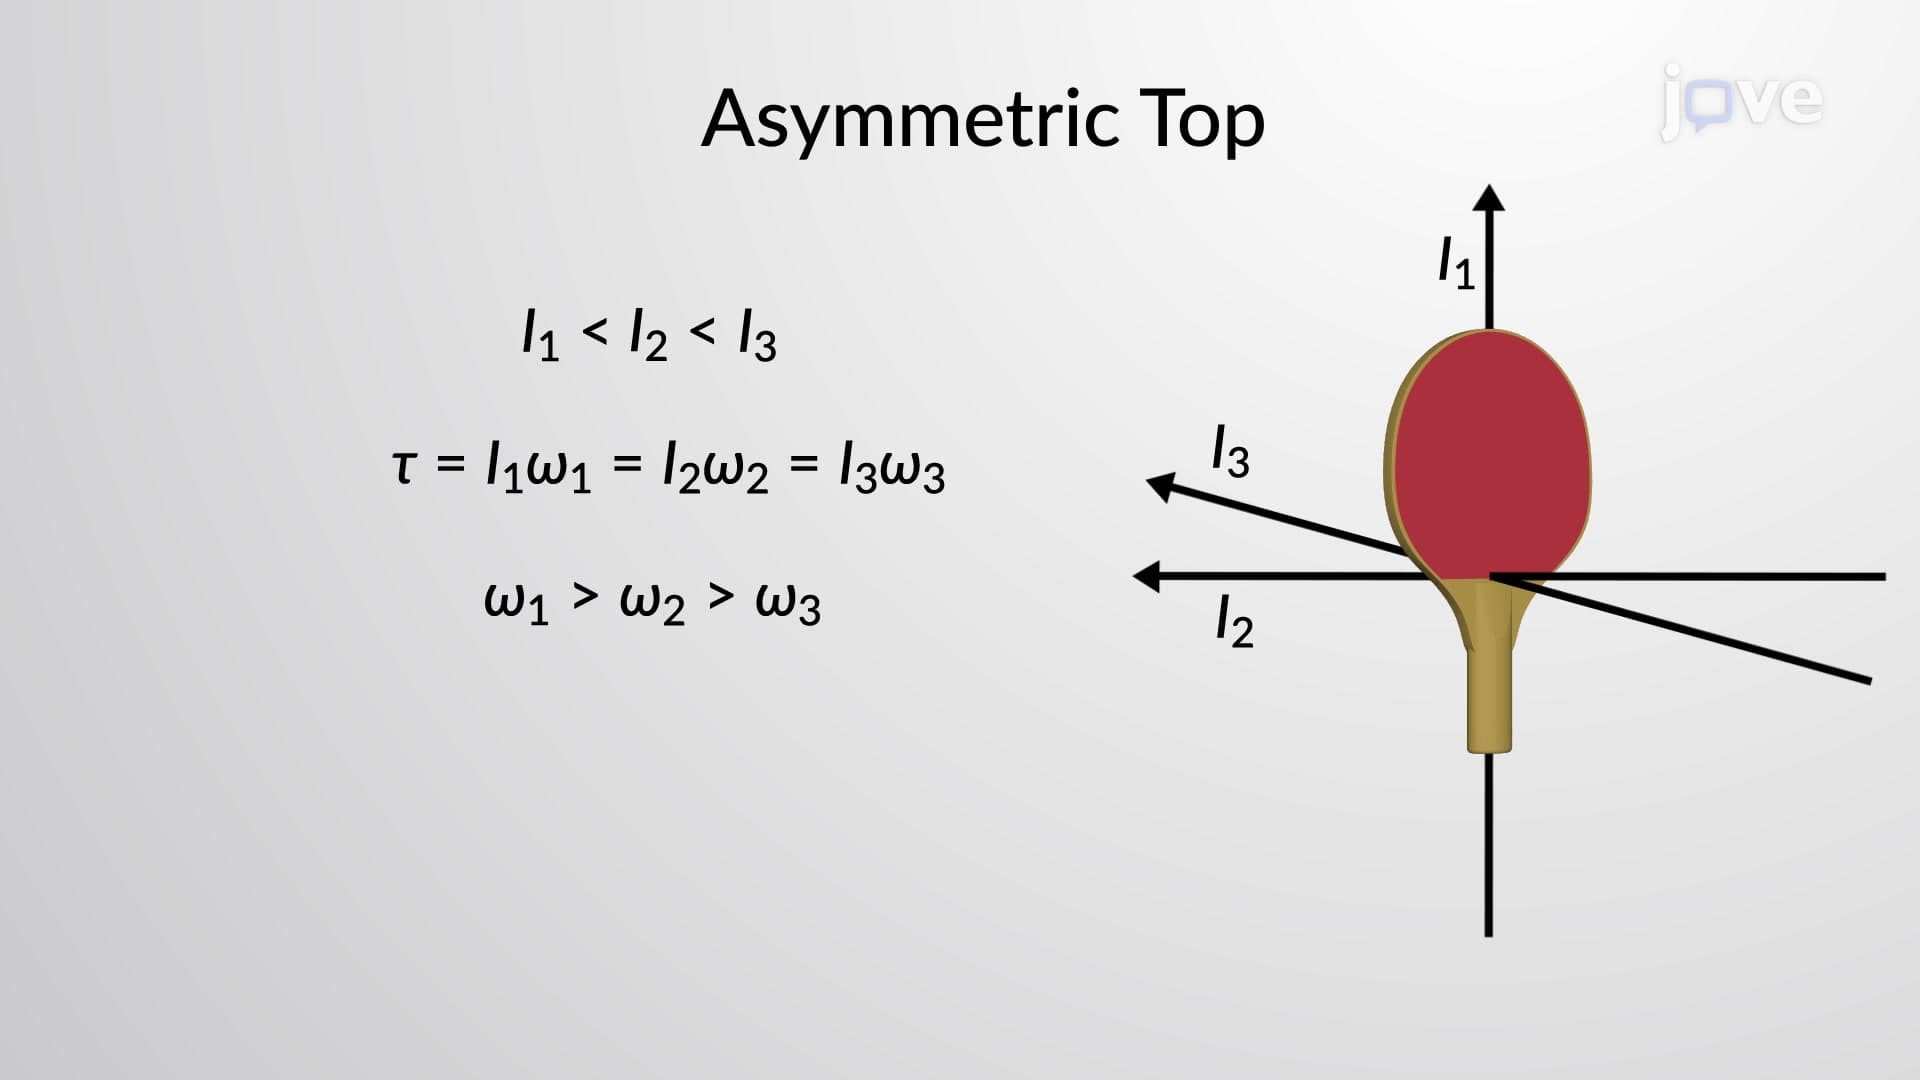
Rotation of Asymmetric Top
The relationship between the angular momentum of any rigid body and its angular velocity, both of which are vectors, involves the moment of inertia. The moment of inertia is a scalar quantity only for spherically symmetric...
 01:35
Asymmetric Lipid Bilayer
 01:09
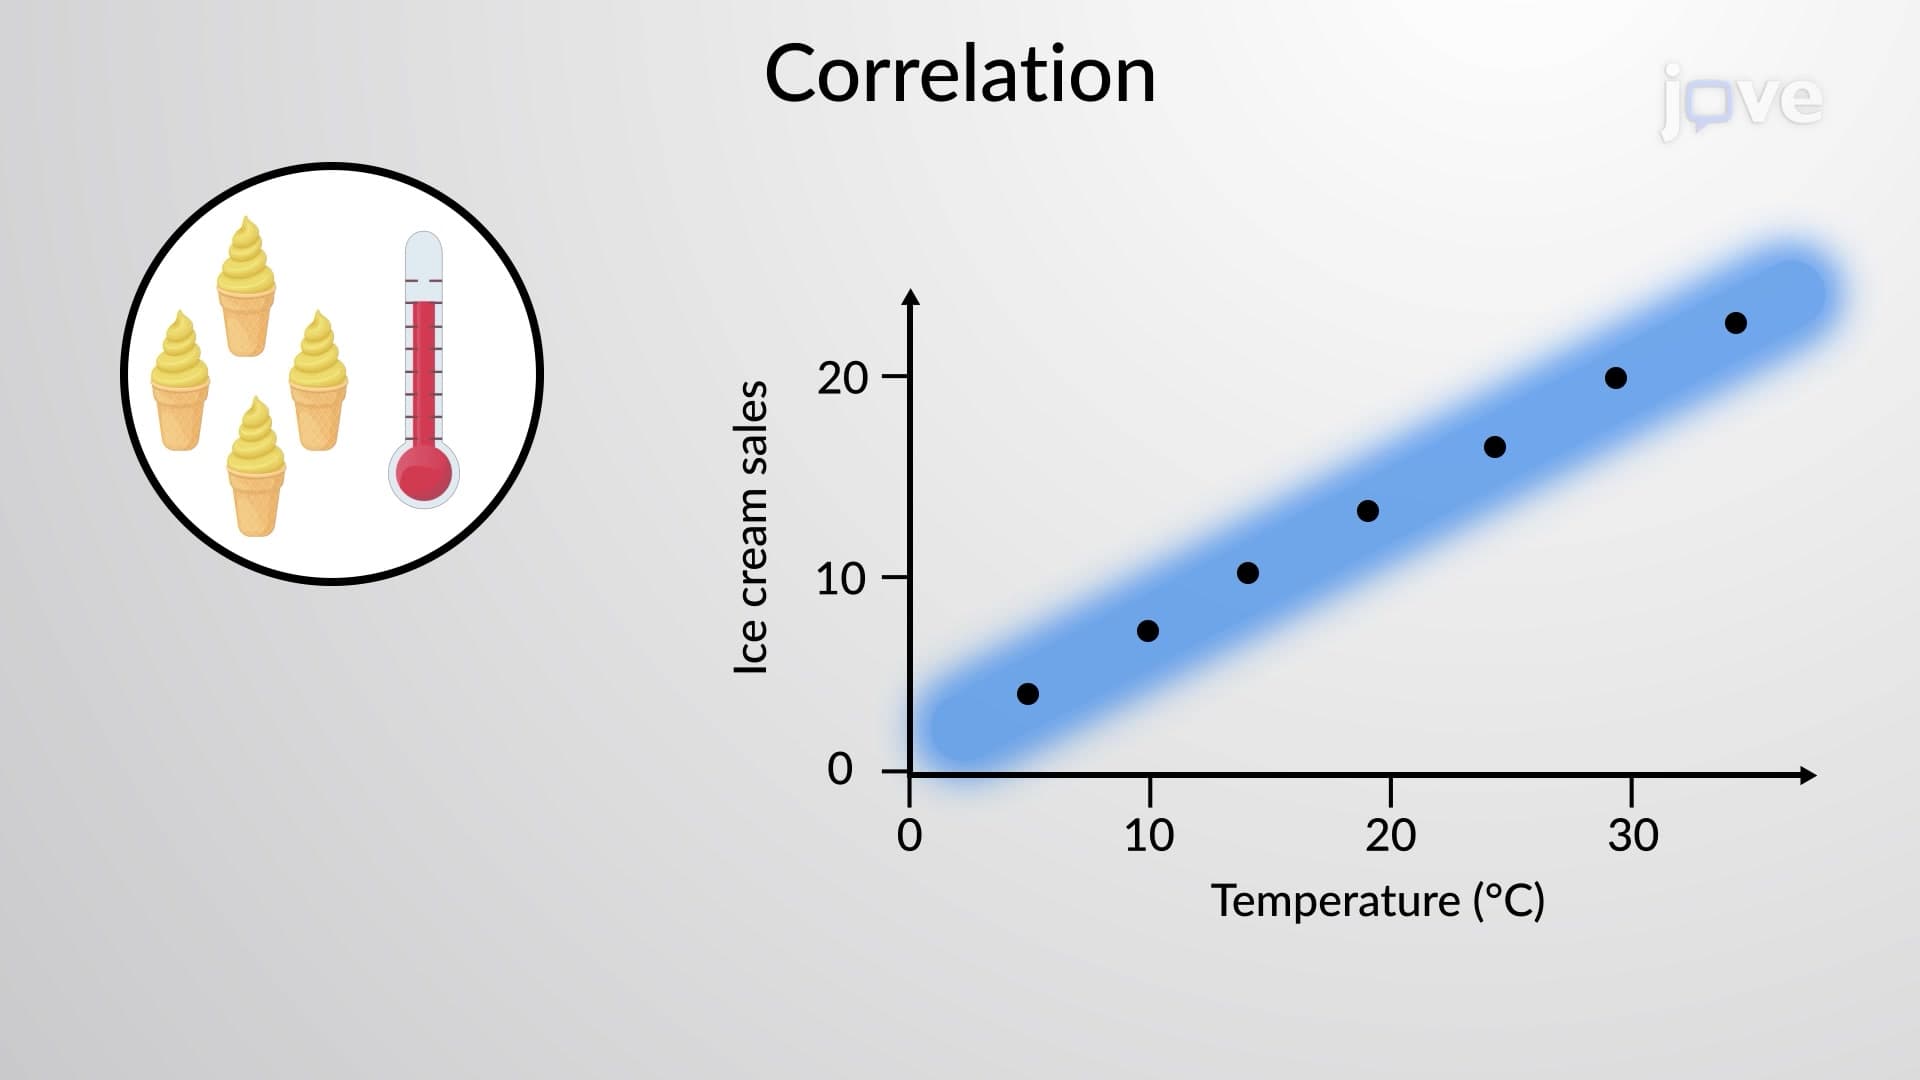
Correlation
Two variables, for example, a and b, are said to be positively correlated if both variables move in the same direction. In other words, a positive correlation exists between two variables, a and b, if: