Related Experiment Video
Updated: Jan 30, 2026

Assessment of Resistance to Tyrosine Kinase Inhibitors by an Interrogation of Signal Transduction Pathways by Antibody Arrays
Published on: September 19, 2018
Clonal MET Amplification as a Determinant of Tyrosine Kinase Inhibitor Resistance in Epidermal Growth Factor
Gillianne G Y Lai1, Tse Hui Lim2, John Lim1
11 National Cancer Centre Singapore, Singapore.

Purpose:
Mesenchymal epithelial transition factor ( MET) activation has been implicated as an oncogenic driver in epidermal growth factor receptor ( EGFR)-mutant non-small-cell lung cancer (NSCLC) and can mediate primary and secondary resistance to EGFR tyrosine kinase inhibitors (TKI). High copy number thresholds have been suggested to enrich for response to MET inhibitors. We examined the clinical relevance of MET copy number gain (CNG) in the setting of treatment-naive metastatic EGFR-mutant-positive NSCLC.
Patients And Methods:
MET fluorescence in situ hybridization was performed in 200 consecutive patients identified as metastatic treatment-naïve EGFR-mutant-positive. We defined MET-high as CNG greater than or equal to 5, with an additional criterion of MET/centromeric portion of chromosome 7 ratiο greater than or equal to 2 for amplification. Time-to-treatment failure (TTF) to EGFR TKI in patients identified as MET-high and -low was estimated by Kaplan-Meier method and compared using log-rank test. Multiregion single-nucleotide polymorphism array analysis was performed on 13 early-stage resected EGFR-mutant-positive NSCLC across 59 sectors to investigate intratumoral heterogeneity of MET CNG.
Results:
Fifty-two (26%) of 200 patients in the metastatic cohort were MET-high at diagnosis; 46 (23%) had polysomy and six (3%) had amplification. Median TTF was 12.2 months (95% CI, 5.7 to 22.6 months) versus 13.1 months (95% CI, 10.6 to 15.0 months) for MET-high and -low, respectively ( P = .566), with no significant difference in response rate regardless of copy number thresholds. Loss of MET was observed in three of six patients identified as MET-high who underwent postprogression biopsies, which is consistent with marked intratumoral heterogeneity in MET CNG observed in early-stage tumors. Suboptimal response (TTF, 1.0 to 6.4 months) to EGFR TKI was observed in patients with coexisting MET amplification (five [3.2%] of 154).
Conclusion:
Although up to 26% of TKI-naïve EGFR-mutant-positive NSCLC harbor high MET CNG by fluorescence in situ hybridization, this did not significantly affect response to TKI, except in patients identified as MET-amplified. Our data underscore the limitations of adopting arbitrary copy number thresholds and the need for cross-assay validation to define therapeutically tractable MET pathway dysregulation in EGFR-mutant-positive NSCLC.
Insights
High MET copy number gain (CNG) in EGFR-mutant non-small-cell lung cancer (NSCLC) does not impact TKI response, except in MET-amplified cases. This highlights limitations in using arbitrary thresholds for MET pathway dysregulation in NSCLC.
Area of Science:
- Oncology
- Genetics
- Molecular Biology
Background:
- Mesenchymal epithelial transition factor (MET) activation is a key driver in EGFR-mutant non-small-cell lung cancer (NSCLC).
- MET activation can lead to resistance against EGFR tyrosine kinase inhibitors (TKIs).
- High MET copy number gain (CNG) is proposed to predict response to MET inhibitors.
Purpose of the Study:
- To evaluate the clinical relevance of MET copy number gain (CNG) in treatment-naive metastatic EGFR-mutant-positive NSCLC.
- To determine if high MET CNG predicts response to EGFR TKIs.
- To investigate the heterogeneity of MET CNG in NSCLC.
Main Methods:
- 200 metastatic treatment-naive EGFR-mutant-positive NSCLC patients underwent MET fluorescence in situ hybridization.
- MET-high was defined as CNG ≥ 5, with amplification requiring a MET/chromosome 7 ratio ≥ 2.
- Time-to-treatment failure (TTF) to EGFR TKI was analyzed using Kaplan-Meier and log-rank tests.
Main Results:
- 26% of patients were MET-high; 3% had MET amplification.
- No significant difference in median TTF was observed between MET-high and MET-low groups (12.2 vs. 13.1 months, P = .566).
- Suboptimal response to EGFR TKI was noted in patients with coexisting MET amplification.
Conclusions:
- High MET CNG does not significantly impact EGFR TKI response in NSCLC, except in cases of MET amplification.
- Arbitrary copy number thresholds may be insufficient for defining therapeutically relevant MET pathway alterations.
- Cross-assay validation is crucial for defining MET pathway dysregulation in EGFR-mutant NSCLC.
Related Concept Videos
 01:26
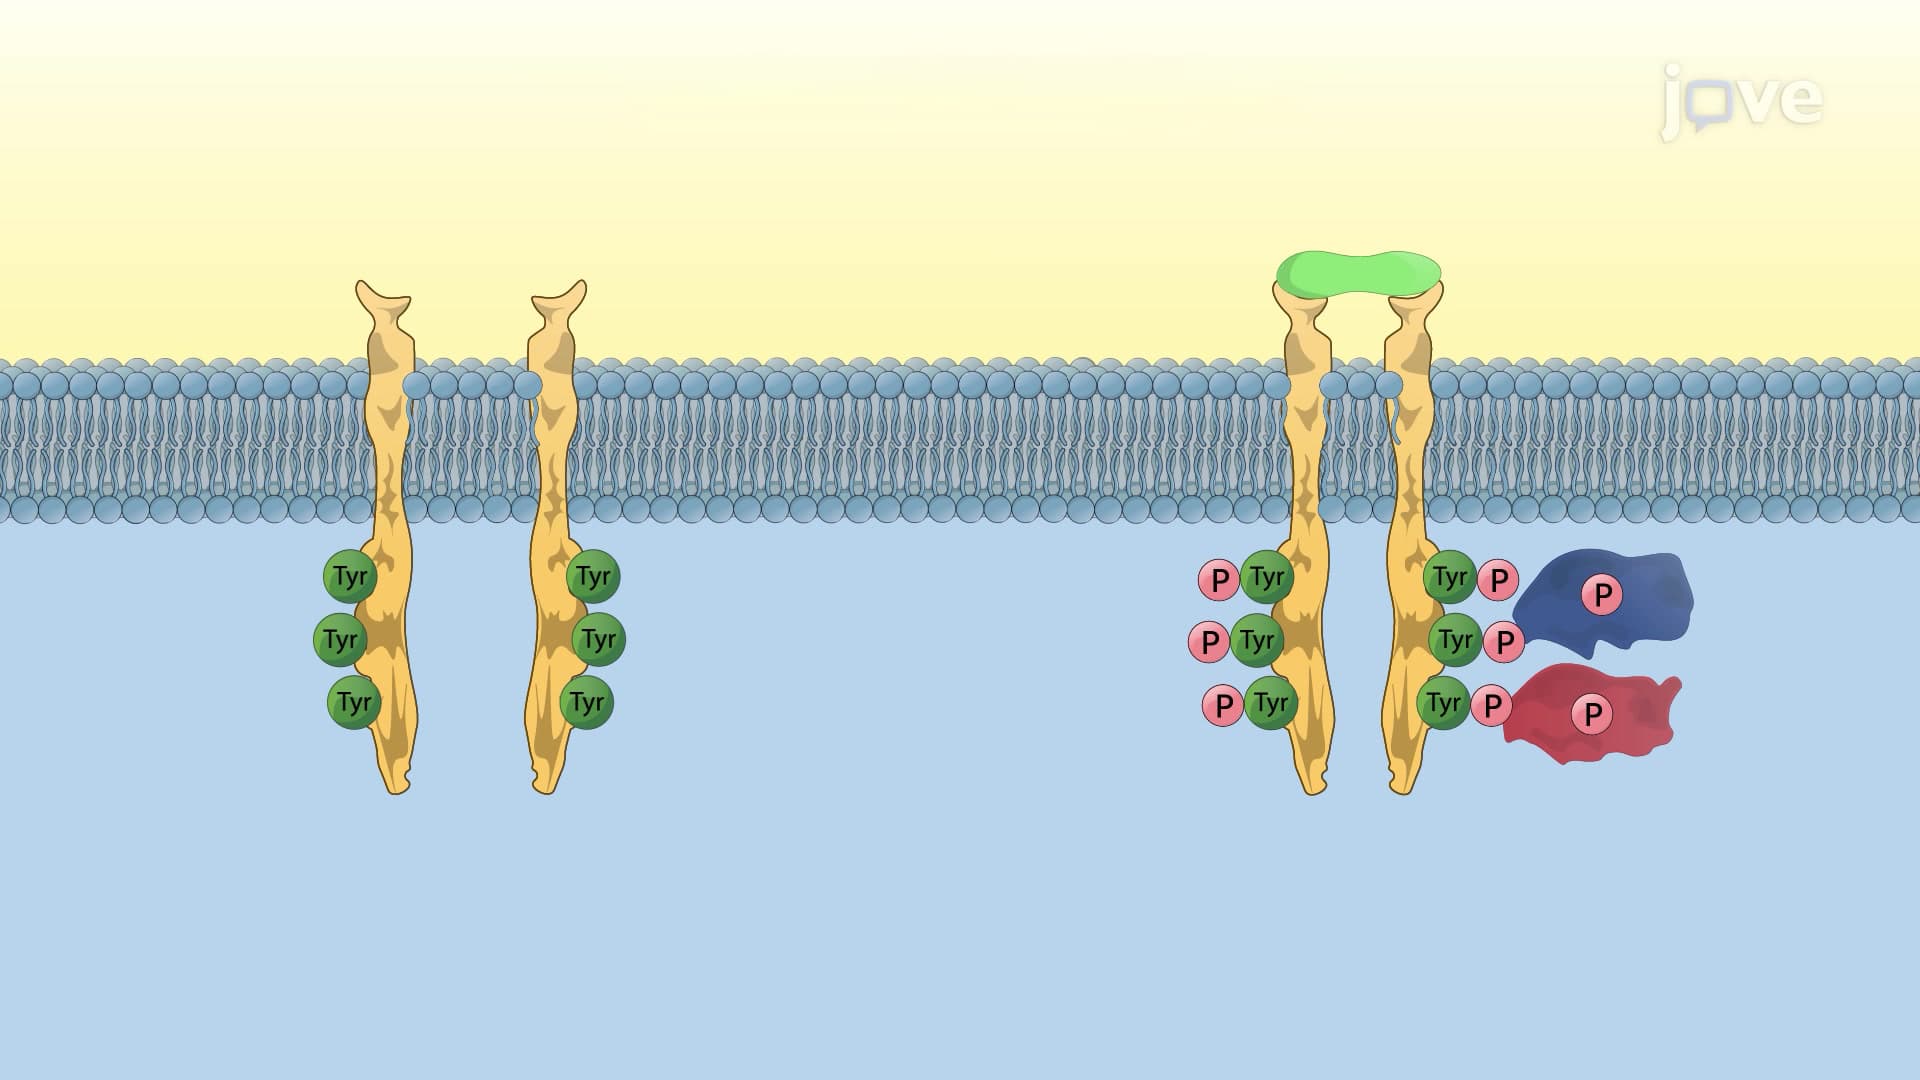
Receptor Tyrosine Kinases
 01:26
Treatment for Pulmonary Arterial Hypertension: Receptor Tyrosine Kinase Inhibitors and Calcium Channel Blockers
TKIs, such as imatinib (Gleevec), are particularly effective in tackling the growth and mitogenic factors that become upregulated in PAH patients. These factors contribute to the...
 02:54
Protein Kinases and Phosphatases
Protein kinases
Many proteins in the cell are regulated by phosphorylation, the addition of a phosphate group. A family of enzymes called kinases...
 01:00
Enzyme-linked Receptors
Neurotrophin (NT) receptors are a family of RTKs, including trkA, trkB, and trkC (tropomyosin-related kinase) receptors. TrkA is specific for nerve growth factor (NGF), neurotrophin-6, and neurotrophin-7. TrkB binds...
 02:56
Treatment Resistant Cancers
 01:28
Role of Hematopoietic Growth Factors
Thrombopoietin (TPO), mainly released by the liver,...