Related Experiment Video
Updated: Jan 30, 2026

Modified Single-Loop Reconstruction for Pancreaticoduodenectomy
Published on: September 28, 2019
Post-Pancreaticoduodenectomy Outcomes and Epidural Analgesia: A 5-year Single-Institution Experience
Rachel E Simpson1, Mitchell L Fennerty2, Cameron L Colgate3
1Department of Surgery, Indiana University School of Medicine, Indianapolis, IN; Pancreatic Cyst and Cancer Early Detection Center, Indiana University Health, Indianapolis, IN.

Background:
Optimal pain control post pancreaticoduodenectomy is a challenge. Epidural analgesia (EDA) is used increasingly, despite inherent risks and unclear effects on outcomes.
Methods:
All pancreaticoduodenectomies (PDs) performed from January 2013 through December 2017 were included. Clinical parameters were obtained from a retrospective review of a prospective clinical database, the American College of Surgeons NSQIP prospective institutional database, and medical record review. Chi-square, Fisher's exact test, and independent-samples t-tests were used for univariable analyses. Multivariable regression was performed.
Results:
Six hundred and seventy-one consecutive PDs from a single institution were included (429 EDA, 242 non-EDA). On univariable analysis, EDA patients experienced significantly less wound disruption (0.2% vs 2.1%), unplanned intubation (3.0% vs 7.9%), pulmonary embolism (0.5% vs 2.5%), mechanical ventilation longer than 48 hours (2.1% vs 7.9%), septic shock (2.6% vs 5.8%), and lower pain scores. On multivariable regression (accounting for baseline group differences (ie sex, hypertension, preoperative transfusion, laboratory results, approach, and pancreatic duct size), EDA was associated with less superficial wound infections (odds ratio [OR] 0.34; 95% CI 0.14 to 0.83; p = 0.017), unplanned intubations (OR 0.36; 95% CI 0.14 to 0.88; p = 0.024), mechanical ventilation longer than 48 hours (OR 0.22; 95% CI 0.08 to 0.62; p = 0.004), and septic shock (OR 0.39; 95% CI 0.15 to 1.00; p = 0.050). Epidural analgesia improved pain scores post-PD days 1 to 3 (p < 0.001). No differences were seen in cardiac or renal complications; pancreatic fistula (B+C) or delayed gastric emptying, 30-/90-day mortality, length of stay, readmission, discharge destination, or unplanned reoperation.
Conclusions:
Based on the largest single-institution series published to date, our data support the use of EDA for optimization of pain control. More importantly, our data document that EDA improved infectious and pulmonary complications significantly.

Related Concept Videos
 01:25
Analgesia and Pain Management
 01:04
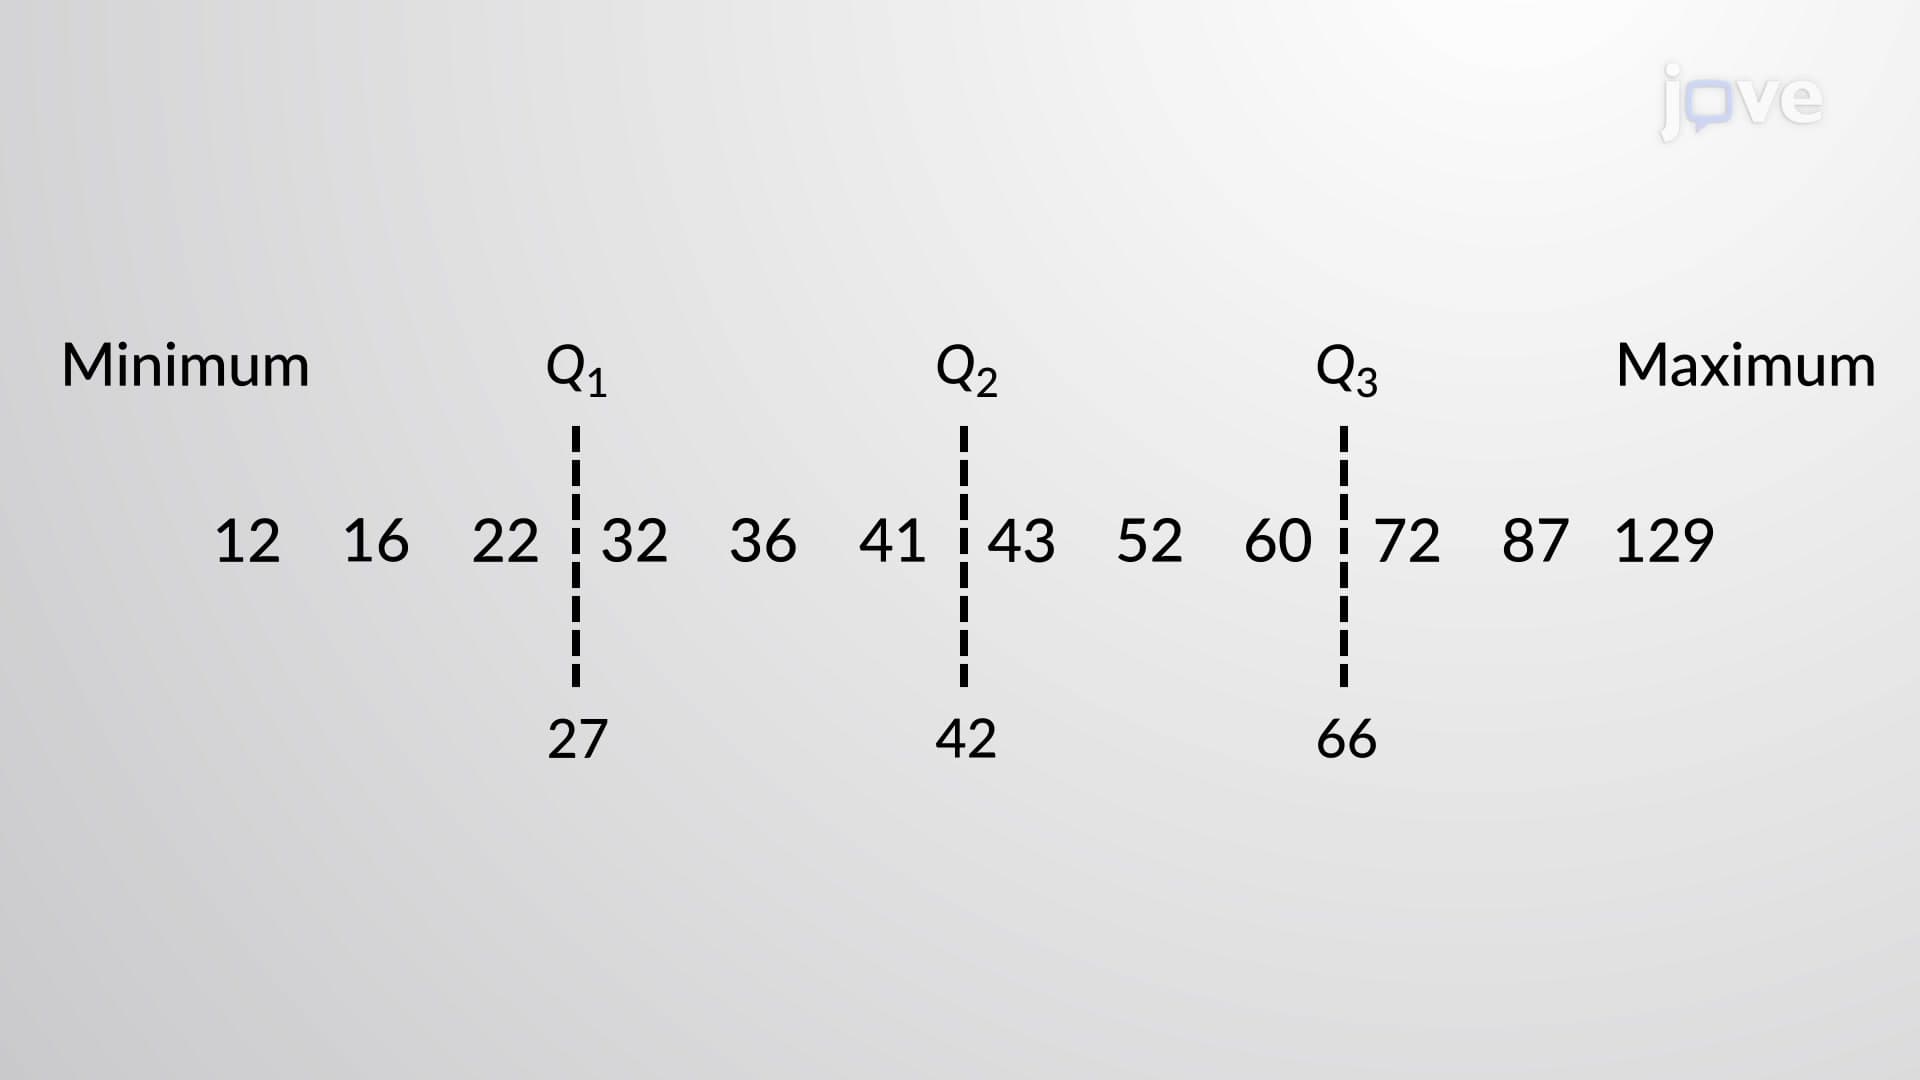
5-Number Summary
In a box plot, the minimum and maximum data values represent the lower and upper whiskers in the graph, and the median is designated as the center of the box in the chart. The first quartile and third...
 02:24
Predicting Reaction Outcomes
 01:13
Outcomes of Glycolysis
Cellular respiration can occur aerobically (with oxygen) or anaerobically (without oxygen). In the presence of oxygen, cellular respiration starts with glycolysis and continues with pyruvate...
 01:29
Local Anesthetics: Clinical Application as Epidural Anesthesia
Since epidural anesthetics can be infused through an epidural catheter, all types of drugs, including short-acting ones, can be administered. Chloroprocaine and lidocaine are examples of short and long-duration anesthetics, respectively. Bupivacaine...
 01:12
What is an Experiment?