Related Experiment Video
Updated: Jan 30, 2026
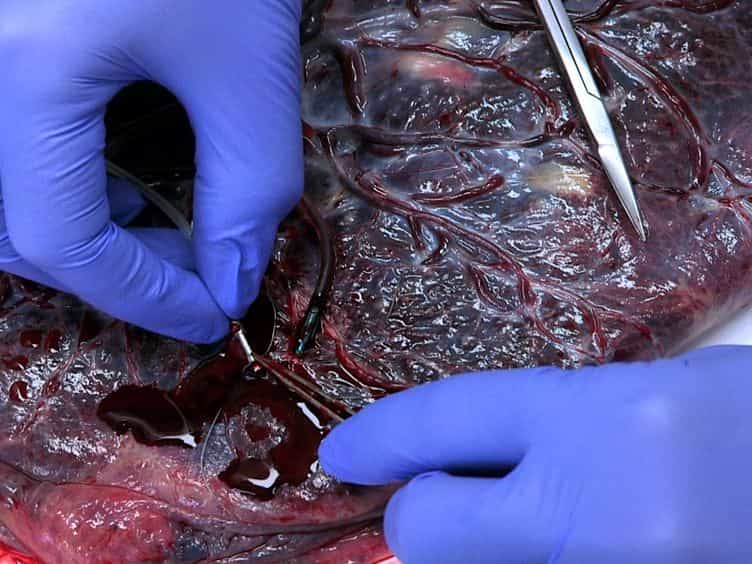
Determination of the Transport Rate of Xenobiotics and Nanomaterials Across the Placenta using the ex vivo Human Placental Perfusion Model
Published on: June 18, 2013
Diagnosis and management of placenta previa and low placental implantation
Souhail Alouini1, Pascal Megier1, Arnaud Fauconnier2
1Department of Gynaecology and Obstetrics, Centre Hospitalier Régional d'Orléans, Orleans, France.

Objective: To evaluate the migration of low-placental implantation (LPI) during the third trimester of pregnancy and its effect on delivery and post-partum hemorrhage.Methods: We conducted a retrospective study at a level 3 maternity center including all cases of placenta previa (PP) and LPI between 1998 and 2014. The distance (d) between cervical internal os (CIO) and placental edge (PE) were measured by vaginal ultrasonography in the third trimester of pregnancy at 32 and 3 weeks after. We analyzed CIO-PE distance, volume of post-partum hemorrhage, delivery decision, and mode of delivery using Kruskall-Wallis test.Results: In total, 319 patients presented with PP or LPI. All complete PP (121) and 90.6% (58 of 64) of the placentas less than 1 cm from the CIO did not migrate. Among the 138 placentas with an initial CIO-PE d greater than 1 cm, only 17 (12.3%) did not migrate above 2 cm. The patients for whom the decision to perform a cesarean section (C-section) was retained and realized had a CIO-PE d significantly lower than those who delivered vaginally (p < .001). The patients who delivered by C-section had a lower CIO-PE d when an emergency C-section was performed, specifically for hemorrhage (p < .001). The mean volume of hemorrhage was significantly higher for patients with a CIO-PE d less than 2 cm.Conclusion: Complete PP and the majority of the placentas less than 1 cm from the CIO did not migrate. Above 1 cm, the majority of the placentas migrated three to four weeks later. For the placentas less than 1 cm from the CIO, a significant risk of hemorrhage at delivery was observed. Thus, prophylactic cesarean section is required for CIO-PE distances <1 cm. For distances between 1 and 2 cm, the volume of blood loss tends to be more important than for distances >3 cm without statistical significance. A vaginal delivery could be tried after information of patients.
Objective: To evaluate the migration of low-placental implantation (LPI) during the third trimester of pregnancy and its effect on delivery and post-partum hemorrhage.Methods: We conducted a retrospective study at a level 3 maternity center including all cases of placenta previa (PP) and LPI between 1998 and 2014. The distance (d) between cervical internal os (CIO) and placental edge (PE) were measured by vaginal ultrasonography in the third trimester of pregnancy at 32 and 3 weeks after. We analyzed CIO-PE distance, volume of post-partum hemorrhage, delivery decision, and mode of delivery using Kruskall-Wallis test.Results: In total, 319 patients presented with PP or LPI. All complete PP (121) and 90.6% (58 of 64) of the placentas less than 1 cm from the CIO did not migrate. Among the 138 placentas with an initial CIO-PE d greater than 1 cm, only 17 (12.3%) did not migrate above 2 cm. The patients for whom the decision to perform a cesarean section (C-section) was retained and realized had a CIO-PE d significantly lower than those who delivered vaginally (p < .001). The patients who delivered by C-section had a lower CIO-PE d when an emergency C-section was performed, specifically for hemorrhage (p < .001). The mean volume of hemorrhage was significantly higher for patients with a CIO-PE d less than 2 cm.Conclusion: Complete PP and the majority of the placentas less than 1 cm from the CIO did not migrate. Above 1 cm, the majority of the placentas migrated three to four weeks later. For the placentas less than 1 cm from the CIO, a significant risk of hemorrhage at delivery was observed. Thus, prophylactic cesarean section is required for CIO-PE distances <1 cm. For distances between 1 and 2 cm, the volume of blood loss tends to be more important than for distances >3 cm without statistical significance. A vaginal delivery could be tried after information of patients.


Related Concept Videos
 01:24
Gonadal and Placental Hormones
In males, testosterone is the primary gonadal androgen. It plays a central role in the maturation of male reproductive organs — the penis and testes. Additionally, testosterone is instrumental in the development of secondary sexual characteristics — a deep voice as well as facial and pubic hair...
 01:22
Nursing Diagnosis
The nursing diagnosis focuses on evidence-based...
 01:26
Formulating and Validating Nursing Diagnosis I
There are thirteen domains...
 01:10
Documentation of Nursing Diagnosis
In some settings, data-driven computerized decision support systems are in place, allowing for more accurate nursing diagnoses. The database within one of these systems includes diagnostic labels defining characteristics, activities, and indicators for nursing. A nurse enters...
 01:25
Formulating and Validating Nursing Diagnosis II
Risk nursing diagnoses represent clinical judgments of an individual, family, or community more vulnerable to developing the health problem than others...
 01:15
Diabetes: Symptoms, Diagnosis, and Complications