Related Experiment Video
Updated: Jan 30, 2026
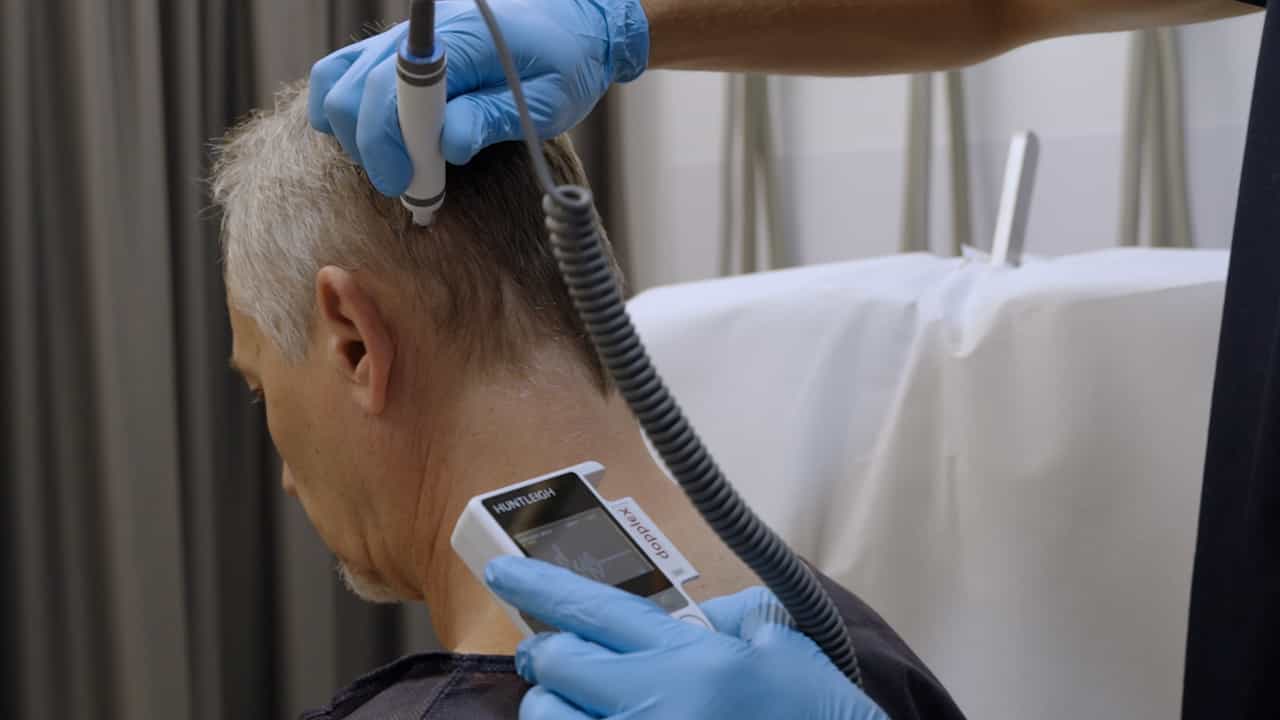

Author Spotlight: Minimally Invasive Relief for Occipital Neuralgia at the Nuchal Line
Published on: September 13, 2024
Management of Chronic Migraine and Occipital Neuralgia in Post 9/11 Combat Veterans
Karen A Williams1, Robin M Lawson2, Osvaldo H Perurena3
1Central Texas Veterans Health Care System, Medical Service, 1901 Veterans Memorial Drive, Temple, TX.

Introduction:
The rate of chronic migraine (CM) has been shown to be 20% or greater in the post 9/11 combat veteran population with a history of traumatic brain injury, while the rate is much lower at 3-5% in the general population. Studies have shown that medications such as oral topiramate or intramuscular injections of onabotulinum toxin A (Botox) have been used for CM prevention, and occipital blocks have been shown to be helpful in treating occipital neuralgia and short-term relief of CM. However, there are no known studies that have specifically evaluated the use of Botox and occipital blocks for reducing headache frequency in the US veteran population. The purpose of this study was to evaluate the effectiveness of using occipital blocks and Botox as dual therapy for reducing headache frequency in post 9/11 combat veterans with CM, occipital neuralgia, and a history of TBI or neck trauma.
Materials And Methods:
Following Institutional Review Board approval, a retrospective chart review was completed on post 9/11 combat veterans treated in a headache clinic located at the Central Texas Veteran Health Care System. The electronic medical record was used to retrieve the charts of post 9/11 combat veterans who (1) had a confirmed deployment-related history of TBI or neck trauma; (2) were diagnosed with CM and occipital neuralgia; and (3) were treated in the headache clinic between January 1, 2014 and December 31, 2015 with the administration of occipital blocks and Botox within the first six months. Of 282 charts that were reviewed, a total of 30 (N = 30) veterans fit the criteria. The mean number of self-reported headache days per month (28 days) for the month prior to starting treatment was compared to the number of headache days per month (28 days) 6 months after initiation of therapy.
Results:
Results revealed that the mean number of headache days in the month prior to treatment was 24.1 (22.0, 25.7). The mean number of headache days in the month post-treatment (6 months after the initiation of dual therapy with occipital blocks and Botox) was 12.9 (9.7, 16.4). The mean difference in the number of headache days from pre- to post-treatment (pre-treatment minus post-treatment) was 11.2 (8.2, 14.2).
Conclusion:
This study evaluated the effectiveness of using occipital blocks and Botox as dual therapy for reducing headache frequency for post 9/11 combat veterans with CM, occipital neuralgia, and a history of TBI or neck trauma. Results revealed a statistically significant reduction in the number of headache days per month after the dual therapy. There were multiple limitations to the study to include a small sample size, lack of a control group, self-reported headaches for only 1 month pre-and post-treatment, and no control for other interventions or events which may have influenced the outcome. There is a strong need for randomized, double blinded, placebo- controlled studies involving dual therapy in this population. This study, though small, may be helpful in stimulating additional studies and treatments in this veteran population.

Related Concept Videos
 01:29
Chronic Obstructive Pulmonary Disease-V: Management
Smoking Cessation
 01:28
Cardiomyopathy VII: Pre and Post Operative Nursing Management
 01:30
Chronic Obstructive Pulmonary Disease-V: Nursing Management
Assessment
 01:18
Chronic Kidney Disease IV: Nursing Management
 01:23
Chronic Pharyngitis
Etiology
It often arises from persistent viral or bacterial infections affecting sinuses and tonsils.
Additional contributing factors include inadequate dental hygiene, mouth breathing, recurring tonsillitis, allergic rhinitis, laryngopharyngeal reflux, and exposure to smoke, chemicals, and other environmental pollutants. Allergic reactions to pollen, mold, and pet dander, chronic cough, excessive voice usage,...
 01:26
Tonsillitis II: Management