Related Experiment Video
Updated: Jan 30, 2026

Duodenal-Jejunal Bypass Surgery in Diet-Induced Obese Diabetic Mice
Published on: October 18, 2024
Feasibility of primary sternal plating for morbidly obese patients after cardiac surgery
Joshua M Liao1, Patrick Chan2, Lorraine Cornwell3,4
1Department of Medicine, University of Washington, Seattle, WA, USA.

Background:
Morbidly obese patients (body mass index [BMI] ≥ 35 kg/m2) who undergo cardiac surgery involving median sternotomy have a higher-than-normal risk of sternal dehiscence. To explore a potential solution to this problem, we examined the utility of transverse sternal plating for primary sternal closure in morbidly obese cardiac surgical patients.
Methods:
We retrospectively reviewed data from cardiac surgical patients who underwent single primary xiphoid transverse titanium plate reinforcement for primary sternal closure from August 2009 to July 2010 (n = 8), and we compared their outcomes with those of patients with BMI ≥35 kg/m2 who underwent cardiac surgery without sternal plate reinforcement from April 2008 to July 2009 (n = 14). All cases were performed by the same surgeon.
Results:
The 2 groups of patients had similar demographics and comorbidities (P > 0.05 for all). All patients with sternal plate reinforcement reported sternal stability at last follow-up (at a median of 27 months postoperatively; range, 8.4-49.3 months), whereas 1 patient (7.1%) who underwent standard closure developed sterile sternal dehiscence (P = 0.4). Postoperative patient-controlled analgesia (PCA) morphine usage was significantly higher for patients without sternal plate reinforcement than for patients who had sternal plate reinforcement (3.6 mg/h vs 1.3 mg/h, P = 0.008). No patient in the sternal plate group had wound seroma or perioperative complications attributable to sternal closure technique.
Conclusion:
Single xiphoid transverse plate reinforcement for primary sternal closure is a feasible option for morbidly obese patients, who are otherwise at high risk of developing sternal dehiscence. Using this technique may decrease postoperative narcotics usage. Morbidly obese patients (body mass index ≥35 kg/m2) have a higher-than-normal risk of sternal dehiscence after cardiac surgery. In a pilot study, we found that those who underwent transverse sternal plating (n = 8) had no sternal dehiscence and required less postoperative analgesia than patients who underwent standard wire closure (n = 14).
More Related Videos
 15:11
Surgical Fixation of Sternal Fractures: Preoperative Planning and a Safe Surgical Technique Using Locked Titanium Plates and Depth Limited Drilling
Published on: January 5, 2015
 06:46
Competing-Risk Nomogram for Predicting Cancer-Specific Survival in Multiple Primary Colorectal Cancer Patients after Surgery
Published on: September 27, 2024
Related Concept Videos
 01:21
Drug Dosing: Obese Patients
 01:25
Pharmacokinetics in Obese Patients: Drug Absorption and Distribution
 01:20
Pharmacokinetics in Obese Patients: Drug Metabolism and Excretion
 01:24
Obesity
 01:22
Cardiac Output II: Effect of Stroke Volume on Cardiac Output
Preload
Preload refers to the initial elongation of the cardiac myocytes before contraction and is related to the volume of blood filling the heart at the end of diastole, or end-diastolic volume. The...
 01:19
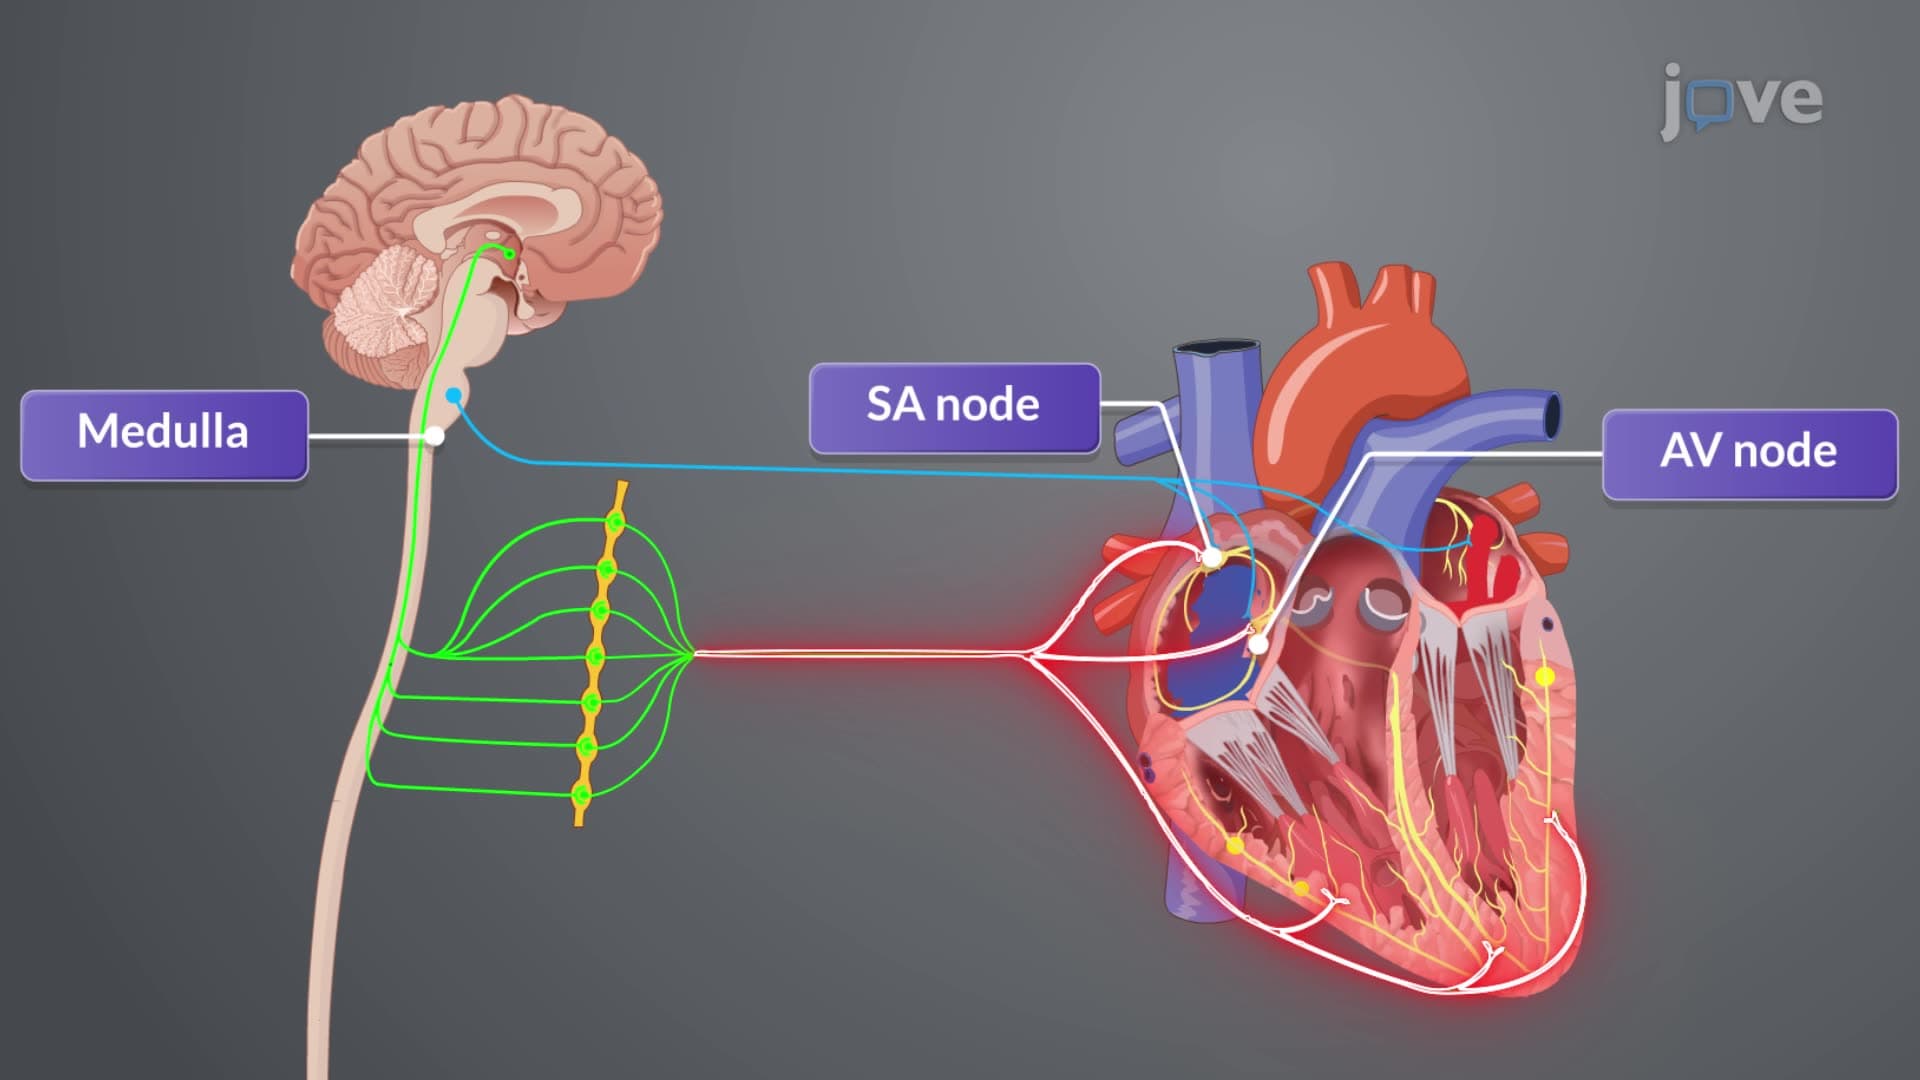
Cardiac Output I:Effect of Heart Rate on Cardiac Output
Cardiac output (CO) refers to the total amount of blood ejected by one of the ventricles in liters per minute (L/min). In a resting adult, CO ranges from 5 to 6 L/min, adjusting according to the body's metabolic requirements.
Effect of Heart Rate on Cardiac Output
Cardiac output adapts to metabolic demands during stress, physical activity, or illness. The autonomic nervous system regulates heart rate via the sinoatrial node. The parasympathetic nervous system decreases heart...