Related Experiment Video
Updated: Jan 30, 2026
Analysis of Coronary Vessels in Cleared Embryonic Hearts
Published on: December 7, 2016
Complete Heart Block in a Diabetic Patient with a Preexisting LBBB and Normal Coronaries, Paradoxically Responding to
Nikolaos S Ioakeimidis1, Dimitrios Valasiadis1, Lykourgos Nanis1
1Department of Cardiology, General Hospital of Florina "Eleni Th. Dimitriou", Egnatias 9, Florina 53100, Greece.

Insights
This case study highlights a complete atrioventricular block with varying bundle branch block patterns. Prompt treatment with atropine successfully restored sinus rhythm, demonstrating a dynamic cardiac response.
Area of Science:
- Cardiology
- Electrophysiology
Background:
- A 66-year-old female with hypertension, diabetes, and hypothyroidism presented with dizziness and fatigue.
- The patient had a known history of Left Bundle Branch Block (LBBB).
Observation:
- Initial presentation revealed a complete atrioventricular block with a slow heart rate (32 bpm) and Right Bundle Branch Block (RBBB) morphology on ECG.
- Intravenous atropine administration was followed by a return to sinus rhythm (SR) with LBBB.
Findings:
- The case demonstrates a complete heart block with distinct aberrancy patterns during different rhythms (sinus vs. escape).
- Atropine effectively converted the rhythm, suggesting a transient block or a response to vagal tone modulation.
- Coronary angiography showed normal anatomy, ruling out significant atherosclerotic disease as the cause.
Implications:
- This case underscores the importance of recognizing dynamic ECG changes in complete atrioventricular block.
- It highlights the potential efficacy of atropine in certain AV block scenarios, although permanent pacing was still indicated.
- Understanding varying aberrancy patterns is crucial for accurate diagnosis and management of heart block.
Abstract:
We present a case of a complete atrioventricular block (AV block) with different aberrancy patterns during sinus rhythm and escape rhythm. A 66-year-old woman visited our emergency department complaining of sudden onset dizziness and fatigue over the past thirty minutes. Her medical history was remarkable for arterial hypertension, type 2 diabetes mellitus, and hypothyroidism. The patient had a known Left Bundle Branch Block (LBBB) on past ECGs. Upon palpation of peripheral pulse, a measurement of 32 beats per minute was obtained. No other sign of hemodynamic instability was present. A 12-Lead ECG revealed a complete heart block with sparse QRS complexes with a Right Bundle Branch Block (RBBB) morphology. Before the insertion of a temporary transvenous pacemaker, atropine was administered intravenously. Shortly after the administration, the patient's heart rhythm was restored to sinus rhythm (SR) with LBBB. The patient remained hemodynamically stable and in sinus rhythm at the cardiac ICU and was scheduled for implantation of a permanent pacemaker at a specialized tertiary center. Before successful implantation, a coronary angiography revealed normal coronary anatomy with no atherosclerotic lesions.

Related Concept Videos
 01:20
Bioequivalence Experimental Study Designs: Completely Randomized and Randomized Block Designs
 01:27
Anatomy of the Heart
 01:20
Pathophysiology of Diabetes
Type 1 diabetes is characterized by autoimmune-mediated destruction of pancreatic β cells, with environmental factors potentially triggering this process in genetically susceptible individuals. Despite many not having a family history, certain genes increase susceptibility,...
 01:19
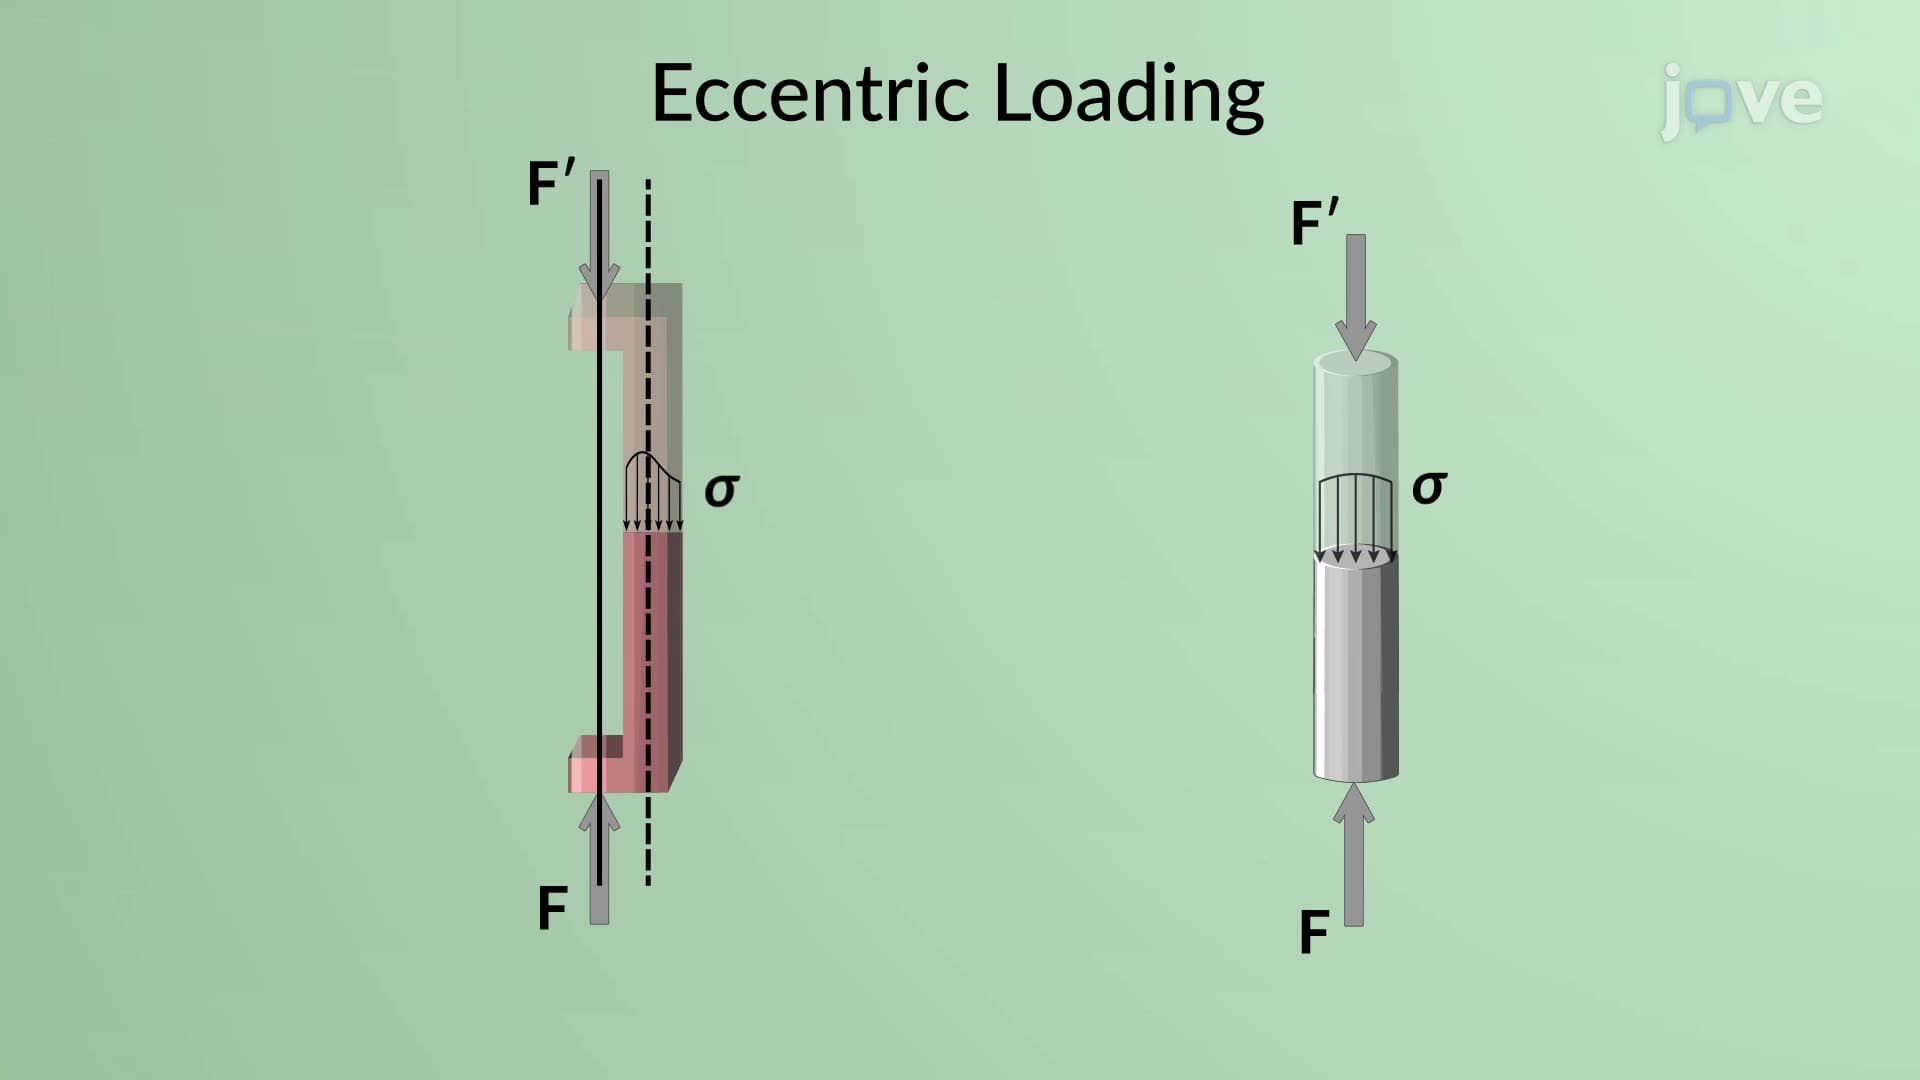
Normal Stress
When a rod is under axial loading, the internal forces and corresponding stress are normal to the plane of the section, so it is termed normal stress. It's important to...
 01:11
Normal Distribution
 01:21
Coronary Circulation
Coronary circulation begins at the base of the aorta, where two main arteries arise—the left and right coronary arteries. These arteries encircle the heart in the coronary sulcus and supply the...