Related Experiment Video
Updated: Jan 30, 2026


Generation of Murine Cardiac Pacemaker Cell Aggregates Based on ES-Cell-Programming in Combination with Myh6-Promoter-Selection
Published on: February 17, 2015
Cardiac toxicity of combined vemurafenib and cobimetinib administration

Abstract:
Vemurafenib and cobimetinib are extremely effective in treating V600E-mutated metastatic melanoma, but their use is associated with toxic cardiac effects. Vemurafenib-induced prolonged QTc interval may be associated with ventricular fibrillation and sudden cardiac death. Cobimetinib-induced myocardial damage may lead to severely reduced heart function and lethal heart failure. Few data are available about the time course of recovery after these side effects. We provide the first description of cardiac recovery after potentially fatal cardiac side effects due to vemurafenib and cobimetinib administration. A 51-year-old woman was admitted to our hospital with diarrhea, vomiting, and asthenia. At admission, her left ventricular ejection fraction (LVEF) was severely reduced and QTc interval was extremely elongated (normal range QTc ≤ 440 ms). Blood levels of troponin I (normal values below 0.07 ng/mL) and brain natriuretic peptide (brain natriuretic peptide (BNP), normal range < 100 pg/mL) were elevated. During hospitalization, she developed recurrent runs of torsades de pointes degenerating into ventricular fibrillation, requiring direct current electric shock (DC shocks). Vemurafenib and cobimetinib were discontinued. Three weeks later, QTc was still higher than 500 ms and LVEF lower than 30%: an implantable cardioverter-defibrillator (ICD) was implanted. Myocardial function improved within 1 month, and QTc intervals became 500 ms 1 week later. After 6 months, a normal ejection fraction (> 55%) was observed, and the QTc interval was 455 ms. The patient died rather from metastatic melanoma recurrence 8 months later. This case report highlights the time-course of recovery after combined vemurafenib-cobimetinib-induced severe myocardial damage. Further research is warranted to assess whether and how antineoplastic therapy may be resumed after QT normalization and heart function recovery. .
More Related Videos
 06:29
Cardiac Magnetic Resonance for the Evaluation of Suspected Cardiac Thrombus: Conventional and Emerging Techniques
Published on: June 11, 2019
 05:04
In vitro Assessment of Cardiac Reprogramming by Measuring Cardiac Specific Calcium Flux with a GCaMP3 Reporter
Published on: February 22, 2022
Related Concept Videos
 01:26
Toxic Reactions: Overview
Toxicity falls into two primary categories: local and systemic.
Local toxicity appears at the exposure site, such as protein denaturation caused by caustic substances.
In contrast, systemic toxicity requires the toxic agent's absorption and distribution,...
 01:22
Cardiac Output II: Effect of Stroke Volume on Cardiac Output
Preload
Preload refers to the initial elongation of the cardiac myocytes before contraction and is related to the volume of blood filling the heart at the end of diastole, or end-diastolic volume. The...
 01:18
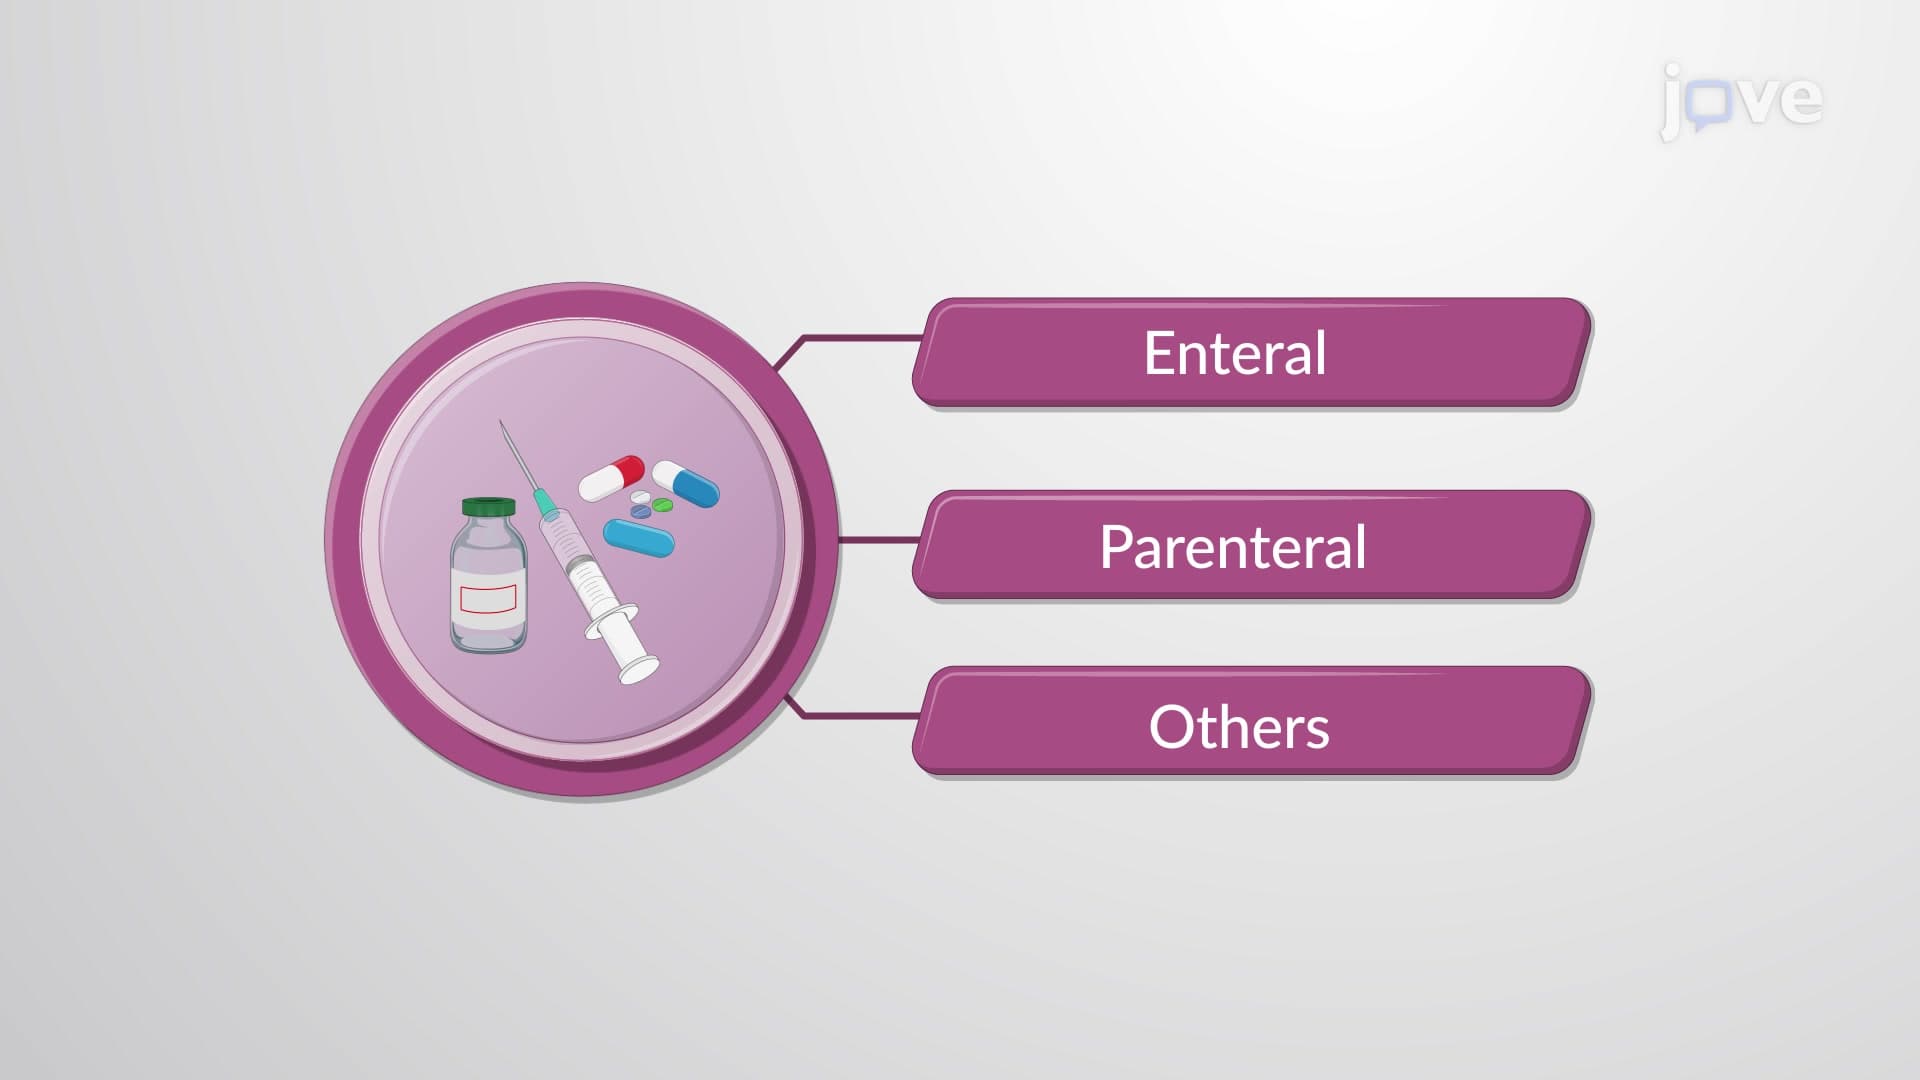
Additional Routes of Drug Administration
Administering drugs via inhalation allows for the direct delivery of gaseous, volatile substances or droplets to different parts of the respiratory tract. One of the advantages of the inhalation route is the rapid absorption of drugs into the circulatory system, which is possible because of the large surface area of...
 01:18
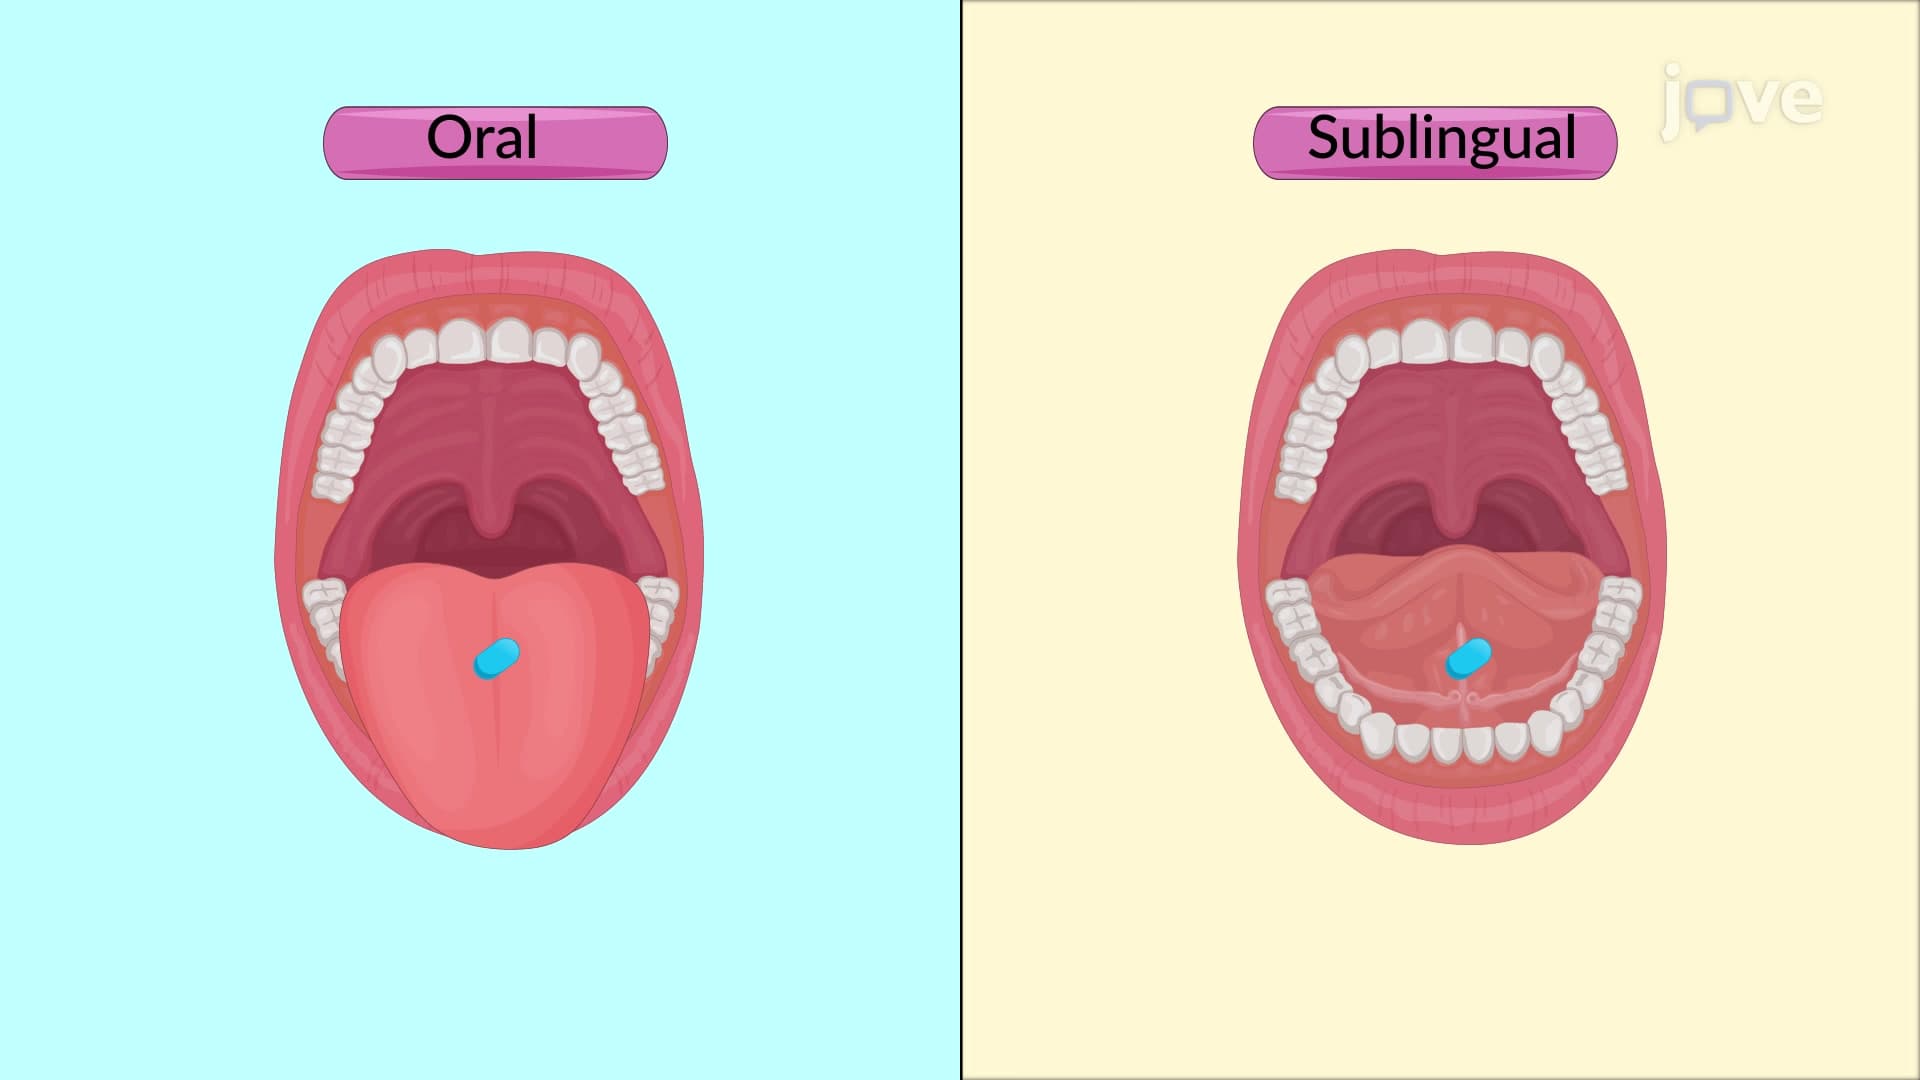
Routes of Drug Administration: Enteral
Enteral administration involves drug administration via the mouth in two ways: orally or sublingually.
Unlike sublingually drugs, drugs that are taken orally pass through the gastrointestinal (GI) tract and get metabolized by the liver. Once metabolized, the drug is absorbed into the systemic circulation, reaching different body parts via the bloodstream. However, while passing through the stomach,...
 01:19
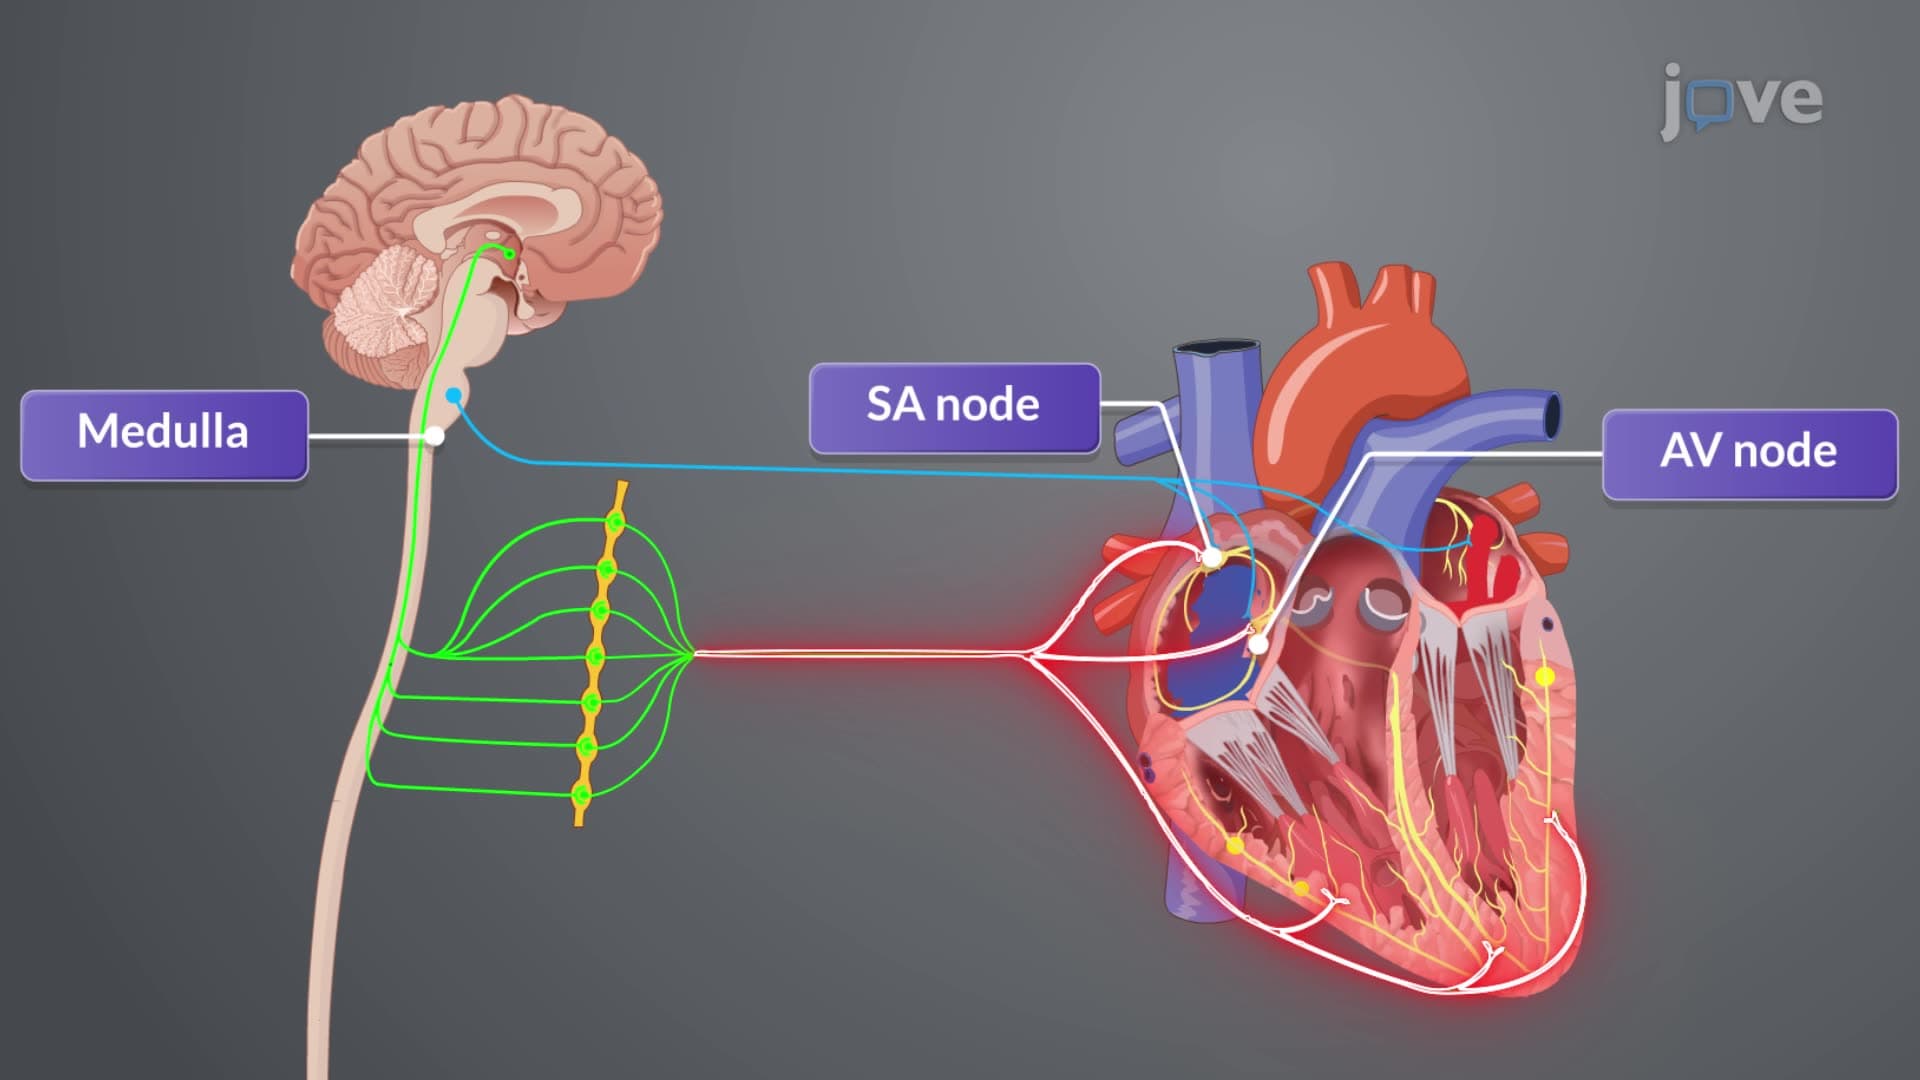
Cardiac Output I:Effect of Heart Rate on Cardiac Output
Cardiac output (CO) refers to the total amount of blood ejected by one of the ventricles in liters per minute (L/min). In a resting adult, CO ranges from 5 to 6 L/min, adjusting according to the body's metabolic requirements.
Effect of Heart Rate on Cardiac Output
Cardiac output adapts to metabolic demands during stress, physical activity, or illness. The autonomic nervous system regulates heart rate via the sinoatrial node. The parasympathetic nervous system decreases heart...
 01:13
The Cardiac Cycle
The Process
Electrical signals—sent from the sinoatrial (SA) node in the right atrial wall to the atrioventricular (AV) node between the right atrium and right ventricle—cause both atria to simultaneously contract. When the signal reaches the AV node, it pauses for approximately a tenth of a second, allowing the atria to contract and...