Related Experiment Video
Updated: Jan 29, 2026
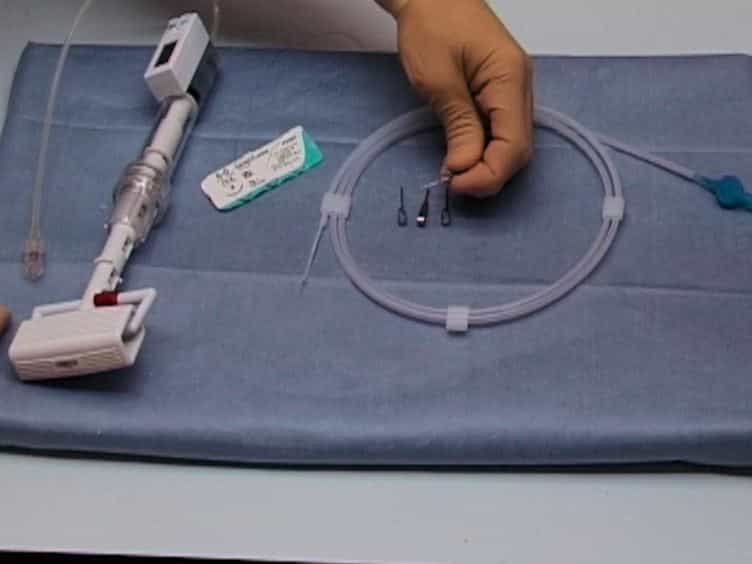

A New Murine Model of Endovascular Aortic Aneurysm Repair
Published on: July 7, 2013
The state of complex endovascular abdominal aortic aneurysm repairs in the Vascular Quality Initiative
Thomas F X O'Donnell1, Virendra I Patel2, Sarah E Deery3
1Division of Vascular and Endovascular Surgery, Beth Israel Deaconess Medical Center, Boston, Mass; Department of Surgery, Massachusetts General Hospital, Boston, Mass.

Insights
Complex endovascular aneurysm repair outcomes were analyzed using real-world data. Chimney/snorkel repairs showed higher perioperative stroke and major adverse cardiac event rates compared to FEVAR and PMEGs.
Area of Science:
- Vascular Surgery
- Endovascular Repair
- Aortic Aneurysm Treatment
Background:
- Endovascular repair of complex abdominal aortic aneurysms is increasingly common.
- Previous reports often limited to single centers and devices.
Purpose of the Study:
- To compare outcomes of different endovascular repair methods for complex abdominal aortic aneurysms.
- Utilize real-world data from the Vascular Quality Initiative.
Main Methods:
- Analysis of complex endovascular aneurysm repairs (zone 6 or caudal) from 2014-2018.
- Included fenestrated endovascular aneurysm repair (FEVAR), chimney/snorkel, and physician-modified endografts (PMEGs).
- Used inverse probability-weighted regression for perioperative outcomes and Cox regression for long-term mortality.
Main Results:
- 1396 complex endovascular repairs performed; 880 FEVAR, 256 PMEG, 260 chimney/snorkel.
- Chimney/snorkel repairs associated with higher rates of stroke (3.3% vs. <1%) and MACEs (11.7% vs. ~5.5%).
- Adjusted analysis confirmed significantly higher odds of stroke, myocardial infarction, and MACEs for chimney/snorkel repairs.
Conclusions:
- Real-world data from VQI offers insights into complex endovascular aneurysm repair outcomes.
- Perioperative morbidity appears higher with chimney/snorkel repair.
- Further studies needed to confirm findings and assess long-term durability.
Background:
Endovascular repair of complex abdominal aortic aneurysms has become increasingly common, but reports have mostly been limited to single centers and single devices.
Methods:
We studied all endovascular repairs of complex abdominal aortic aneurysms (zone 6 or caudal) from 2014 to 2018 in the Vascular Quality Initiative. This included all commercially available fenestrated endovascular aneurysm repair (FEVAR), chimney/snorkel repairs, and physician-modified endografts (PMEGs), exclusive of investigational device exemptions and clinical trial devices. We used inverse probability-weighted multilevel logistic regression to compare rates of perioperative outcomes including death, acute kidney injury (AKI), and major adverse cardiac events (MACEs; the composite of death/stroke/myocardial infarction) and Cox regression for long-term mortality.
Results:
During the study period, surgeons performed 1396 complex endovascular repairs: 1308 (94%) elective, 63 (4.5%) for symptomatic aneurysms, and 25 (1.8%) for rupture. The number of centers performing complex endovascular repairs expanded steadily from 39 in 2014 to 81 in 2017. There were 880 FEVAR (63%), 256 PMEG (18%), and 260 chimney/snorkel repairs (19%). In elective cases, 3214 visceral vessels were incorporated and revascularized; 120 repairs (9%) involved one vessel, 481 (38%) repairs involved two vessels, 560 (44%) involved three vessels, and 113 (9%) involved four vessels. The mean number of arteries incorporated was 2.5 ± 0.8, with PMEGs involving the most arteries (3.3 ± 0.8 for PMEG vs 2.5 ± 0.6 for FEVAR and 1.9 ± 0.9 for chimney/snorkel; P < .001). PMEGs were used to treat more extensive aneurysms, and more incorporated the celiac and superior mesenteric arteries. There was no change in aneurysm extent, but the length of proximal seal extended over time. Chimney/snorkel cases employed more arm or neck access, had longer procedure times, and used more contrast material. Rates of perioperative death (3.4% for FEVAR vs 2.7% for PMEG vs 6.1% for chimney/snorkel; P = .13) and AKI (17% vs 18% vs 19%; P = .42) were similar, but chimney/snorkel was associated with higher rates of stroke (0.8% vs 0.9% vs 3.3%; P = .03) and MACEs (6.1% vs 5.4% vs 11.7%; P = .02). After adjustment, rates of perioperative death, AKI, and overall complications remained similar, but chimney/snorkel was associated with significantly higher odds of stroke (odds ratio [OR], 7.3 [1.5-36.4]; P = .015), myocardial infarction (OR, 18.7 [2.6-136.8]; P = .004), and MACEs (OR, 11.1 [2.1-58.9]; P = .005). Overall survival after elective repair was 91% at 1 year and 88% at 3 years, with no difference between repair types in crude or adjusted analysis.
Conclusions:
The Vascular Quality Initiative provides a unique opportunity to study the real-world application and outcomes of complex endovascular aneurysm repair. Perioperative morbidity appears to be higher after chimney/snorkel repair, but further study is needed to confirm these findings and to establish the durability of these novel technologies.

Related Concept Videos
 02:33
Initiation of Translation
First, the initiator tRNA must be selected from the pool of elongator tRNAs by eukaryotic initiation factor 2 (eIF2). The initiator tRNA (Met-tRNAi) has conserved sequence elements including modified bases at...
02:33Initiation of Translation
 01:08
Nucleotide Excision Repair
 01:36
Mismatch Repair
 02:25
Overview of DNA Repair
Chemically...
 01:54
Base Excision Repair
The first step of...