Cefepime Pharmacokinetics in Critically Ill Pediatric Patients Receiving Continuous Renal Replacement Therapy
Related Experiment Video
Updated: Jan 29, 2026
Manual Muscle Testing: A Method of Measuring Extremity Muscle Strength Applied to Critically Ill Patients
Published on: April 12, 2011
Gideon Stitt1,2, Jennifer Morris2, Lindsay Schmees2
1Department of Pharmacy Services, Children's Hospital of Philadelphia, Philadelphia, Pennsylvania, USA stittg@email.chop.edu.

Insights
Critically ill children on continuous veno-venous hemodiafiltration (CVVHDF) receiving cefepime achieved target drug levels. Therapeutic drug monitoring is recommended for cefepime dosing in pediatric intensive care unit patients undergoing CVVHDF.
Area of Science:
- Pharmacokinetics and Pharmacodynamics
- Critical Care Medicine
- Pediatric Nephrology
Background:
- Continuous veno-venous hemodiafiltration (CVVHDF) is a common renal replacement therapy in pediatric intensive care units.
- Cefepime is a frequently used antibiotic in critically ill children.
- The optimal dosing of cefepime during CVVHDF in pediatric patients is not well established.
Purpose of the Study:
- To evaluate the pharmacokinetic/pharmacodynamic (PK/PD) targets of cefepime in pediatric intensive care unit patients undergoing CVVHDF.
- To assess the achievement of target free cefepime concentrations (fT>1xMIC and fT>4xMIC) in this patient population.
Main Methods:
- Retrospective study of pediatric intensive care unit patients receiving cefepime during CVVHDF.
- Calculation of free drug concentration above one time the minimum inhibitory concentration (MIC) (fT>1xMIC) and four times a presumed MIC (fT>4xMIC) of 8 μg/ml.
- Analysis of cefepime doses administered (48 to 64 mg/kg every 6 to 12 hours).
Main Results:
- Three out of four patients achieved 100% fT>1xMIC.
- The fourth patient achieved 98% fT>1xMIC.
- All patients received cefepime doses ranging from 48 to 64 mg/kg every 6 to 12 hours.
Conclusions:
- The studied cefepime dosing regimens were generally effective in achieving target PK/PD exposures in pediatric patients on CVVHDF.
- Therapeutic drug monitoring should be considered to optimize cefepime therapy in critically ill pediatric patients receiving CVVHDF.
- Further studies are warranted to confirm optimal dosing strategies.
Abstract:
This retrospective study included pediatric intensive care unit patients receiving continuous veno-venous hemodiafiltration (CVVHDF) being treated with cefepime. The free drug concentration above one time the MIC (fT>1×MIC) and four times a presumed MIC (fT>4×MIC) of 8 μg/ml were calculated. Four patients received doses ranging from 48 to 64 mg/kg of body weight every 6 to 12 h. Three patients achieved 100% fT>1×MIC, with the fourth patient achieving 98% fT>1×MIC. Therapeutic drug monitoring should be considered for critically ill patients receiving cefepime on CVVHDF.

Related Concept Videos
 01:30
Continuous Renal Replacement Therapy
 01:26
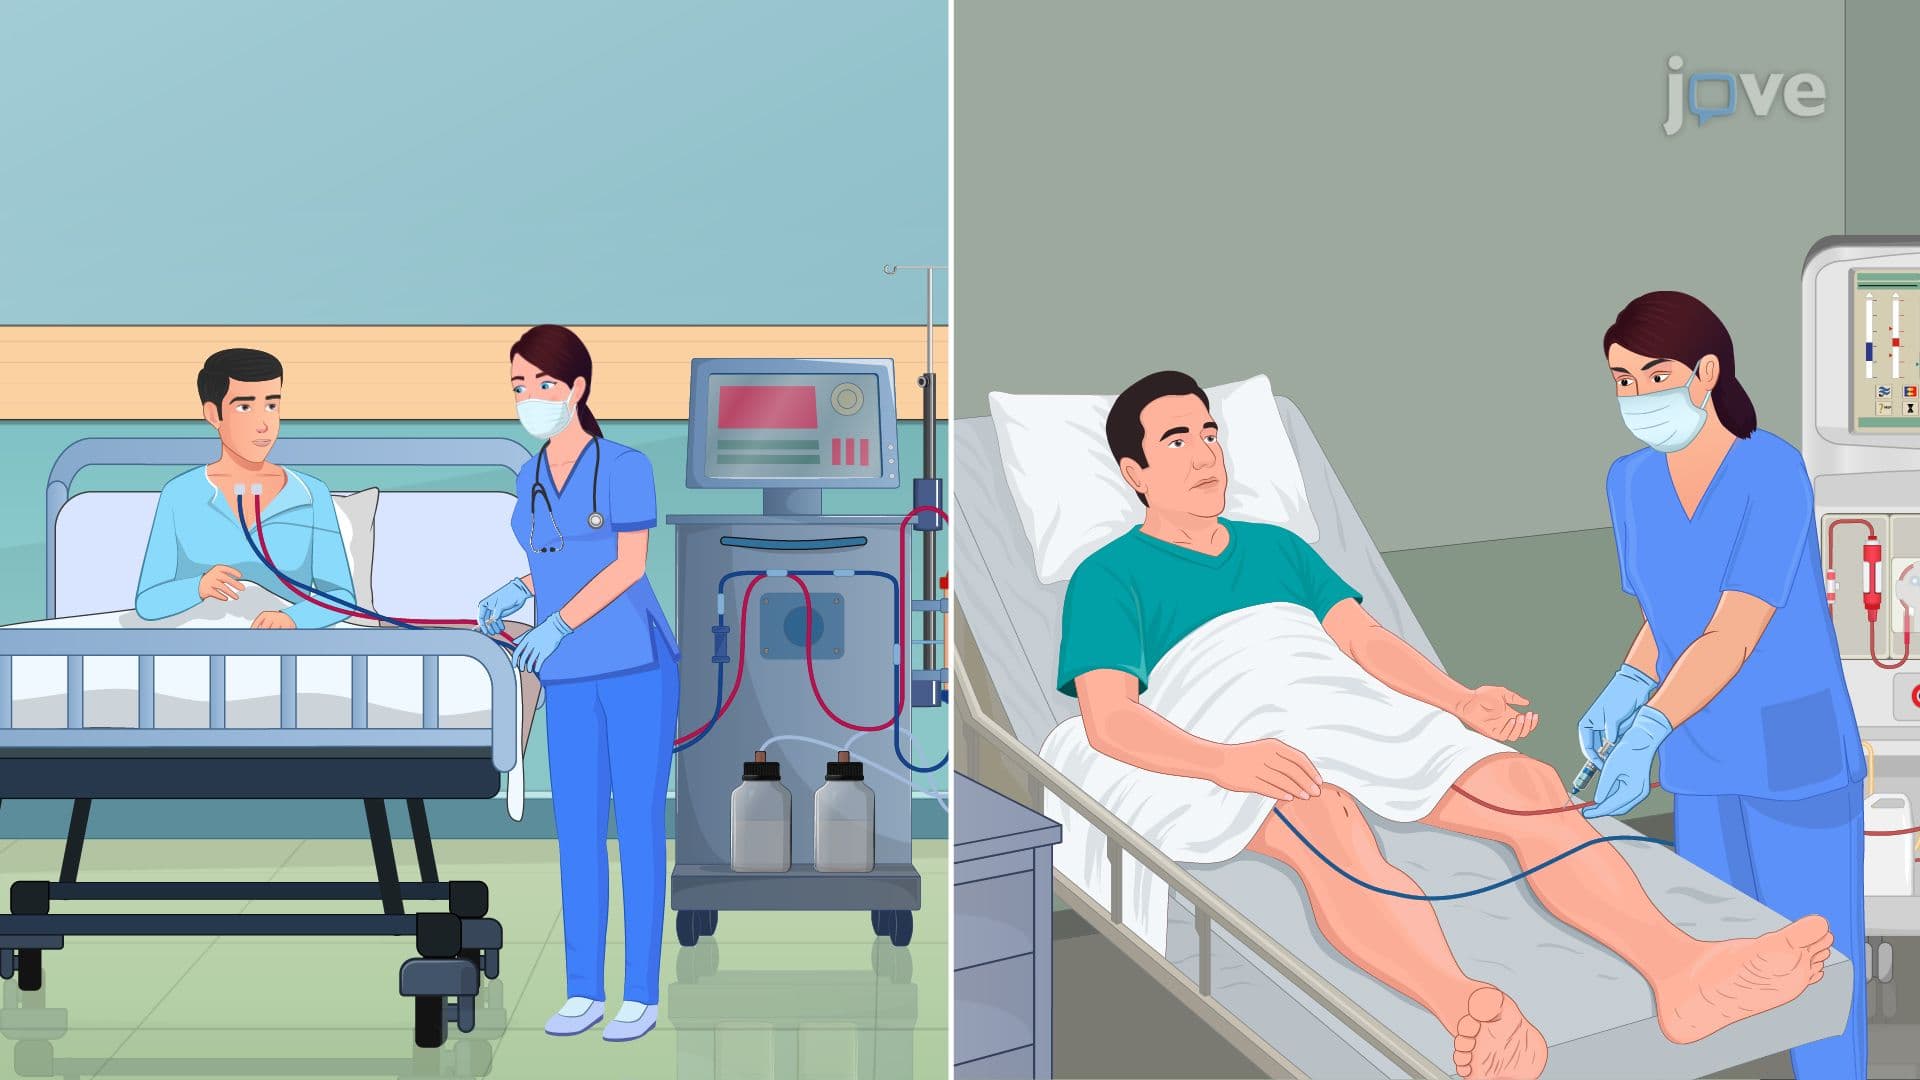
Extracorporeal Removal of Drugs: Continuous Renal Replacement Therapy
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion
 01:17
Pharmacokinetics in Pediatric Patients: Drug Distribution
 01:24
Pharmacokinetics in Pediatric Patients: Drug Metabolism
 01:23
Pharmacokinetics in Pediatric Patients: Overview and Drug Absorption