Related Experiment Video
Updated: Jan 29, 2026
An Effective Mouse Model of Unilateral Renal Ischemia-Reperfusion Injury
Published on: July 15, 2021
Cardioprotective Effects of Beta3-Adrenergic Receptor (β3-AR) Pre-, Per-, and Post-treatment in Ischemia-Reperfusion
Ruduwaan Salie1,2, Aisha Khlani Hassan Alsalhin3, Erna Marais3
1Biomedical Research and Innovation Platform, South African Medical Research Council, Building D, Medicina, Francie van Zijl Drive, Parow Valley, Cape Town, Western Cape, South Africa. ruduwaan.salie@mrc.ac.za.

Abstract:
The β3-AR (beta3-adrenergic receptor) is resistant to short-term agonist-promoted desensitization and delivers a constant intracellular signal, making this receptor a potential target in acute myocardial infarction (AMI).
Aim:
To investigate whether selective modulation of β3-AR prior to or during ischemia and/or reperfusion may be cardioprotective.
Methods:
Isolated perfused rat hearts were exposed to 35-min regional ischemia (RI) and 60-min reperfusion. The β3-AR agonist (BRL37344, 1 μM) or antagonist (SR59230A, 0.1 μM) was applied: (i) before RI (PreT) or (ii) last 10 min of RI (PerT) or (iii) onset of reperfusion (PostT) or (iv) during both PerT+PostT. Nitric oxide (NO) involvement was assessed, using the NOS inhibitor, L-NAME (50 μM). Endpoints were functional recovery, infarct size (IS), cGMP levels, and Western blot analysis of eNOS, ERKp44/p42, PKB/Akt, and glycogen synthase kinase-3β (GSK-3β).
Results:
Selective treatment with BRL significantly reduced IS. L-NAME abolished BRL-mediated cardioprotection. BRL (PreT) and BRL (PerT) significantly increased cGMP levels (which were reduced by L-NAME) and PKB/Akt phosphorylation. BRL (PostT) produced significantly increased cGMP levels, PKB/Akt, and ERKp44/p42 phosphorylation. BRL (PerT+PostT) caused significant eNOS, PKB/Akt, ERKp44/p42, and GSK-3β phosphorylation.
Conclusion:
β3-AR activation by BRL37344 induced significant cardioprotection regardless of the experimental protocol. However, the pattern of intracellular signaling with each BRL treatment differed to some degree and suggests the involvement of cGMP, eNOS, ERK, GSK-3β, and particularly PKB/Akt activation. The data also suggest that clinical application of β3-AR stimulation should preferably be incorporated during late ischemia or/and early reperfusion.
Insights
Beta3-adrenergic receptor (β3-AR) activation protects the heart during acute myocardial infarction (AMI). Selective β3-AR stimulation, particularly during late ischemia or early reperfusion, offers significant cardioprotection.
Area of Science:
- Cardiovascular Pharmacology
- Myocardial Ischemia/Reperfusion Injury
Background:
- The beta3-adrenergic receptor (β3-AR) is resistant to desensitization, offering a constant intracellular signal.
- This characteristic makes β3-AR a promising therapeutic target for acute myocardial infarction (AMI).
Purpose of the Study:
- To investigate the cardioprotective potential of selective β3-AR modulation.
- To determine the optimal timing for β3-AR intervention during ischemia and/or reperfusion.
Main Methods:
- Isolated perfused rat hearts subjected to regional ischemia and reperfusion.
- Administration of a β3-AR agonist (BRL37344) or antagonist (SR59230A) at various time points: before ischemia, during late ischemia, or during reperfusion.
- Assessment of functional recovery, infarct size, cGMP levels, and key signaling proteins (eNOS, ERK, Akt, GSK-3β).
- Evaluation of nitric oxide (NO) involvement using L-NAME.
Main Results:
- Selective β3-AR agonist treatment significantly reduced infarct size.
- Cardioprotection was abolished by L-NAME, indicating a role for nitric oxide.
- Agonist administration increased cGMP levels and phosphorylation of signaling proteins, including PKB/Akt, with varying patterns depending on treatment timing.
- β3-AR activation induced significant cardioprotection irrespective of the specific intervention timing.
Conclusions:
- β3-AR activation confers significant cardioprotection in a rat model of myocardial infarction.
- The cardioprotective effects involve cGMP, nitric oxide, and activation of signaling pathways like PKB/Akt.
- Optimal clinical application of β3-AR stimulation may involve targeting late ischemia and/or early reperfusion phases.

Related Concept Videos
 01:27
Adrenergic Receptors (Adrenoceptors): Classification
α-Adrenoceptors
α-Adrenoceptors are classified into two main subtypes: α1 and α2. The α1 adrenoceptors,...
 01:31
Adrenergic Receptors: ɑ Subtype
Adrenaline ≥ Noradrenaline >> Isoprenaline
α-adrenoceptors are further divided into α1 and α2-adrenoceptors.
α1-Adrenoceptors: These receptors are located postsynaptically on the effector organs and cause constriction of smooth muscle mediated by activation of phospholipase...
 01:26
Adrenergic Receptors: β Subtype
Isoprenaline > Adrenaline > Noradrenaline
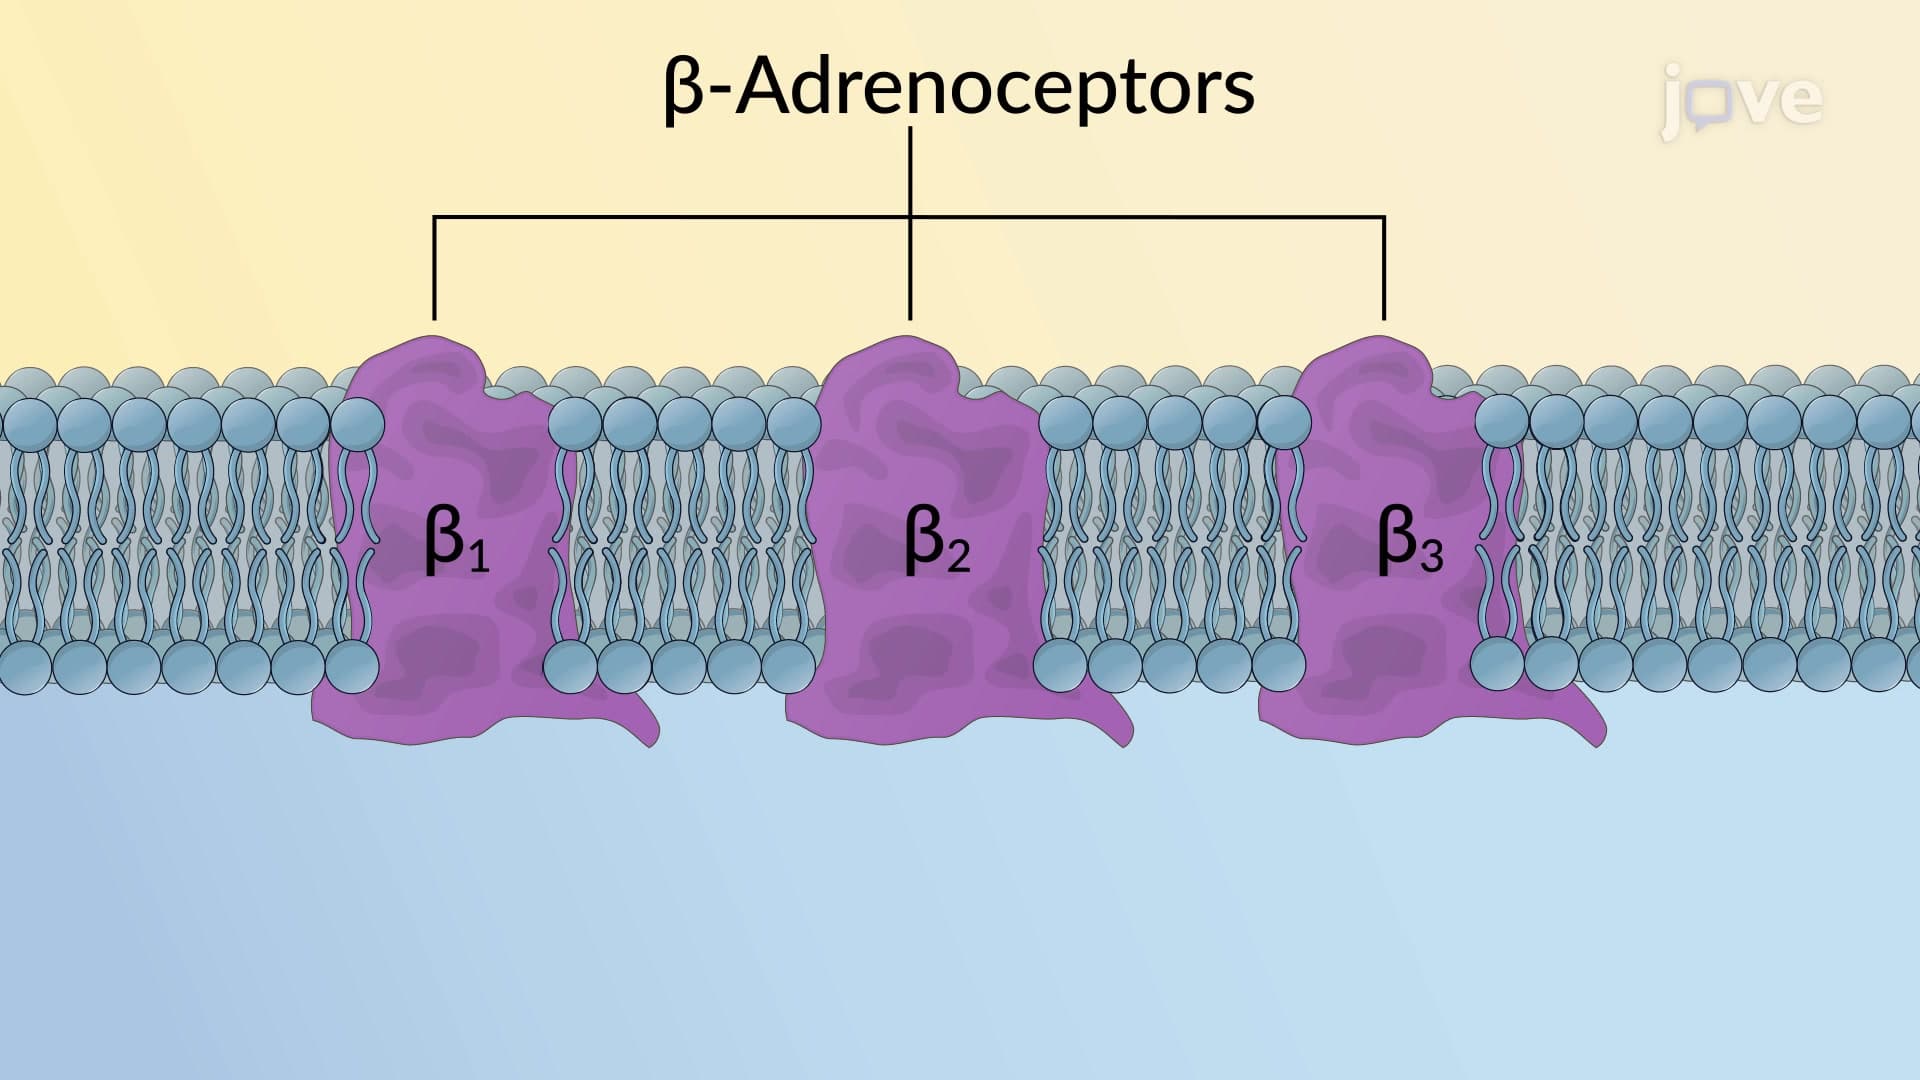
Neurotransmitter binding to these receptors causes activation of adenylyl cyclase resulting in increased concentrations of cAMP and modulation of calcium ion channels within the cell. They are further classified into β1, β2, and β3 subtypes.
β1-adrenoceptors: β1-adrenoceptors...
 01:31
Adrenergic Antagonists: ɑ and β-Receptor Blockers
 01:28
Cardiomyopathy VII: Pre and Post Operative Nursing Management
 01:22
Adrenergic Antagonists: Pharmacological Actions of ɑ-Receptor Blockers
α1-blockers: These drugs inhibit α1-adrenoceptors on smooth muscle cells, resulting in vasodilation. This vasodilation lowers blood pressure, making α1-blockers valuable in treating hypertension. Additionally,...