Related Experiment Video
Updated: Jan 29, 2026


Author Spotlight: Exploring the Long-Term Health Impacts of Intracytoplasmic Sperm Injection on Offspring
Published on: May 17, 2024
ICSI outcomes using testicular spermatozoa in non-azoospermic couples with recurrent ICSI failure and no previous
M B Herrero1, M F Lusignan2, W-Y Son1
1MUHC Reproductive Centre, McGill University Health Centre, Montreal, QC, Canada.

Background:
The use of testicular over ejaculated spermatozoa for ICSI has been presented as an alternative to overcome infertility in men with poor semen parameters or high levels of sperm DNA fragmentation.
Objective:
To evaluate the efficacy of testicular ICSI outcomes in couples with no previous live birth and recurrent ICSI failure using ejaculated spermatozoa by comparison to the outcomes of couples with similar history of recurrent ICSI using ejaculated spermatozoa only.
Materials And Methods:
A total of 145 couples undergoing ejaculated or testicular ICSI cycles with no previous live births and with at least two previous failed ICSI cycles with ejaculated spermatozoa were evaluated retrospectively. ICSI was performed either with ejaculated (E-ICSI) or with testicular (T-ICSI) spermatozoa. Semen parameters and sperm DNA quality were assessed prior to the oocyte collection day. Primary outcomes included cumulative live birth and pregnancy rates. Secondary analysis included percentage of DNA fragmentation in ejaculated spermatozoa (SCSA® and TUNEL).
Results:
Patients undergoing T-ICSI (n = 77) had a significantly higher clinical pregnancy rate/fresh embryo transfer (ET) (27.9%; 17/61) and cumulative live birth rate (23.4%; 15/64) compared to patients using E-ICSI (n = 68) (clinical pregnancy rate/fresh ET: 10%; 6/60 and cumulative live birth rate: 11.4%; 7/61). Further, T-ICSI yield significantly better cumulative live birth rates than E-ICSI for men with high TUNEL (≥36%) (T-ICSI: 20%; 3/15 vs. E-ICSI: 0%; 0/7, p < 0.025), high SCSA® (≥25%) scores (T-ICSI: 21.7%; 5/23 vs. E-ICSI: 9.1%; 1/11, p < 0.01), or abnormal semen parameters (T-ICSI: 28%; 7/25 vs. E-ICSI: 6.7%; 1/15, p < 0.01).
Conclusions:
The use of testicular spermatozoa for ICSI in non-azoospermic couples with no previous live births, recurrent ICSI failure, and high sperm DNA fragmentation yields significantly better live birth outcomes than a separate cohort of couples with similar history of ICSI failure entering a new ICSI cycle with ejaculated spermatozoa.

Related Concept Videos
 01:22
Birth Control Methods
 02:24
Predicting Reaction Outcomes
 01:13
Outcomes of Glycolysis
Cellular respiration can occur aerobically (with oxygen) or anaerobically (without oxygen). In the presence of oxygen, cellular respiration starts with glycolysis and continues with pyruvate...
 01:20
Spin–Spin Coupling: Two-Bond Coupling (Geminal Coupling)
The central atom need not be NMR-active because its electrons are affected by the electron polarization of the spin-active atoms. However, spin information is transmitted less effectively than in one-bond coupling, and 2J values are usually weaker than 1J values. The energy of...
 01:22
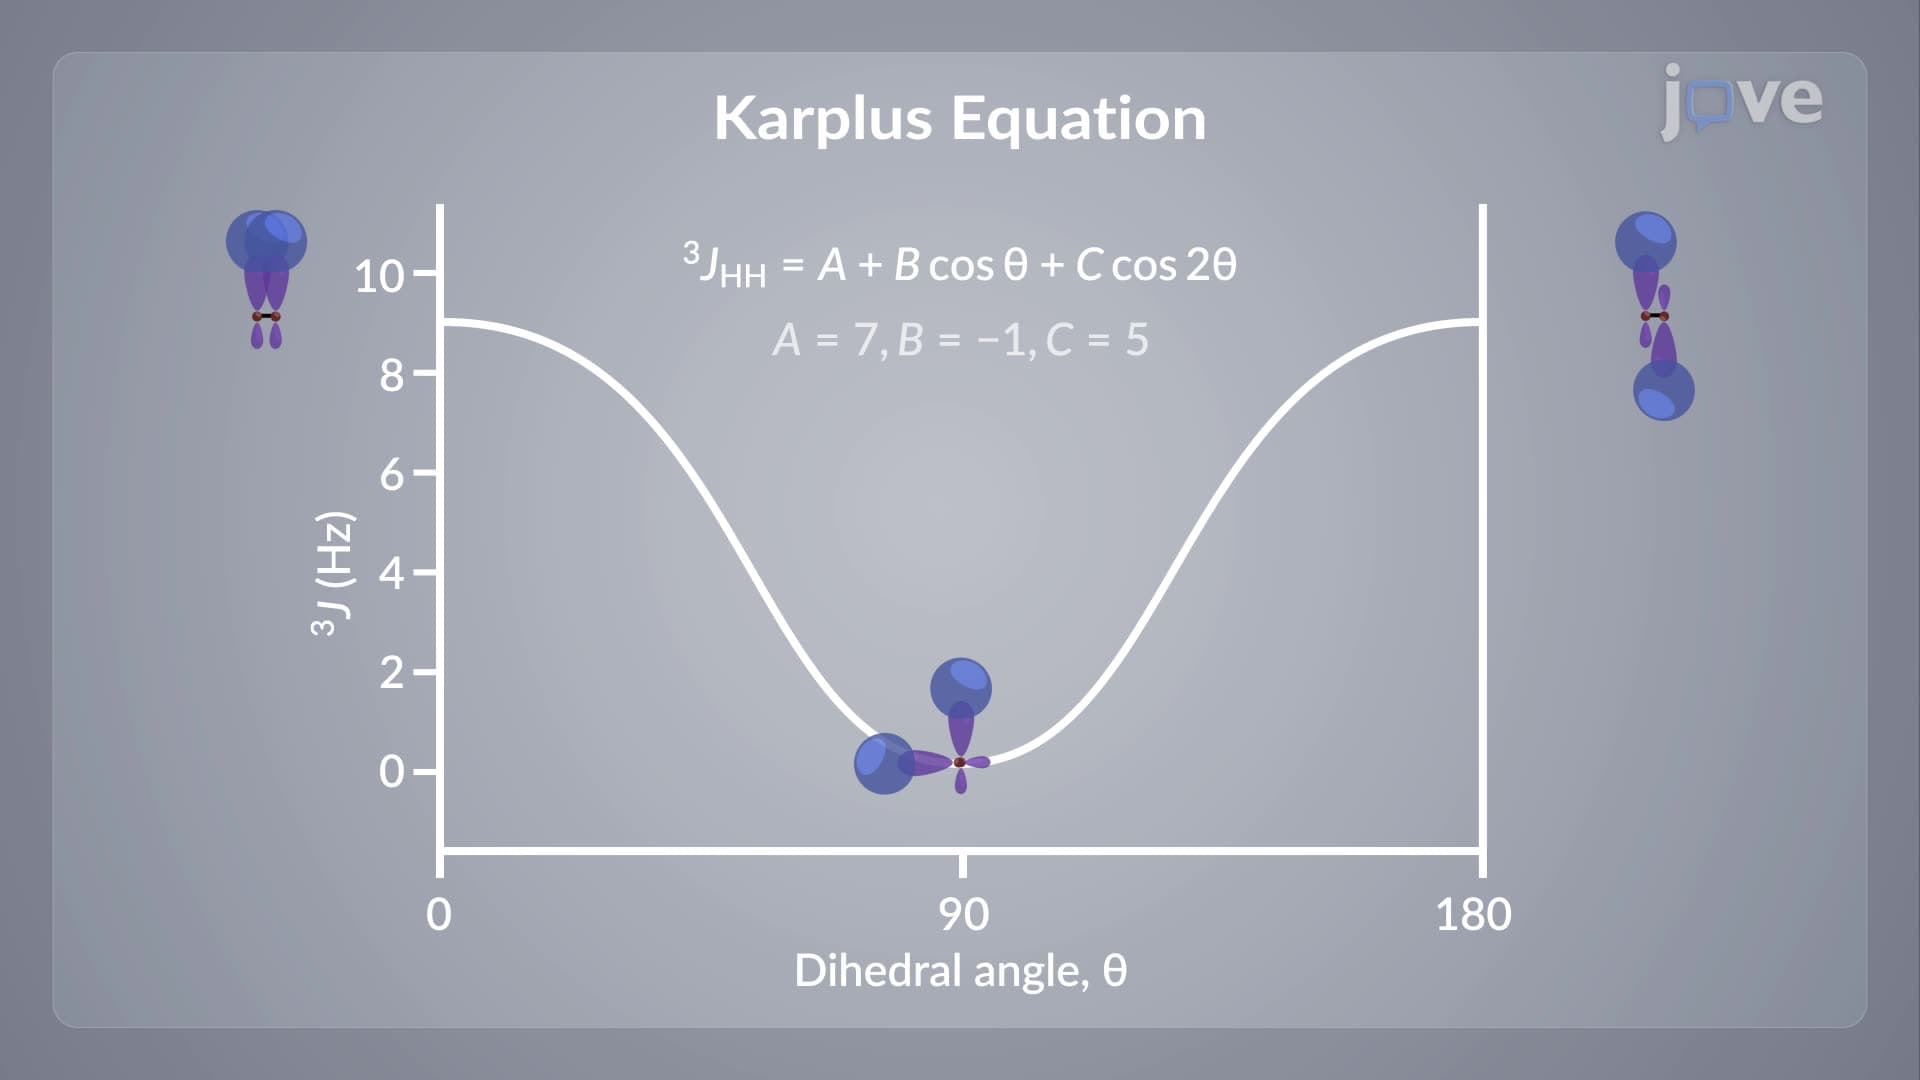
Spin–Spin Coupling: Three-Bond Coupling (Vicinal Coupling)
The extent of coupling depends on the C‑C bond length, the two H‑C‑C angles, any electron-withdrawing substituents, and the dihedral angle between the involved orbitals. The...
 01:11
Guidelines for Writing Outcome
Patient outcomes reflect the patient's response to the goal rather than what the nurse aims to achieve. Terminology should be observable and measurable to avoid the reader's interpretation. The desired outcome should be realistic and achievable in the designated care timeframe. Expected outcomes should align with adjunctive therapies. The outcome should enhance care...