

Impact of Degree of Left Ventricular Remodeling on Clinical Outcomes From Cardiac Resynchronization Therapy
Fadi Shamoun1, Teresa De Marco2, David DeMets3
1Department of Cardiovascular Diseases, Mayo Clinic Arizona, Scottsdale, Arizona.

Insights
Patients with larger left ventricular dimensions (LVEDDI ≥35 mm/m²) experienced reduced all-cause mortality and heart failure hospitalizations with cardiac resynchronization therapy (CRT). Smaller LVEDDI (<35 mm/m²) did not show significant benefits from CRT for these outcomes.
Area of Science:
- Cardiology
- Heart Failure Research
- Medical Device Technology
Background:
- The influence of left ventricular (LV) structural remodeling severity on cardiac resynchronization therapy (CRT) effectiveness in heart failure with reduced ejection fraction (HFrEF) remains unclear.
- Understanding this relationship is crucial for optimizing CRT patient selection and predicting treatment outcomes.
Purpose of the Study:
- To investigate the association between the extent of LV eccentric structural remodeling, quantified by left ventricular internal dimensions at end diastole indexed by body surface area (LVEDDI), and clinical event responses to CRT in HFrEF patients.
- To determine if LVEDDI influences the efficacy of CRT compared to optimal pharmacologic therapy (OPT).
Main Methods:
- Retrospective analysis of data from the Comparison of Medical Therapy, Pacing and Defibrillation in Heart Failure (COMPANION) trial.
- Patients were stratified based on pre-randomization LVEDDI values (median cutoff of 35 mm/m²).
- CRT (CRT-P and/or CRT-D) treatment effects were compared to OPT for outcomes of all-cause mortality (ACM) or ACM and heart-failure hospitalization (ACM/HFH).
Main Results:
- In patients with LVEDDI ≥35 mm/m², CRT was associated with a significantly lower risk of ACM/HFH compared to OPT (HR: 0.53; p <0.001).
- For ACM alone, CRT-P and CRT-D showed significant reductions in the LVEDDI ≥35 mm/m² group (HRs 0.59 and 0.50, respectively; p <0.012 and p <0.002).
- In contrast, patients with LVEDDI <35 mm/m² did not demonstrate statistically significant improvements in ACM/HFH or ACM with CRT compared to OPT.
Conclusions:
- Larger LVEDDIs are associated with significant reductions in ACM and ACM/HFH when treated with CRT (CRT-P or CRT-D).
- The combined CRT treatment groups showed more effective reduction in ACM/HFH in patients with larger LVEDDIs.
- LV remodeling extent, as indicated by LVEDDI, is an important factor in predicting CRT response in HFrEF.
Objectives:
This study tested the hypothesis that the extent of left ventricular (LV) eccentric structural remodeling in heart failure with reduced ejection fraction (HFrEF) is directly associated with clinical event responses to cardiac resynchronization therapy (CRT).
Background:
Whether the severity of LV structural remodeling influences CRT treatment effects is unknown.
Methods:
COMPANION (Comparison of Medical Therapy, Pacing and Defibrillation in Heart Failure) trial data were analyzed retrospectively. Left ventricular internal dimensions at end diastole indexed by body surface area (LVEDDI) were measured pre-randomization by 2-dimensional echocardiography. LVEDDI values were stratified around the median value of 35 mm/m2, and CRT (including CRT-P [CRT with only pacing capability] and/or CRT-D [CRT with an implantable defibrillator]) treatment effects were assessed and compared by LVEDDI group. Patients assigned to these treatments were compared to those undergoing optimal pharmacologic therapy (OPT) for the outcomes of all-cause mortality (ACM) or ACM and heart-failure hospitalization (ACM/HFH).
Results:
In the LVEDDI ≥35 mm/m2 group (n = 614), CRT vs. OPT was associated with a lower ACM/HFH hazard ratio (HR) (HR: 0.53; 95% confidence interval [CI]: 0.40 to 0.70; p <0.001), whereas in the LVEDDI <35 mm/m2 group, the CRT vs. OPT ACM/HFH hazard ratio was not statistically significant (HR: 0.80; 95% CI: 0.59 to 1.08; p = 0.15). For ACM alone, in the LVEDDI ≥35 mm/m2 group, the hazard ratio for CRT-P was 0.59 (95% CI: 0.39 to 0.90; p = 0.012) and for CRT-D 0.50 (95% CI: 0.32 to 0.77; p = 0.002). Neither of the CRT groups showed a statistically significant reduction in ACM in the LVEDDI <35 mm/m2 group.
Conclusions:
Larger versus smaller LVEDDIs are associated with a reduction in ACM with CRT-P or CRT-D treatment, and with a more effective reduction in ACM/HFH for the combined CRT treatment groups.


Related Concept Videos
 02:54
Nucleosome Remodeling
Nucleosome remodeling complex
Eukaryotic cells have specialized enzymes called ATP-dependent nucleosome remodeling enzymes. These enzymes...
 01:24
Cardiac Catheterization III: Left Heart Catheterization
 01:24
One-Degree-of-Freedom System
A one-degree-of-freedom system is defined by an independent variable that determines its state and behavior. One example of a one-degree-of-freedom system is a simple harmonic oscillator, such as a...
 01:02
Degrees of Freedom
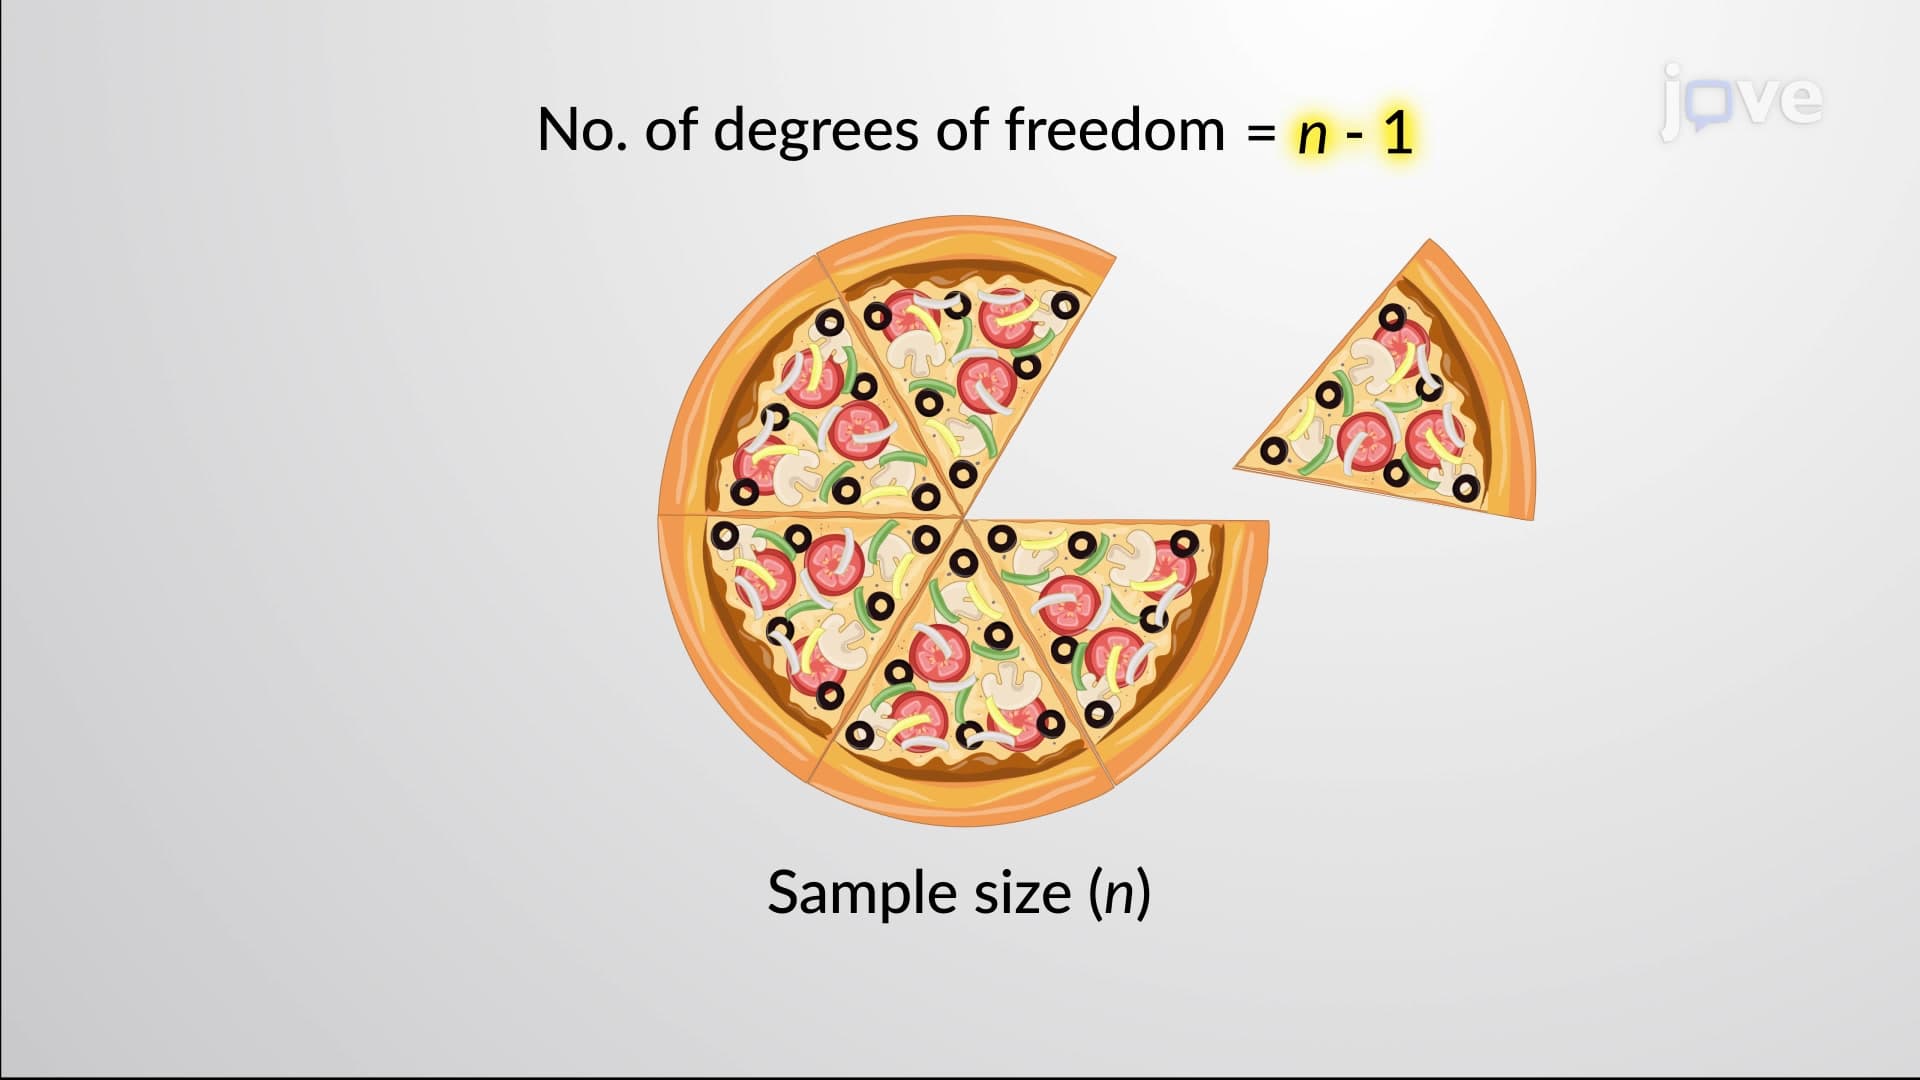
For example, suppose there are three unknown numbers whose mean is 10; although we can freely assign values to the first and second numbers, the value of the last number can not be arbitrarily assigned.
 01:02
Degrees of Freedom
For example, suppose there are three unknown numbers whose mean is 10; although we can freely assign values to the first and second numbers, the value of the last number can not be arbitrarily...
 02:05
Degree of Unsaturation
The degree of unsaturation for hydrocarbons is U = (2C + 2 − H) / 2, where C is the number of carbon atoms and H is the number of hydrogen atoms.