Related Experiment Video
Updated: Jan 29, 2026

Intraoperative Gastroscopy for Tumor Localization in Laparoscopic Surgery for Gastric Adenocarcinoma
Published on: August 9, 2016
Internal hernia after gastrectomy for gastric cancer in minimally invasive surgery era
Kyong Min Kang1, Yo Seok Cho1, Sa-Hong Min1
1Department of Surgery, Seoul National University Bundang Hospital, 82 Gumi-ro 173beon-gil, Bundang-gu, Seongnam, 13620, South Korea.

Background:
The incidence and clinical presentation of internal hernia after gastrectomy have been changing in the minimally invasive surgery era. This study aimed to analyze the clinical features and risk factors for internal hernia after gastrectomy for gastric cancer.
Methods:
We retrospectively analyzed internal hernia after gastrectomy for gastric cancer in 6474 patients between January 2003 and December 2016 at Seoul National University Bundang Hospital. Multivariable logistic regression was performed to evaluate risk factors.
Results:
Internal hernias identified by computed tomography or surgical exploration were 111/6474 (1.7%) and the median interval time was 450 days after gastrectomy. Fourteen (0.9%) of the 1510 patients who underwent open gastrectomy and 97 (2.0%) of the 4964 patients who underwent laparoscopic gastrectomy developed internal hernia. Of the 6474 patients, internal hernia developed in 0 (0%), 9 (1.1%), 40 (3.1%), 56 (3.3%), 6 (2.3%), and 0 (0%) patients who underwent Billroth I, Billroth II, Roux-en-Y, uncut Roux-en-Y, double tract, and esophagogastrostomy reconstructions, respectively. Fifty-nine (53.2%) of 111 patients with symptomatic hernia underwent surgery. Of the 59 internal hernias, treated surgically, 32 (53.2%), 27 (45.8%), and 0 (0%) were identified in jejunojejunostomy mesenteric, Petersen's, and transverse colon mesenteric defects, respectively. In multivariate analysis, non-closure of mesenteric defects (P < 0.01), laparoscopic approach (P < 0.01), and totally laparoscopic approach (P = 0.03) were independent risk factors for internal hernia.
Conclusions:
The potential spaces such as Petersen's, jejunojejunostomy mesenteric, and transverse colon mesenteric defects should be closed to prevent internal hernia after gastrectomy for gastric cancer.

Related Concept Videos
 02:00
Internal Energy
 01:29
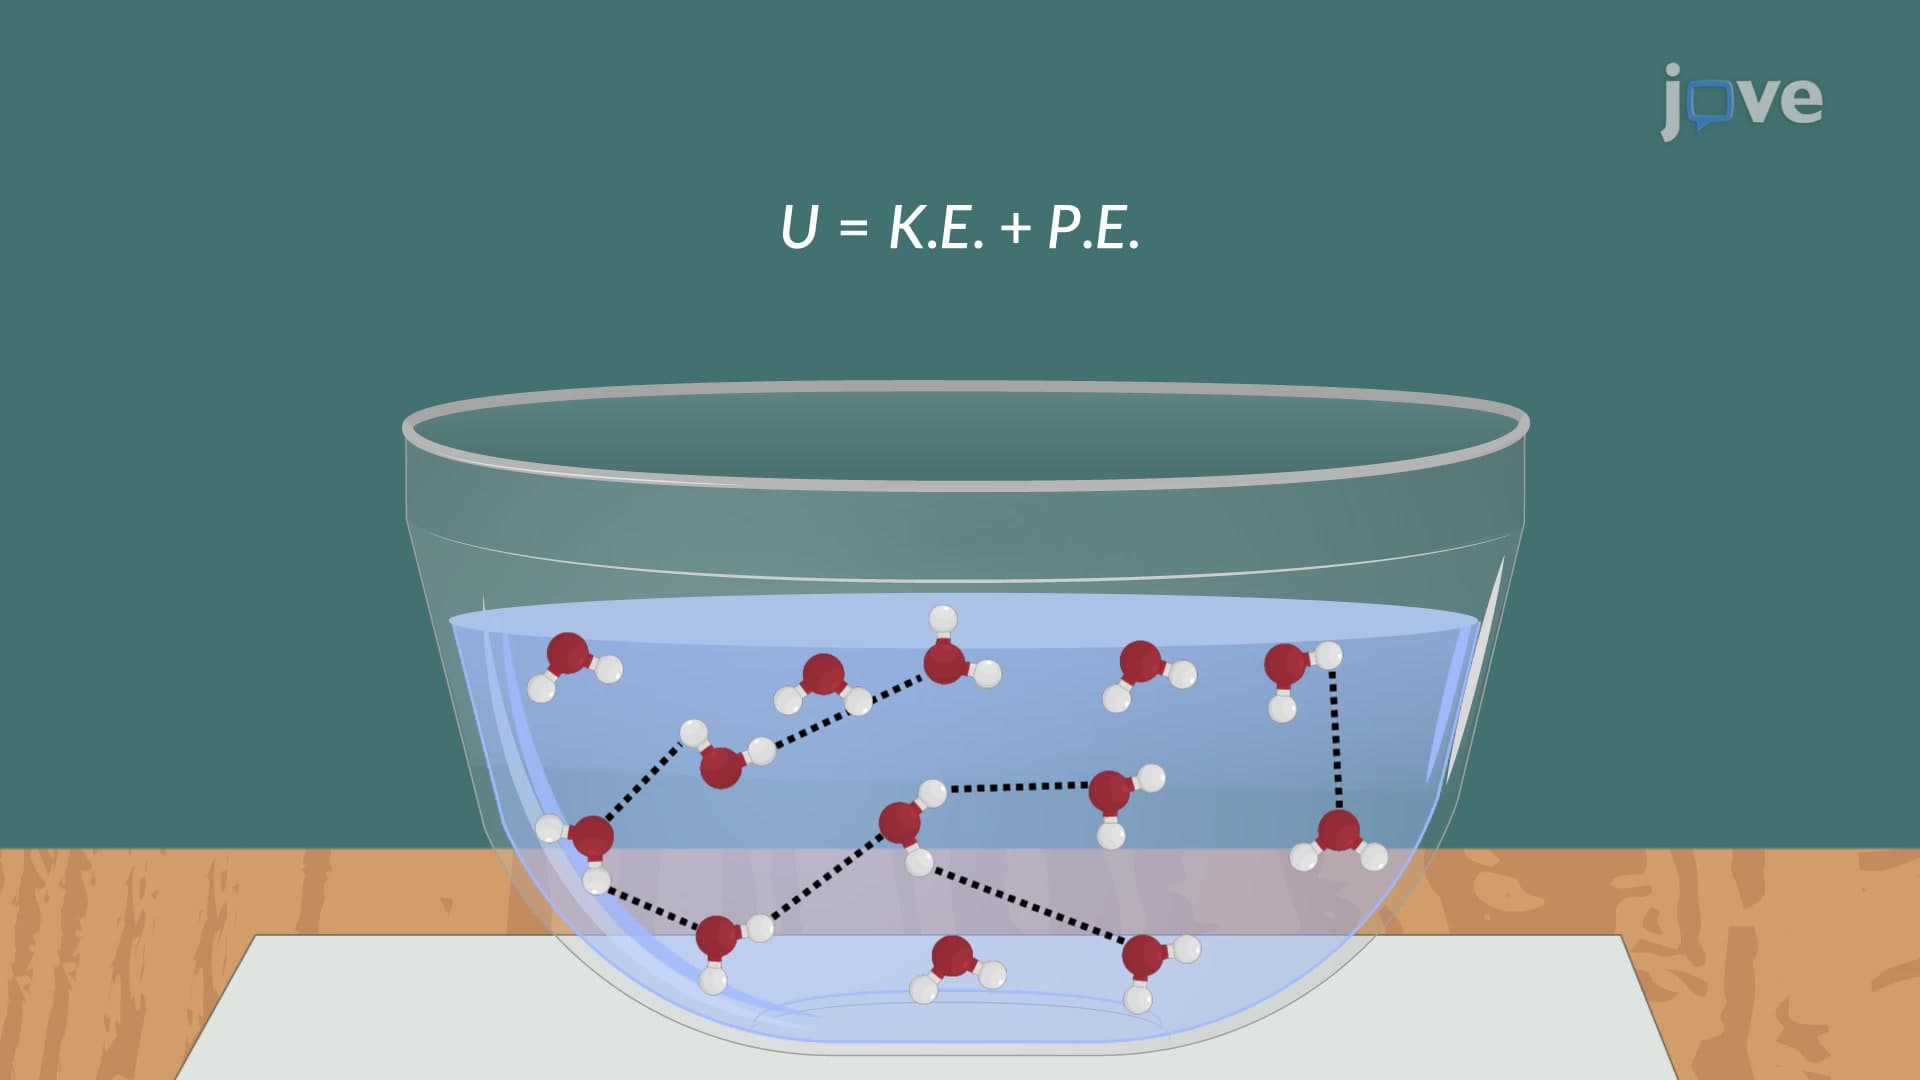
Internal Energy
 01:31
Internal Receptors
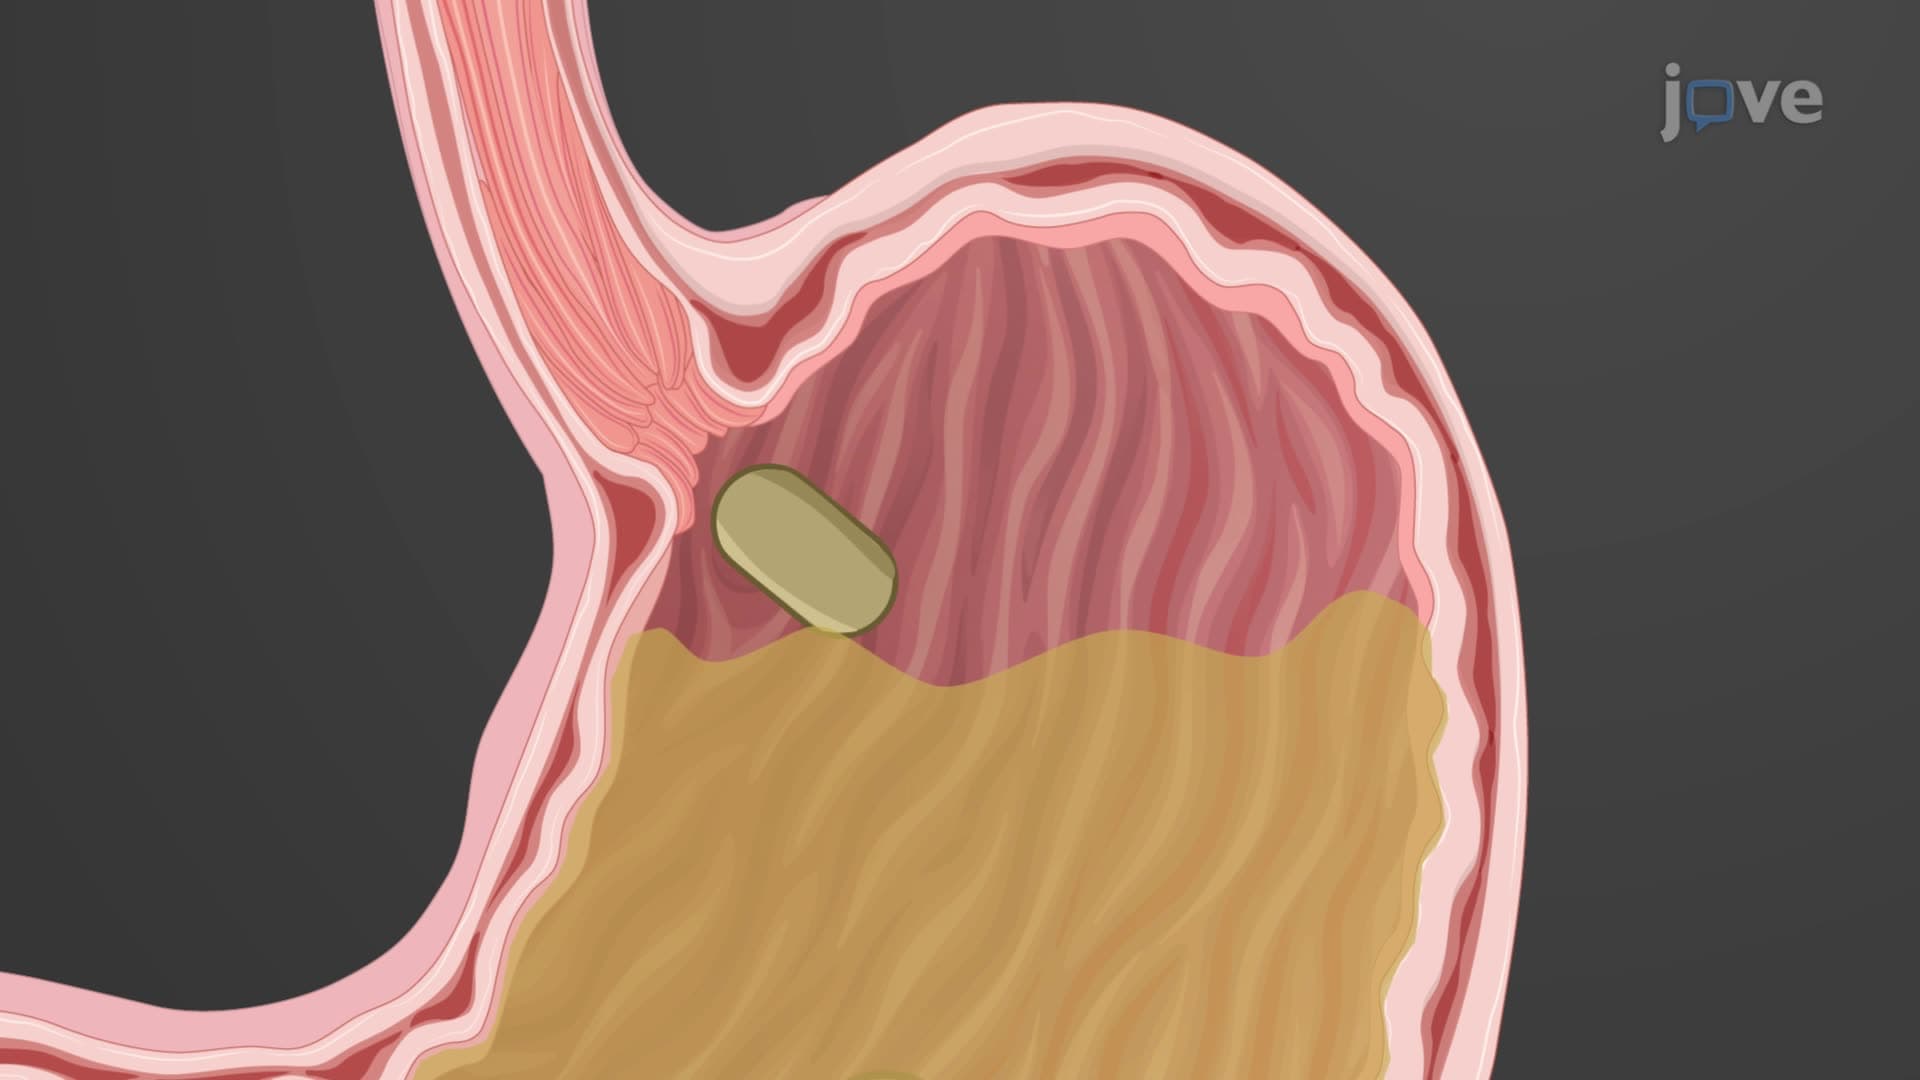 01:16
Gastric Motility
Peristaltic Waves and Chyme Formation
Upon food entry, the stomach initiates...
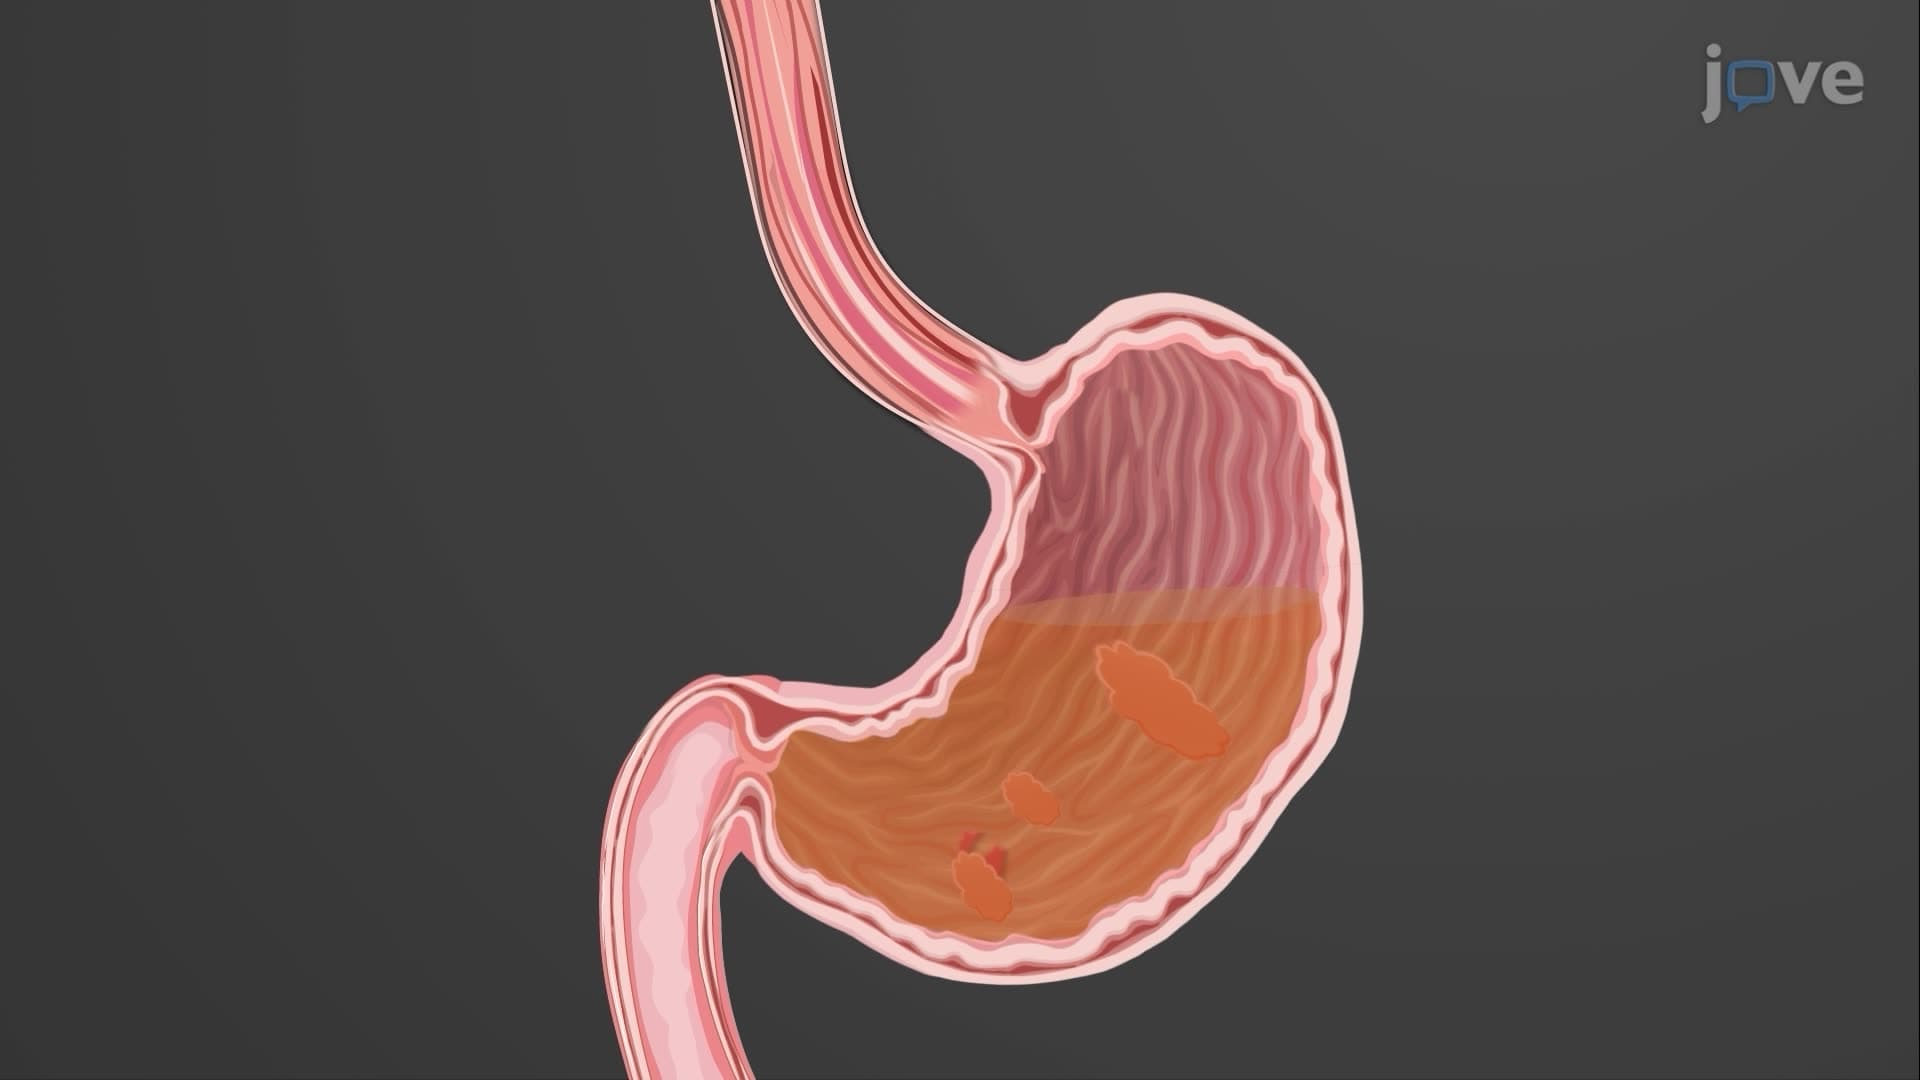 01:16
Gastric Emptying
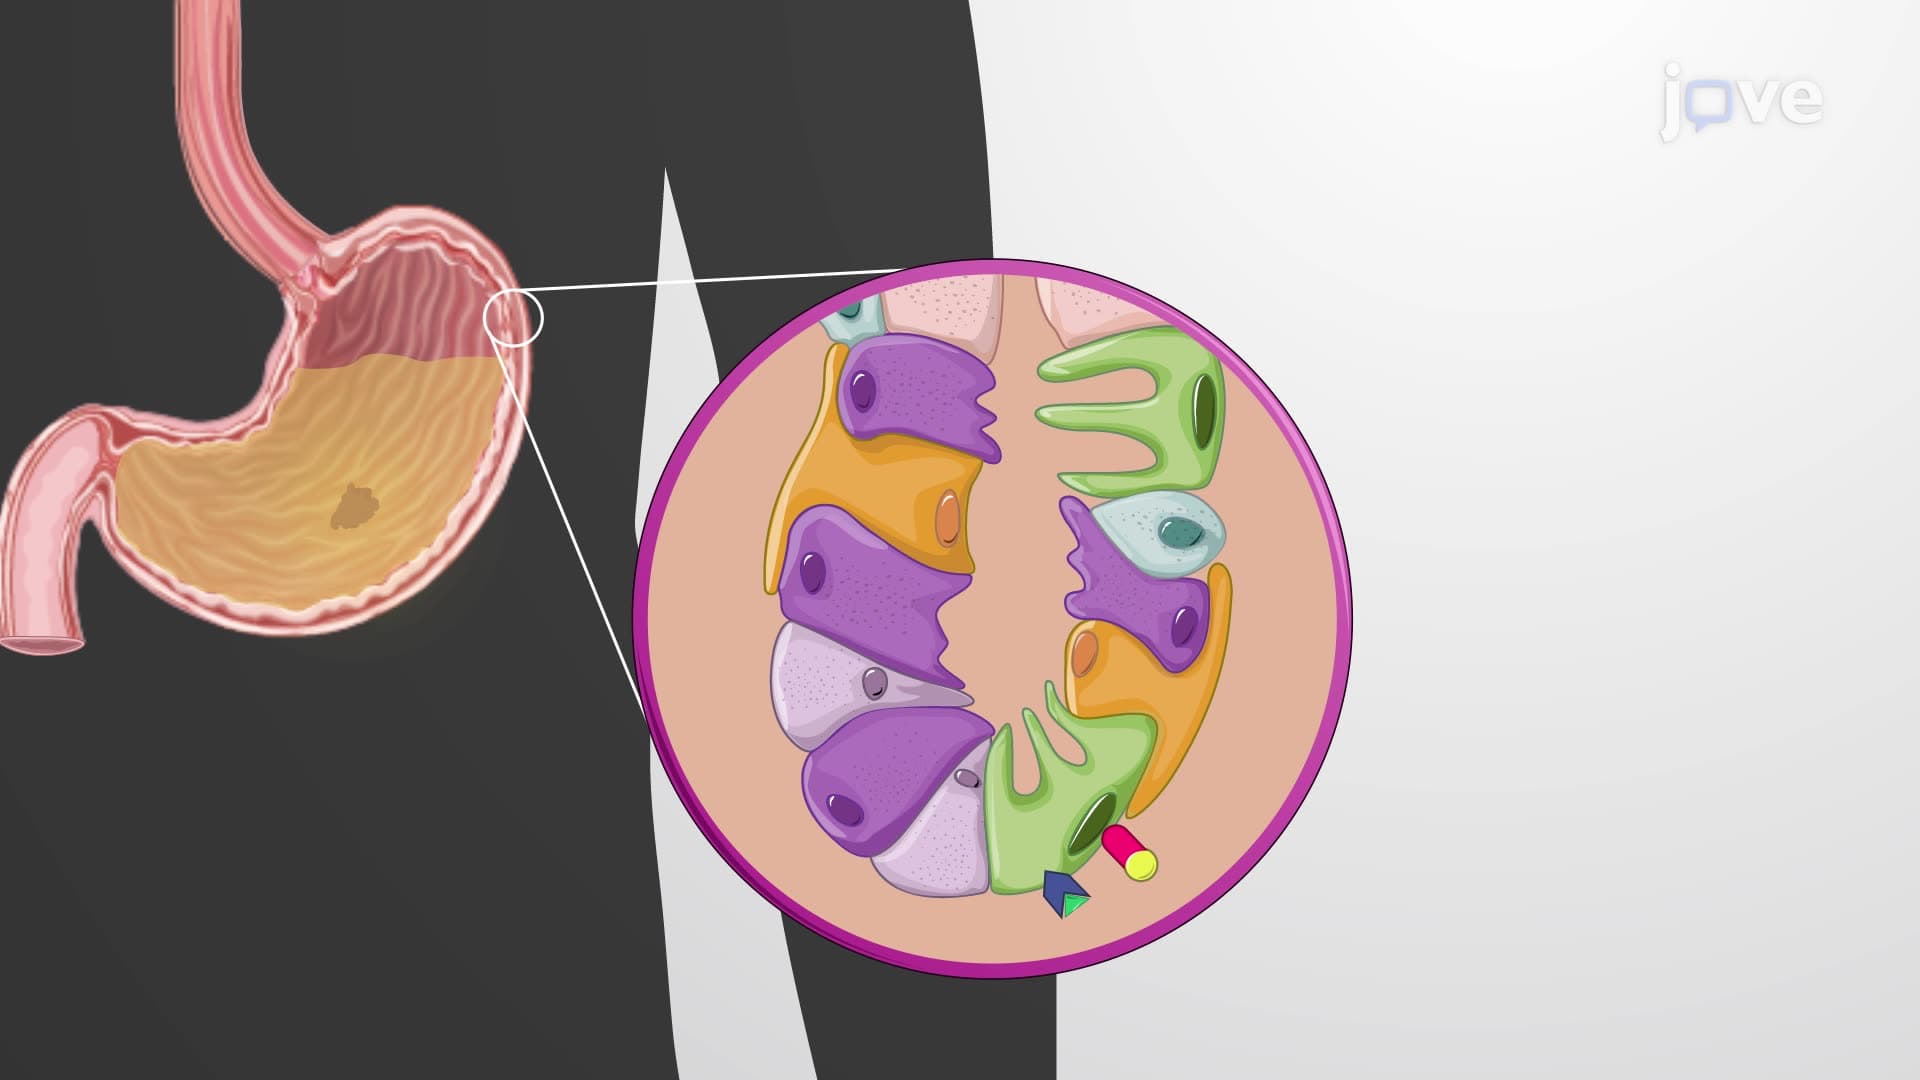 01:26
Gastric Phase of Digestion
When food enters the stomach, it stretches the stomach walls and activates stretch receptors. This triggers local reflexes of the enteric nervous system, mediated through the myenteric plexus. These...