Related Experiment Video
Updated: Jan 29, 2026
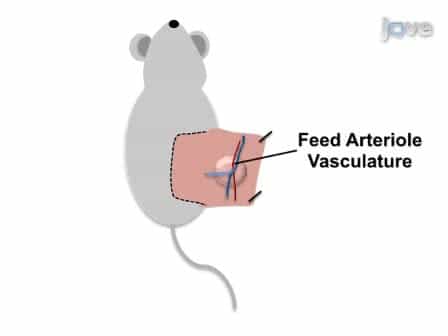

Intravital Microscopy of the Inguinal Lymph Node
Published on: April 4, 2011
Lymph node ratio in inguinal lymphadenectomy for squamous cell vulvar cancer: Results from the AGO-CaRE-1 study
Stephan Polterauer1, Richard Schwameis2, Christoph Grimm2
1Department of Obstetrics and Gynecology, Division General Gynecology and Gynecologic Oncology, Medical University of Vienna, Austria; Karl Landsteiner Institute for General Gynecology and Experimental Gynecologic Oncology, Austria.

Objective:
Lymph node ratio (LNR) can predict treatment outcome and prognosis in patients with solid tumors. Aim of the present analysis was to confirm the concept of using LNR for assessing outcome in patients with vulvar cancer after surgery with inguinal lymphadenectomy in a large multicenter project.
Methods:
The AGO-CaRE-1 study multicenter database was used for analysis. LNR was defined as ratio of number of positive lymph nodes (LN) to the number of resected. Previously established LNR risk groups were used to stratify patients. LNR was investigated with respect to clinical parameters. Univariate and multivariable survival analyses were performed to assess the value of LNR in order to predict overall (OS) and progression-free (PFS) survival.
Results:
In total, 1047 patients treated with surgery including inguinal lymph node resection for squamous cell carcinoma of the vulva were identified from the database. Of these, 370 (35.3%) were found to have positive inguinal LN. In total, 677 (64.7%) had a LNR of 0% (N0), 255 (24.4%) a LNR of >0% < 20%, and 115 (11%) a LNR of ≥20%. Patients with higher LNR were found to have larger tumor size (P < .001), advanced tumor stage (P < .001), high tumor grade (P < .001), and deep stromal invasion (P < .001), more frequently. Three-year PFS rates were 75.7%, 44.2%, and 23.1% and three-year OS rates were 89.7%, 65.4%, and 41.9%, in patients with LNRs 0%, >0% < 20%, and ≥20%, respectively (P < .001, P < .001). On multivariable analyses LNR (HR 7.75, 95%-CI 4.01-14.98, P < .001), FIGO stage (HR 1.41, 95%-CI 1.18-1.69, P < .001), and patient's performance status (HR 1.59, 95%-CI 1.39-1.82, P < .001), were associated with PFS. In addition, LNR (HR 12.74, 95%-CI 5.64-28.78, P < .001), and performance status (HR 1.72, 95%-CI 1.44-2.07, P < .001) were also the only two parameters independently associated with OS. LNR generally showed stronger correlation than number of affected LN when comparing the two different multivariable models.
Conclusions:
In women with vulvar cancer LNR appears to be a consistent, independent prognostic parameter for both PFS and OS and allows patient stratification into three distinct risk groups. In survival analyses, LNR outperformed nodal status and number of positive nodes.
More Related Videos
 09:10
Generation of Lymph Node-fat Pad Chimeras for the Study of Lymph Node Stromal Cell Origin
Published on: December 16, 2013
 12:53
Collection and Processing of Lymph Nodes from Large Animals for RNA Analysis: Preparing for Lymph Node Transcriptomic Studies of Large Animal Species
Published on: May 19, 2018
Related Concept Videos
 01:23
Detailed Structure and Function of Lymph Nodes
From a histological perspective, lymph nodes can be split into two main areas: the superficial cortex and the deep medulla. The outer cortex is populated by dendritic cells, macrophages, and B lymphocytes, which are densely packed into follicles. When these B-lymphocytes are presented...
 01:26
Varicose Veins II: Diagnostic Studies and Interprofessional Care
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care
 01:23
Poisson's Ratio
 01:09
Odds Ratio
 01:12
Hazard Ratio
For example, in a clinical trial...