Related Experiment Video
Updated: Jan 29, 2026

Integration of Brain Tissue Saturation Monitoring in Cardiopulmonary Exercise Testing in Patients with Heart Failure
Published on: October 1, 2019
The Added Value of Exercise Stress Echocardiography in Patients With Heart Failure
Iacopo Fabiani1, Nicola Riccardo Pugliese1, Gian Giacomo Galeotti2
1Cardiac, Thoracic and Vascular Department, University of Pisa, Pisa, Italy; Department of Surgical, Medical and Molecular Pathology and Critical Care Medicine, Italy.

Abstract:
Doppler echocardiography can provide reliable and repeatable measures of cardiac index (CI), whereas lung ultrasound (LUS) represents a quantitative approach to assess pulmonary congestion. We tested the hypothesis that simultaneous assessment of CI and LUS during exercise stress echocardiography (ESE) may define heart failure (HF) outpatients with different risk of adverse outcome. Standard transthoracic echocardiography and LUS (B-lines) evaluation were assessed during semisupine ESE. CI and B-lines were measured at baseline and peak exercise. Resting plasma B-type natriuretic peptide levels were also evaluated. We enrolled 105 HF patients (87 males; age 62 ± 11 years; New York Heart Association class I to III) with reduced left ventricular ejection fraction (30 ± 7%). Patients were classified into 4 profiles: (1) peak CI ≥4.0 l/min/m2 and peak B-lines <15 (no evidence of congestion or hypoperfusion, n = 47); (2) peak CI ≥4.0 l/min/m2 and peak B-lines ≥15 (congestion with adequate perfusion, n = 23); (3) peak CI <4.0 l/min/m2 and peak B-lines <15 (hypoperfusion without congestion, n = 13); and (4) peak CI <4.0 l/min/m2 and peak B-lines ≥15 (congestion and hypoperfusion, n = 22). There were 21 cardiovascular deaths and 18 hospitalizations for worsening HF during a median follow-up of 29 months. Multivariate predictors of the combined end point were peak hemodynamic profiles (hazard ratio [HR] 1.62, 95% confidence interval [CI] 1.19 to 2.21; p = 0.002), B-type natriuretic peptide (HR 1.00, 95% CI 1.00 to 1.01; p = 0.001), and rest E/e' (HR 1.09, 95% CI 1.03 to 1.15; p = 0.002). Survival analysis showed a worse survival in patients with ESE-derived D profile, followed by patients with C, B, and A profile (log-rank: chi-square = 40.5; p <0.0001). In conclusion, dual evaluation of CI and LUS during ESE is useful for risk stratification of HF patients with reduced ejection fraction. Evidence of pulmonary congestion and low CI at peak ESE identifies a subgroup with a very high risk of adverse outcome.
More Related Videos
 07:49
Author Spotlight: Investigating HR-Dependent Cardiac Function in Mouse Models Through a Novel Atrial-Pacing Approach
Published on: July 21, 2023
 10:21
Evaluation of Hydration Status by Bioelectrical Impedance Vector Analysis in Patients with Ischemic Heart Disease Undergoing Exercise Stress Test
Published on: September 22, 2023
Related Concept Videos
 01:26
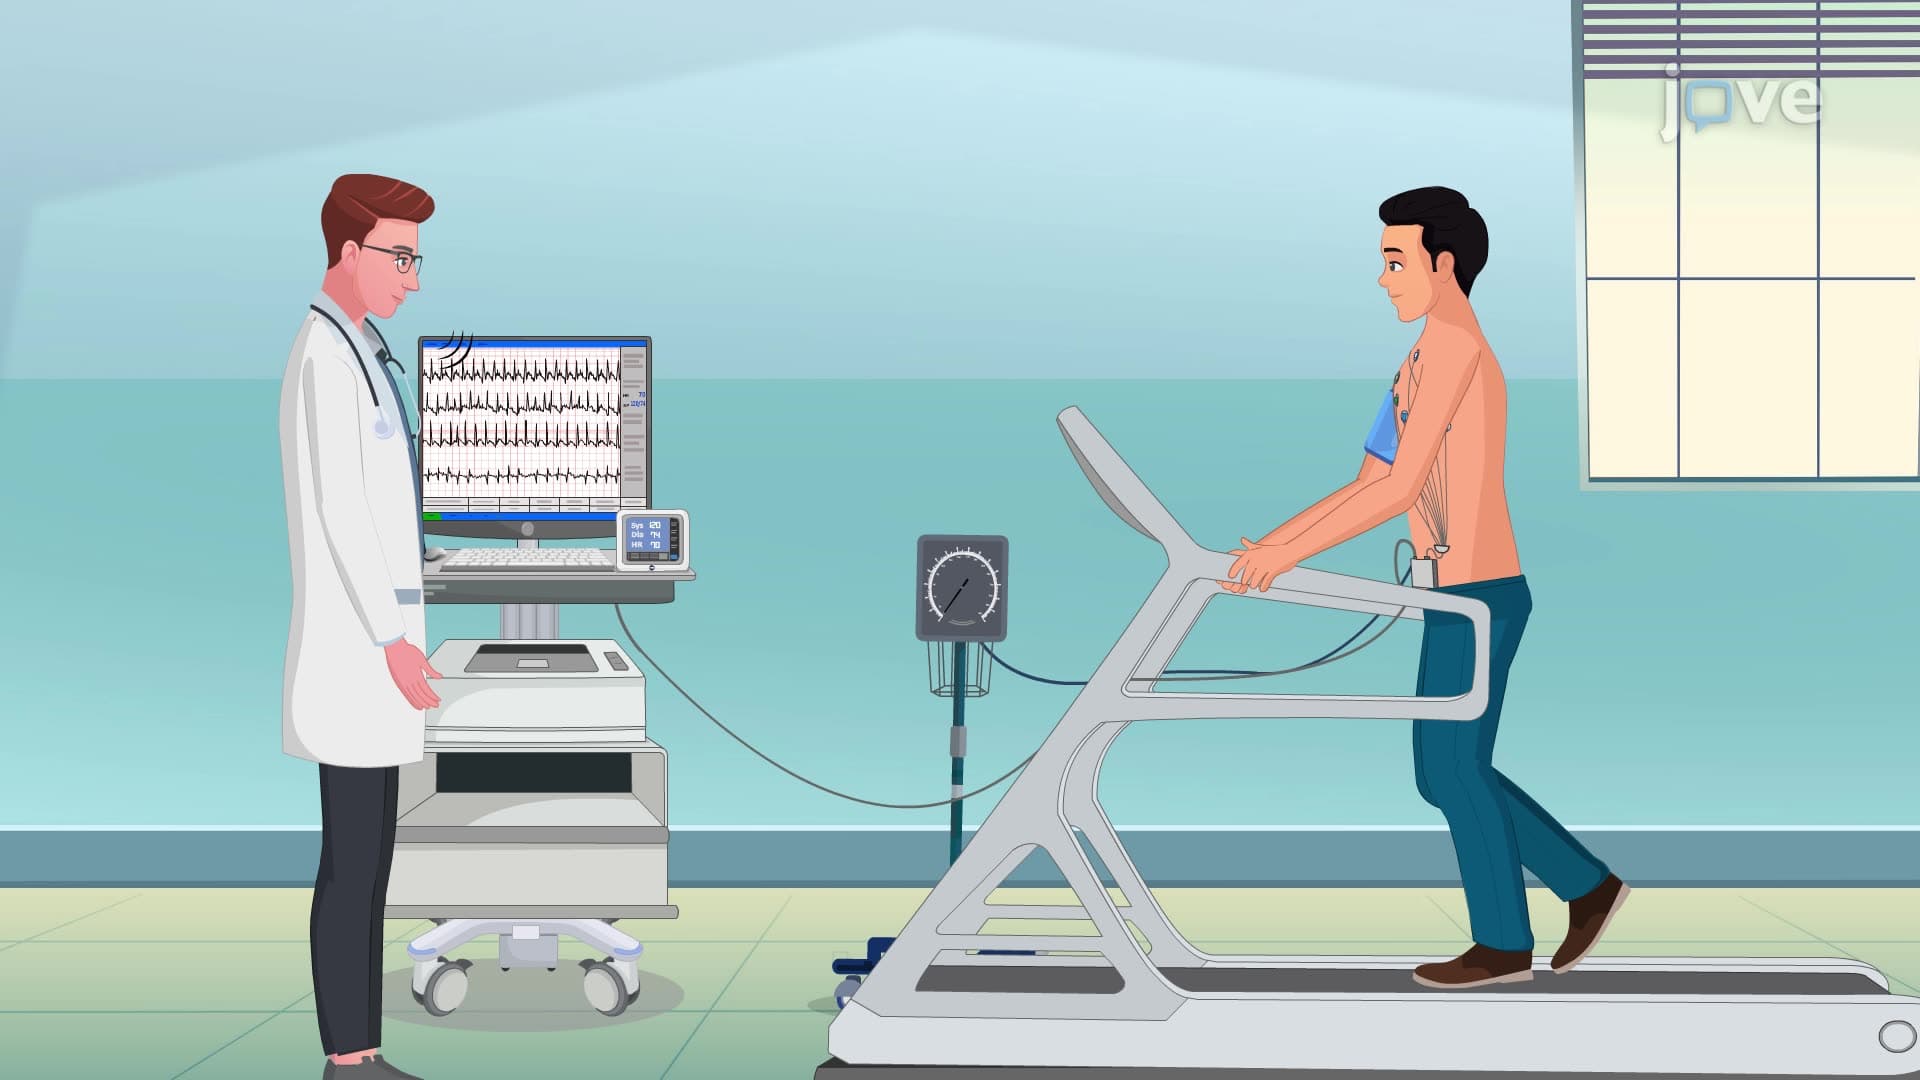
Exercise Stress Test
Exercise stress testing, commonly known as a treadmill test, is a noninvasive procedure used to evaluate cardiovascular function and diagnose heart conditions.
Definition
An exercise stress test measures the heart's response to exertion using a treadmill or stationary bicycle. Chest electrodes record the heart's electrical activity through an ECG, and blood pressure is monitored regularly.
Purposes
 01:29
Heart Failure II: Pathophysiology
 01:17
Pathophysiology of Heart Failure
 01:27
Heart Failure I: Introduction
 01:22
Heart Failure VI: Adjunct Therapies
 01:22
Heart Failure Drugs: Diuretics