Related Experiment Video
Updated: Jan 28, 2026


Irradiator Commissioning and Dosimetry for Assessment of LQ α and β Parameters, Radiation Dosing Schema, and in vivo Dose Deposition
Published on: March 11, 2021
Radiobiological optimization comparison between pulse-dose-rate and high-dose-rate brachytherapy in patients with
Pierre Annede1, Isabelle Dumas1, Antoine Schernberg2
1Radiotherapy Department, Brachytherapy Unit, Gustave Roussy Cancer Campus, Villejuif, France.

Purpose:
Only scarce data are available on the possibility to include radiobiological optimization as part of the dosimetric process in cervical cancer treated with brachytherapy (BT). We compared dosimetric outcomes of pulse-dose-rate (PDR) and high-dose-rate (HDR)-BT, according to linear-quadratic model.
Methods And Materials:
Three-dimensional dosimetric data of 10 consecutive patients with cervical cancer undergoing intracavitary image-guided adaptive PDR-BT after external beam radiation therapy were examined. A new HDR plan was generated for each patient using the same method as for the PDR plan. The procedure was intended to achieve the same D90 high-risk clinical target volume with HDR as with PDR planning after conversion into dose equivalent per 2 Gy fractions (EQD2) following linear-quadratic model. Plans were compared for dosimetric variables.
Results:
As per study's methodology, the D90 high-risk clinical target volume was strictly identical between PDR and HDR plans: 91.0 Gy (interquartile: 86.0-94.6 Gy). The median D98 intermediate-risk clinical target volume was 62.9 GyEQD2 with HDR vs. 65.0 GyEQD2 with PDR (p < 0.001). The median bladder D2cc was 65.6 GyEQD2 with HDR, vs. 62 GyEQD2 with PDR (p = 0.004). Doses to the rectum, sigmoid, and small bowel were higher with HDR plans with a median D2cc of 55.6 GyEQD2 (vs. 55.1 GyEQD2, p = 0.027), 67.2 GyEQD2 (vs. S 64.7 GyEQD2, p = 0.002), and 69.4 GyEQD2 (vs. 66.8 GyEQD2, p = 0.014), respectively. For organs at risk (OARs), the effect of radiobiological weighting depended on the dose delivered. When OARs BT contribution to D2cc doses was <20 GyEQD2, both BT modalities were equivalent. OARs EQD2 doses were all higher with HDR when BT contribution to D2cc was ≥20 GyEQD2.
Conclusion:
Both BT modalities provided satisfactory target volume coverage with a slightly higher value with the HDR technique for OARs D2cc while intermediate-risk clinical target volume received higher dose in the PDR plan. The radiobiological benefit of PDR over HDR was predominant when BT contribution dose to OARs was >20 Gy.

Related Concept Videos
 01:25
Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant
 01:17
Increased pulse rate
Many factors can elevate the risk of developing tachycardia. These include advanced age, a family history of arrhythmias, and an...
 01:14
Decreased pulse rate
There are specific risk factors that can elevate the likelihood of developing bradycardia. Advanced age is a significant factor, with...
 01:15
Drug Dosing: Geriatric Patients
 01:21
Drug Dosing: Obese Patients
 02:53
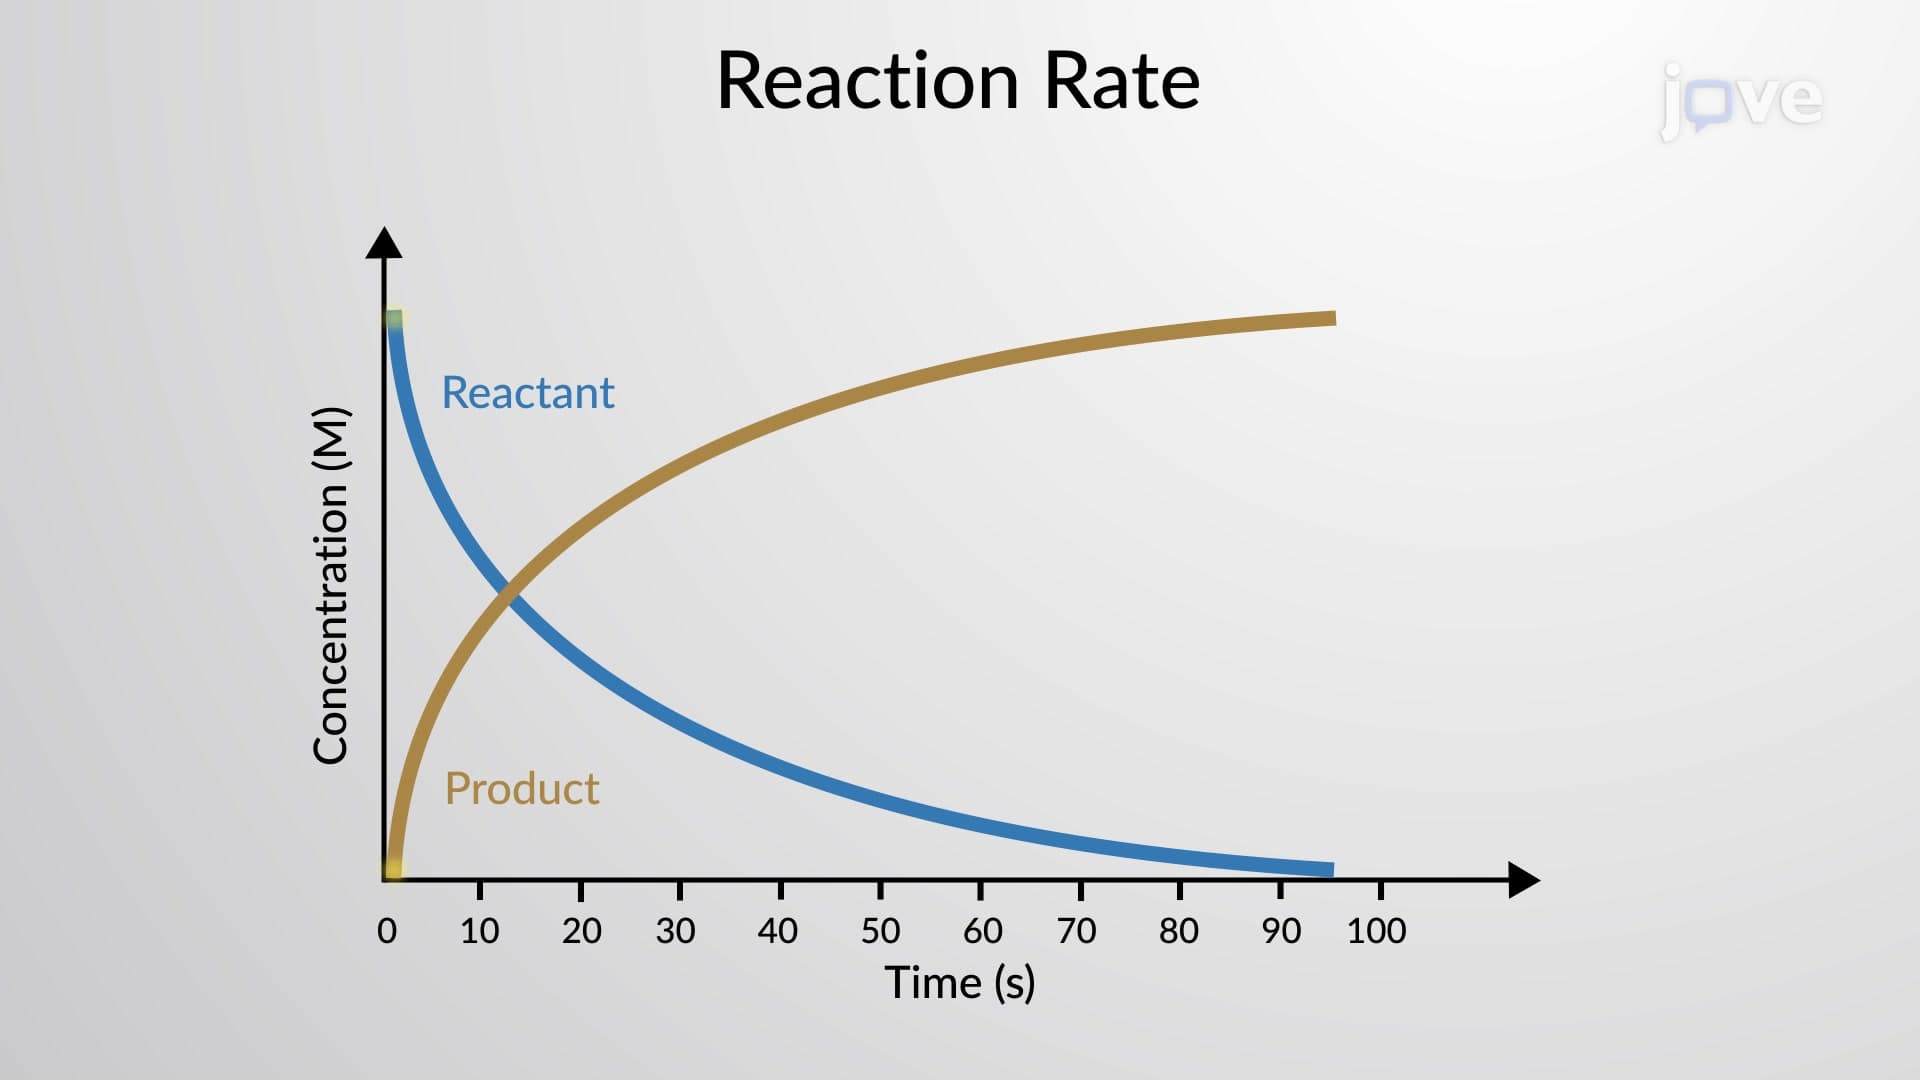
Reaction Rate
The mathematical representation of the change in the concentration of reactants and products, over time, is the rate...