Related Experiment Video
Updated: Jan 28, 2026


Bronchial Thermoplasty: A Novel Therapeutic Approach to Severe Asthma
Published on: November 4, 2010
Quantitative CT assessment of bronchial and vascular alterations in severe precapillary pulmonary hypertension
Florence Coste1,2, Ilyes Benlala1,2, Gaël Dournes1,2,3
1Université de Bordeaux, Centre de Recherche Cardio-Thoracique de Bordeaux, U1045, F-33000 Bordeaux, France, florence-coste@hotmail.fr.

Background:
Little is known about in vivo alterations at bronchial and vascular levels in severe pulmonary hypertension (PH) of different etiologies. We aimed to compare quantitative computed tomography (CT) data from the following three groups of severe precapillary PH patients: COPD, idiopathic pulmonary arterial hypertension (iPAH), and chronic thromboembolic PH (CTEPH).
Patients And Methods:
This study was approved by the institutional review board. Severe PH patients (mean pulmonary arterial pressure [mPAP] ≥35 mmHg) with COPD, iPAH, or CTEPH (n=24, 16, or 16, respectively) were included retrospectively between January 2008 and January 2017. Univariate analysis of mPAP was performed in each severe PH group. Bronchial wall thickness (WT) and percentage of cross sectional area of pulmonary vessels less than 5 mm2 normalized by lung area (%CSA<5) were measured and compared using CT, and then combined to arterial partial pressure of oxygen (PaO2) to generate a "paw score" compared within the three groups using Kruskal-Wallis and its sensitivity using Fisher's exact test.
Results:
WT was higher and %CSA<5 was lower in the COPD group compared to iPAH and CTEPH groups. Mosaic pattern was higher in CTEPH group than in others. In severe PH patients secondary to COPD, mPAP was positively correlated to %CSA<5. By contrast, in severe iPAH, this correlation was negative, or not correlated in severe CTEPH groups. In the COPD group, "paw score" showed higher sensitivity than in the other two groups.
Conclusion:
Unlike in severe iPAH and CTEPH, severe PH with COPD can be predicted by "paw score" reflecting bronchial and vascular morphological differential alterations.

Related Concept Videos
 01:30
Pulmonary Hypertension: Classification and Pathogenesis
There are various classifications for PH, each relating to different underlying causes and also...
 01:28
Treatment for Pulmonary Arterial Hypertension: Phosphodiesterase Inhibitors
Among the PDE5 inhibitors, sildenafil (Revatio) stands out as a competitive and selective inhibitor. It operates by elevating cellular levels of cGMP and augmenting signaling through the cGMP-PKG pathway, promoting vasodilation. Upon oral...
 01:18
Treatment for Pulmonary Arterial Hypertension: Endothelin Receptor Antagonists
ETs are synthesized through a complex sequence of enzymatic steps, primarily involving an enzyme referred to as endothelin-converting enzyme...
 01:23
Treatment for Pulmonary Arterial Hypertension: Prostacyclin Receptor Agonists
These agonists bind to the IPR receptor situated on the plasma membrane of the pulmonary artery smooth muscle cells. This binding triggers a cascade of reactions known as the GS-AC-cAMP-PKA pathway. This pathway results in the relaxation of smooth muscle...
 01:16
Treatment for Pulmonary Arterial Hypertension: Oxygen Therapy for Respiratory Failure
Oxygen therapy is vital in increasing and maintaining blood oxygen levels in PAH patients. As a result, it aids in reducing fatigue,...
 01:23
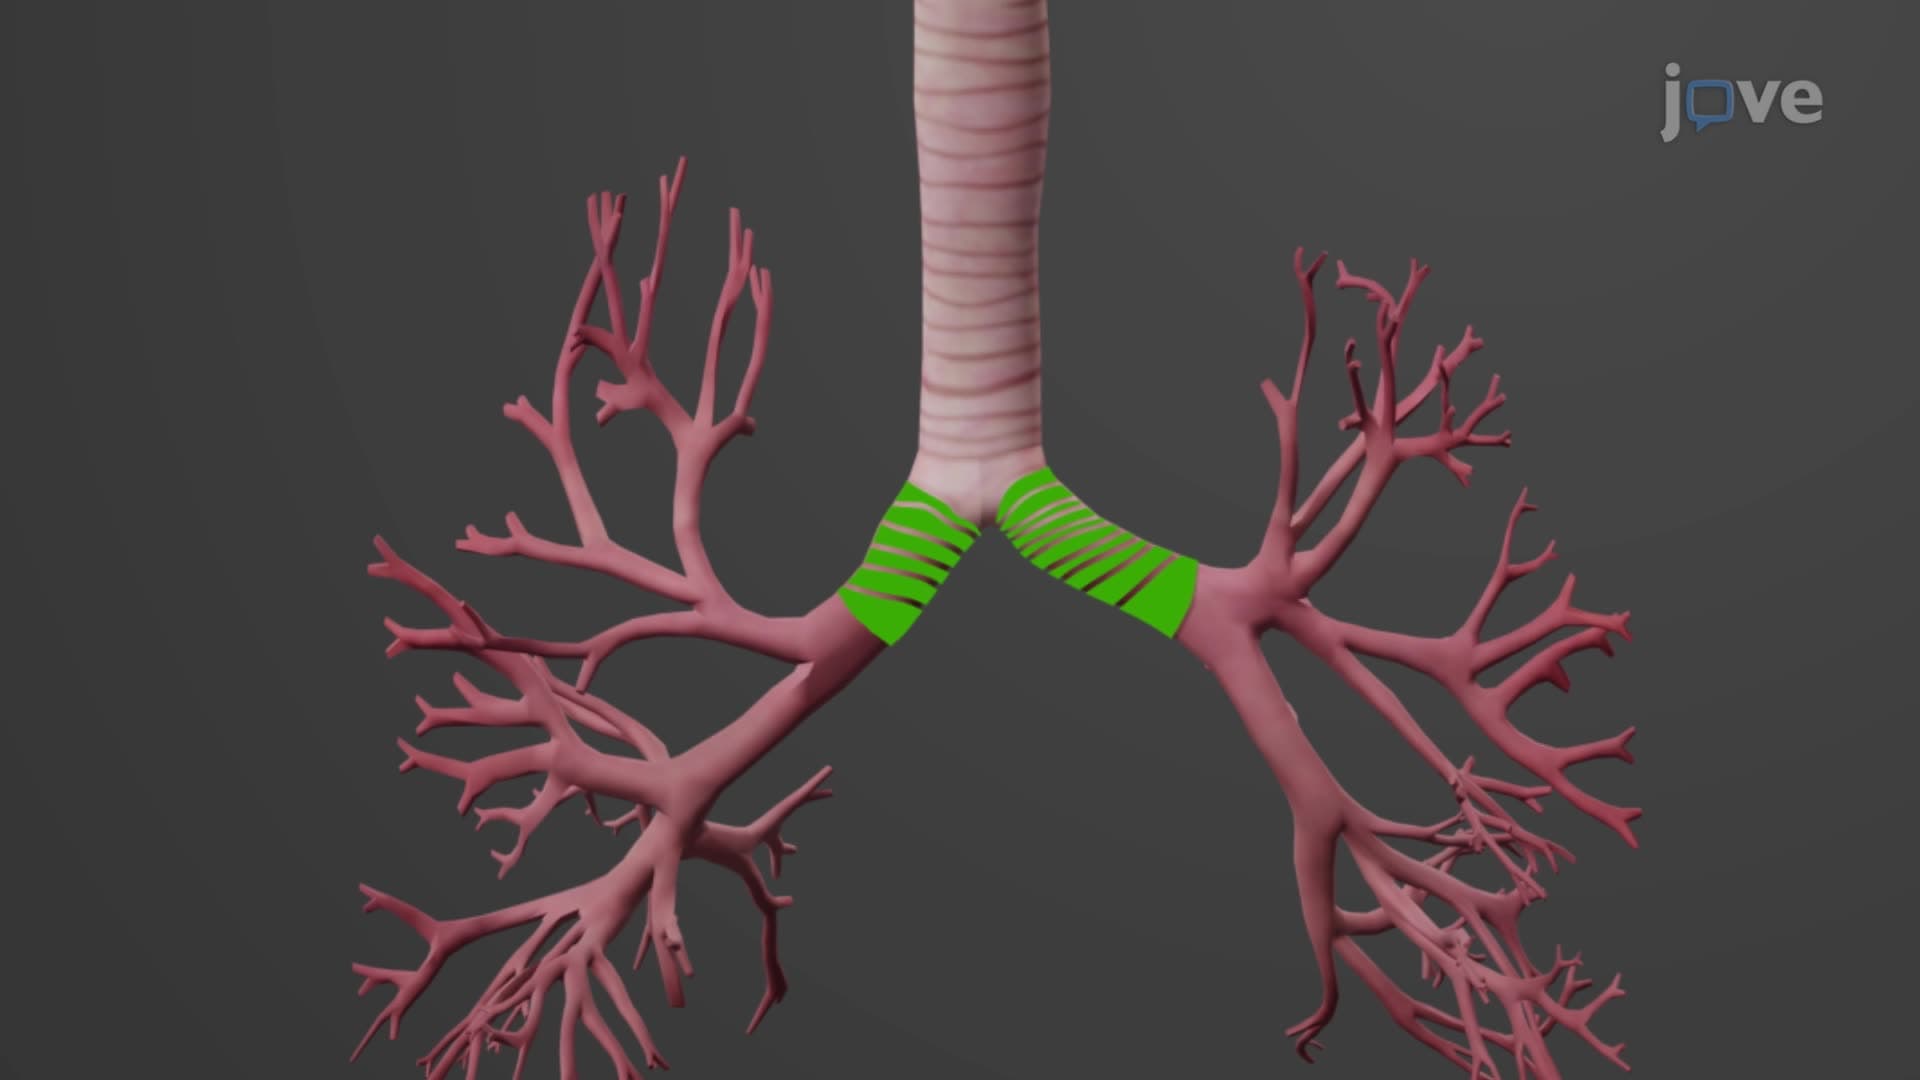
The Bronchial Tree
The trachea, commonly known as the windpipe, is a tube that connects the larynx (voice box) to the bronchi. At a point called the carina, it bifurcates into two primary bronchi. The right primary bronchus is wider, shorter, and more vertical than the left primary...