Related Experiment Video
Updated: Jan 28, 2026

Viral Transgene Expression in Rodent Hearts and the Assessment of Cardiac Arrhythmia Risk
Published on: July 27, 2022
Cardiac sympathectomy for refractory ventricular arrhythmias in cardiac sarcoidosis
David R Okada1, Fabrizio R Assis1, Nisha A Gilotra1
1Division of Cardiology, Department of Medicine, Johns Hopkins University School of Medicine, Baltimore, Maryland.

Insights
Cardiac sympathetic denervation (CSD) offers a promising treatment for refractory ventricular arrhythmias (VAs) in cardiac sarcoidosis (CS). This procedure significantly reduced implantable cardioverter-defibrillator shocks in patients unresponsive to standard therapies.
Area of Science:
- Cardiology
- Electrophysiology
- Cardiac Surgery
Background:
- Ventricular arrhythmias (VAs) in cardiac sarcoidosis (CS) are often resistant to antiarrhythmic drugs (AAD) and catheter ablation (CA).
- Cardiac sympathetic denervation (CSD) has demonstrated efficacy in reducing VA burden and implantable cardioverter-defibrillator (ICD) shocks in nonischemic cardiomyopathy.
Purpose of the Study:
- To evaluate the preliminary experience of cardiac sympathetic denervation (CSD) in patients diagnosed with cardiac sarcoidosis (CS) and experiencing refractory ventricular arrhythmias (VAs).
Main Methods:
- Retrospective analysis of five patients with CS and refractory VAs who underwent CSD.
- Data collected included patient demographics, procedural details, and pre- and post-CSD arrhythmic events, specifically ICD shocks.
Main Results:
- Five patients (mean age 53 years, LVEF 38%) underwent CSD. Median ICD shocks decreased from 5 in the 6 months pre-CSD to 0 during a median 26-month follow-up.
- One patient experienced sustained VA requiring repeat CA, another had premature ventricular contractions managed with repeat CA, and one progressed to heart failure necessitating transplantation.
Conclusions:
- Cardiac sympathetic denervation (CSD) appears to be a feasible adjunctive therapy for managing ventricular arrhythmias (VAs) in cardiac sarcoidosis (CS) patients refractory to AAD therapy and CA.
Background:
Ventricular arrhythmias (VAs) in cardiac sarcoidosis (CS) are frequently refractory to both antiarrhythmic drug (AAD) therapy and catheter ablation (CA). Cardiac sympathetic denervation (CSD) has been shown to reduce VA burden and implantable cardioverter-defibrillator (ICD) shocks in patients with nonischemic cardiomyopathy.
Objective:
We aimed to report our center's preliminary experience with CSD in patients with known or presumed CS and refractory VAs.
Methods:
Patients with CS and refractory VAs who underwent CSD at our institution were included. Patient characteristics, procedural outcomes, and number of arrhythmic events including ICD shocks pre- and post-CSD are reported.
Results:
Five patients with CS (mean age 53 ± 11 years; 2 men [40%]; mean left ventricular ejection fraction 38% ± 11%) underwent CSD for VA refractory to AAD therapy and CA. Four of 5 patients underwent bilateral CSD; 1 patient underwent right-sided sympathectomy only because of poor intraoperative visualization on the left. Procedural complications included hemothorax in 1 patient and azygous vein injury in 1 patient. The median number of ICD shocks in the 6 months pre-CSD was 5. During a median follow-up of 26 months (range 5-29 months), the median number of ICD shocks post-CSD was 0; 1 patient had sustained VA that was below the threshold for device therapy, and 1 patient had symptomatic premature ventricular contractions; both underwent repeat CA. In addition, 1 patient required cardiac transplantation for progressive heart failure.
Conclusion:
CSD may be a feasible therapeutic adjunct for patients with CS and VA refractory to AAD therapy and CA.
More Related Videos
 10:39
Rat Model of Right-Sided Cardiac Remodeling and Arrhythmia Using Pulmonary Artery Banding
Published on: August 30, 2024
 08:28
Methods for ECG Evaluation of Indicators of Cardiac Risk, and Susceptibility to Aconitine-induced Arrhythmias in Rats Following Status Epilepticus
Published on: April 5, 2011
Related Concept Videos
 01:28
Mechanism of Cardiac Arrhythmias
 01:25
ECG Interpretation of Arrhythmias II: Atrial, Junctional and Ventricular Arrhythmias
 01:22
Cardiac Output II: Effect of Stroke Volume on Cardiac Output
Preload
Preload refers to the initial elongation of the cardiac myocytes before contraction and is related to the volume of blood filling the heart at the end of diastole, or end-diastolic volume. The...
 01:19
Cardiac Output I:Effect of Heart Rate on Cardiac Output
Cardiac output (CO) refers to the total amount of blood ejected by one of the ventricles in liters per minute (L/min). In a resting adult, CO ranges from 5 to 6 L/min, adjusting according to the body's metabolic requirements.
Effect of Heart Rate on Cardiac Output
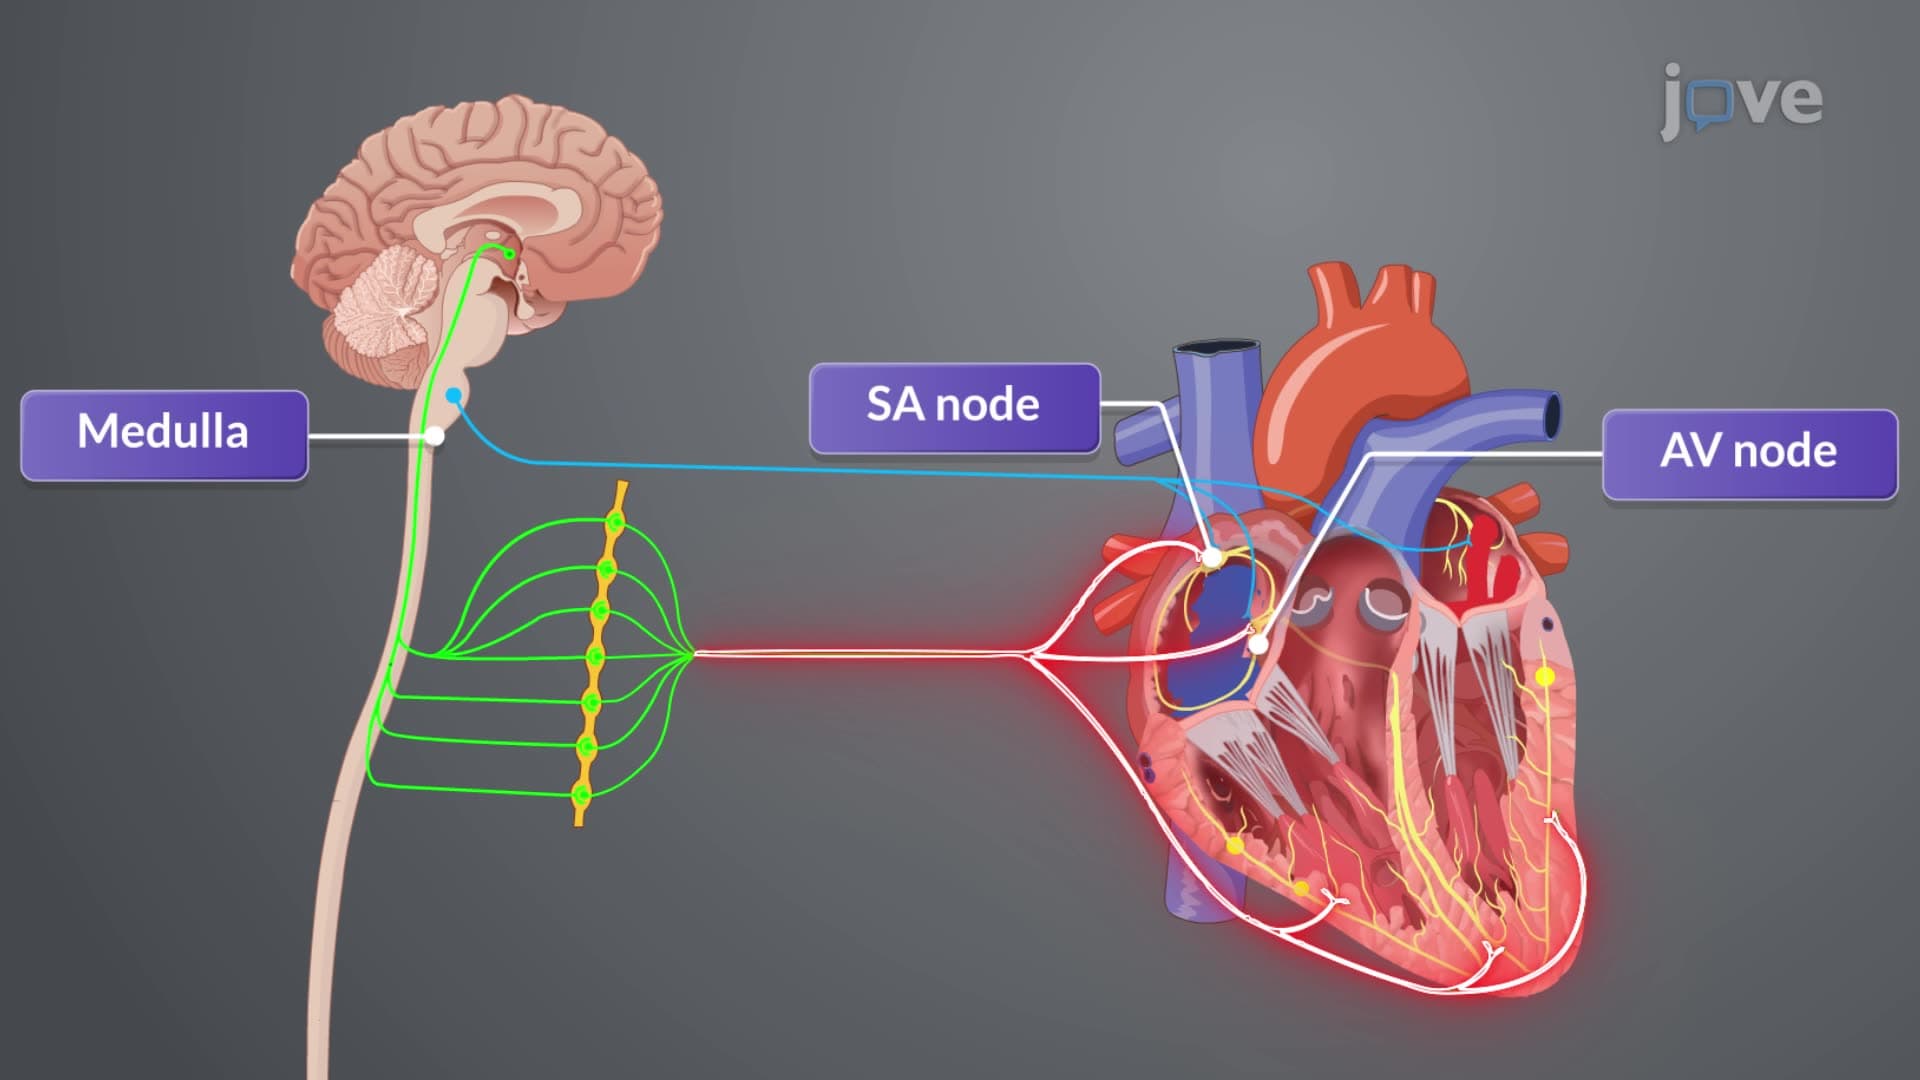
Cardiac output adapts to metabolic demands during stress, physical activity, or illness. The autonomic nervous system regulates heart rate via the sinoatrial node. The parasympathetic nervous system decreases heart...
 01:13
The Cardiac Cycle
The Process
Electrical signals—sent from the sinoatrial (SA) node in the right atrial wall to the atrioventricular (AV) node between the right atrium and right ventricle—cause both atria to simultaneously contract. When the signal reaches the AV node, it pauses for approximately a tenth of a second, allowing the atria to contract and...
 01:29
Cardiac Cycle
During the cardiac cycle, blood flow through the heart is regulated entirely by changing pressure gradients. This sequence of events begins with the heart in a state of total relaxation, known as mid-to-late diastole, during which blood passively flows from...