A novel methodological framework for multimodality, trajectory model-based prognostication
Related Experiment Video
Updated: Jan 28, 2026

Constructing and Visualizing Models using Mime-based Machine-learning Framework
Published on: July 22, 2025
Jonathan Elmer1, Bobby L Jones2, Vladimir I Zadorozhny3
1Department of Emergency Medicine, University of Pittsburgh School of Medicine, Pittsburgh, PA, USA; Department of Critical Care Medicine, University of Pittsburgh School of Medicine, Pittsburgh, PA, USA; Department of Neurology, University of Pittsburgh School of Medicine, Pittsburgh, PA, USA.

Introduction:
Prognostic tools typically combine several time-invariant clinical predictors using regression models that yield a single, time-invariant outcome prediction. This results in considerable information loss as repeatedly or continuously sampled data are aggregated into single summary measures. We describe a method for real-time multivariate outcome prediction that accommodates both longitudinal data and time-invariant clinical characteristics.
Methods:
We included comatose patients treated after resuscitation from cardiac arrest who underwent ≥6 h of electroencephalographic (EEG) monitoring. We used Persyst v13 (Persyst Development Corp, Prescott AZ) to generate quantitative EEG (qEEG) features and calculated hourly summaries of whole brain suppression ratio and amplitude-integrated EEG. We randomly selected half of subjects as a training sample and used the other half as a test sample. We applied group-based trajectory modeling (GBTM) to the training sample to group patients based on qEEG evolution, then estimated the relationship of group membership and clinical covariates with awakening from coma and surviving to hospital discharge using logistic regression. We used these parameters to calculate posterior probabilities of group membership (PPGMs) in the test sample, and built three prognostic models: adjusted logistic regression (no GBTM), unadjusted GBTM (no clinical covariates) and adjusted GBTM (all data). We compared these models performance characteristics.
Results:
We included 723 patients. Group-specific outcome estimates from a 7-group GBTM ranged from 0 to 75%. Compared to unadjusted GBTM, adjusted GBTM calibration was significantly improved at 6 and 12 h, and time to an outcome estimate <10% and <5% were significantly shortened. Compared to simple logistic regression, adjusted GBTM identified a substantially larger proportion of subjects with outcome probability <1%.
Conclusions:
We describe a novel methodology for combining GBTM output and clinical covariates to estimate patient-specific prognosis over time. Refinement of such methods should form the basis for new avenues of prognostication research that minimize loss of clinically important information.


Related Concept Videos
 01:16
Response Surface Methodology
The process of RSM involves several key steps:
 01:15
Systematic Error: Methodological and Sampling Errors
Sampling errors originate from improper sampling methods or the wrong sample population. These errors can be minimized by refining the sampling strategy. Defective instruments or faulty calibrations are the sources of instrumental...
 02:33
Lewis Acids and Bases
A coordinate covalent bond (or dative bond) occurs when one of the atoms in the bond provides both bonding electrons. For example, a coordinate covalent bond occurs when a water molecule combines with a hydrogen ion to form a hydronium ion. A coordinate covalent bond also results when...
 01:54
Base Excision Repair
The first step of...
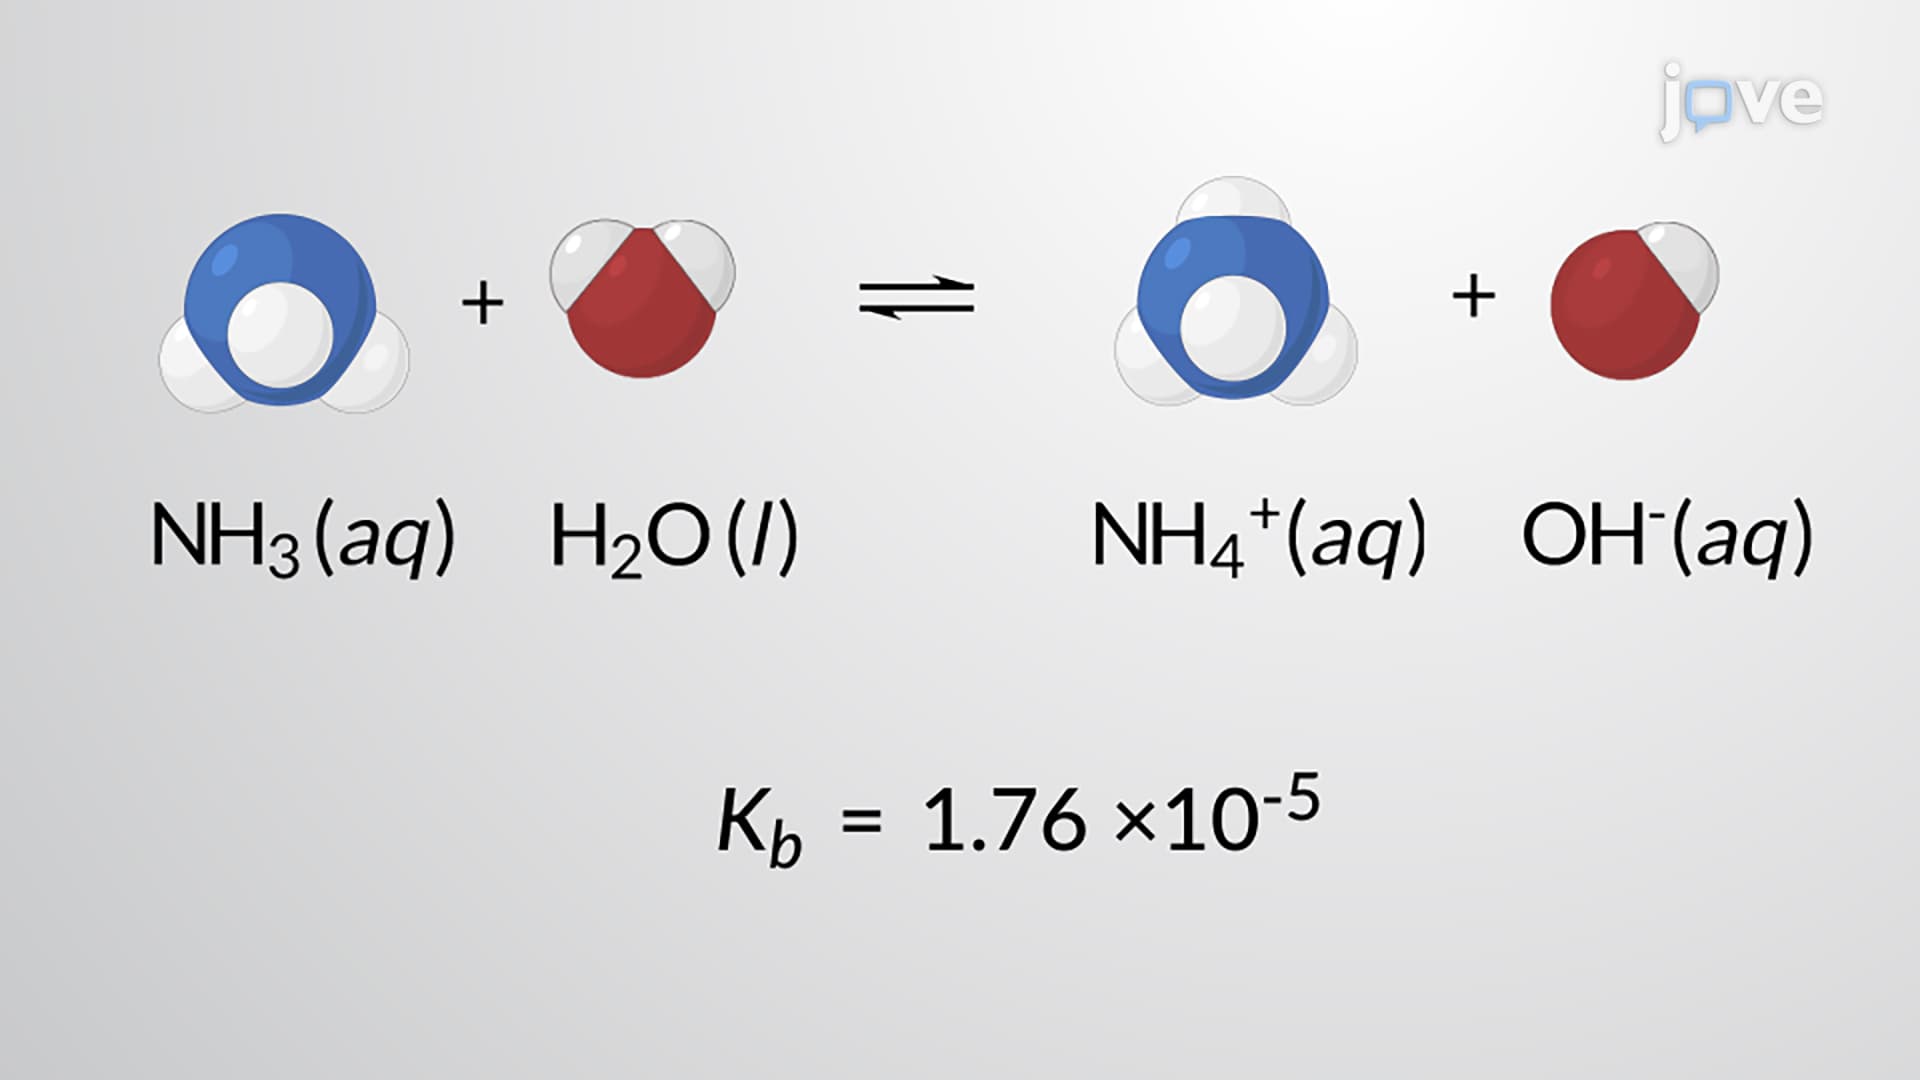 03:21
Weak Base Solutions
 02:27
DNA Base Pairing