Related Experiment Video
Updated: Jan 28, 2026
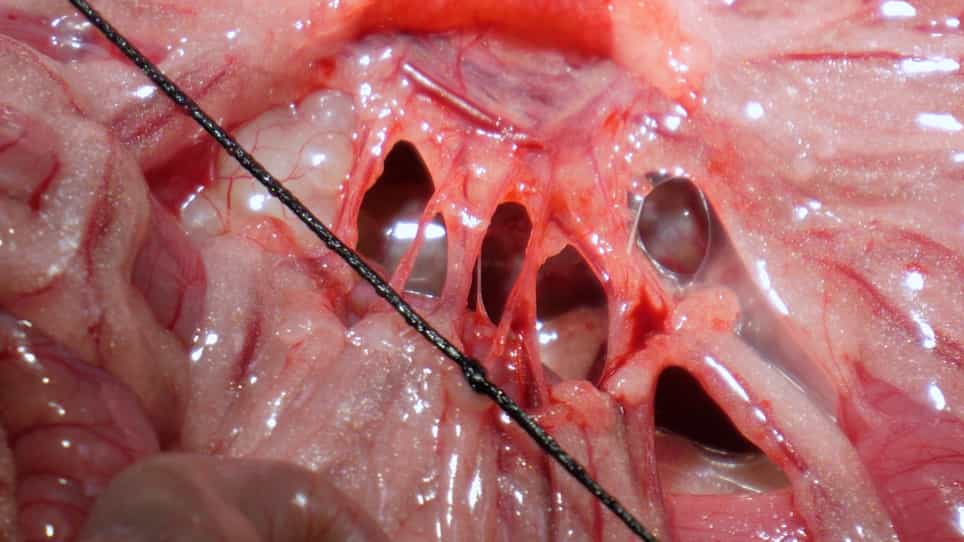

Targeting the Rat's Small Bowel: Long-Term Infusion into the Superior Mesenteric Artery
Published on: April 8, 2021
Bowel Motility After Injury to the Superior Mesenteric Plexus During D3 Extended Mesenterectomy
Yngve Thorsen1, Bojan Vladimir Stimec2, Jonas Christoffer Lindstrom3
1Institute of Clinical Medicine, University of Oslo, Oslo, Norway; Department of Digestive Surgery, Akershus University Hospital, Lorenskog, Norway.

Background:
Improvement of lymphadenectomy in right colectomy requires removal of all tissue surrounding the superior mesenteric vessels beneath the pancreatic notch. Short- and long-term bowel motility disorders after D3 extended mesenterectomy with consecutive superior mesenteric plexus transection are studied.
Methods:
Patients without pre-existing motility disorders undergoing D3 extended mesenterectomy were examined 3 times using the wireless motility capsule: before, at 3 wk, and 6 mo after surgery. Segmental transit times and contractility were analyzed using mixed effect modeling. Correlation between contractility and transit time was assessed by the Pearson correlation coefficient.
Results:
Fifteen patients (4 men), with median age 62 y, were included. Mean values for the three consecutive examinations are as follows. Gastric transit time increased from 237 to 402 and 403 min, respectively. Small bowel transit time decreased from 246 to 158 (P < 0.01) and 199 (P = 0.03) min, respectively. Colonic transit time decreased from 1742 to 1450 and 1110 (P = 0.02) min, respectively. Gastric contractions per minute (CPM) varied from 1.73 to 1.05 (P = 0.01) and 2.47 (P < 0.01), respectively. Small bowel CPM decreased from 3.43 to 2.68 and 3.34, respectively. Colonic CPM ranged from 1.59 to 1.45 and 1.91 (P = 0.08), respectively. Correlation between small bowel (SB) transit time and CPM was -0.45 (P = 0.09) preoperatively, and -0.03 (P = 0.91) 6 mo postoperatively.
Conclusions:
Extrinsic SB denervation leads to significantly accelerated SB transit, reduced contractility, and disturbed correlation between transit time and contractility early after denervation. Both number of contractions and transit time in the denervated SB show a clear tendency toward normalization at 6 mo.
Insights
D3 extended mesenterectomy with superior mesenteric plexus transection significantly alters bowel motility, accelerating small bowel transit and reducing contractility early post-surgery. However, motility shows a tendency toward normalization within six months.
Area of Science:
- Gastroenterology
- Surgical Oncology
- Colorectal Surgery
Background:
- D3 extended mesenterectomy involves removing tissue around superior mesenteric vessels.
- This procedure can lead to transection of the superior mesenteric plexus.
- Potential short- and long-term effects on bowel motility are not fully understood.
Purpose of the Study:
- To investigate short- and long-term bowel motility disorders after D3 extended mesenterectomy.
- To analyze changes in transit time and contractility following superior mesenteric plexus transection.
- To assess the correlation between bowel contractility and transit time post-surgery.
Main Methods:
- Utilized wireless motility capsule in 15 patients without pre-existing motility disorders.
- Performed examinations pre-surgery, at 3 weeks, and 6 months post-surgery.
- Analyzed segmental transit times and contractility using mixed-effects modeling and Pearson correlation.
Main Results:
- Gastric transit time increased significantly post-surgery (237 to 403 min).
- Small bowel transit time decreased significantly at 3 weeks (246 to 158 min, P < 0.01) and 6 months (P = 0.03).
- Colonic transit time decreased significantly post-surgery (1742 to 1110 min, P = 0.02).
- Small bowel contractility decreased at 3 weeks (3.43 to 2.68 CPM) but showed a tendency toward normalization at 6 months (3.34 CPM).
Conclusions:
- Extrinsic small bowel denervation accelerates transit and reduces contractility early after surgery.
- The correlation between small bowel transit time and contractility is disturbed post-denervation.
- Both small bowel transit time and contractility demonstrate a trend toward normalization by 6 months post-surgery.
More Related Videos
 06:29
Rodent Model of Intestinal Ischemia-Reperfusion Injury via Occlusion of the Superior Mesenteric Artery
Published on: October 20, 2023
 07:05
Visualization of Neutrophil Extracellular Traps in Mesenteric Venules After Mesenteric Ischemia-Reperfusion Injury via Intravital Microscopy
Published on: September 27, 2024
Related Concept Videos
 01:22
Spinal Nerves: Plexus I
The Cervical Plexus
The cervical plexus, formed by the anterior rami of the first four...
 01:21
Spinal Nerves: Plexus II
The Lumbar Plexus
The lumbar plexus is situated within the lumbar region of the back and is primarily formed by the first four lumbar spinal nerves (L1 to L4). This plexus extends its branches into several nerves, including the...
 01:16
Gastric Motility
Peristaltic Waves and Chyme Formation
Upon food entry, the stomach initiates...
 01:17
Irritable Bowel Syndrome I: Introduction
IBS is a chronic condition that can persist over a long period or recur frequently.
The pathogenesis of IBS involves a complex interplay of the following factors:
Altered...
 01:17
Chronic Bowel Disorders: Introduction
Irritable Bowel Syndrome (IBS) is a common disorder affecting the gastrointestinal tract. The distinctive feature is recurrent abdominal pain associated with altered bowel movements, manifesting as constipation, diarrhea, or fluctuating between both. The...
 01:14
Cranial Bones: Superior and Posterior View
The frontal bone is the single bone that forms the forehead. At its anterior midline, between the eyebrows, there is a slight depression called the glabella. The frontal bone also forms the supraorbital margin of the orbit. Near the middle of this margin is the supraorbital foramen, the opening that provides passage for a sensory nerve to the forehead. The frontal bone is thickened just above each supraorbital margin,...