Related Experiment Video
Updated: Jan 28, 2026
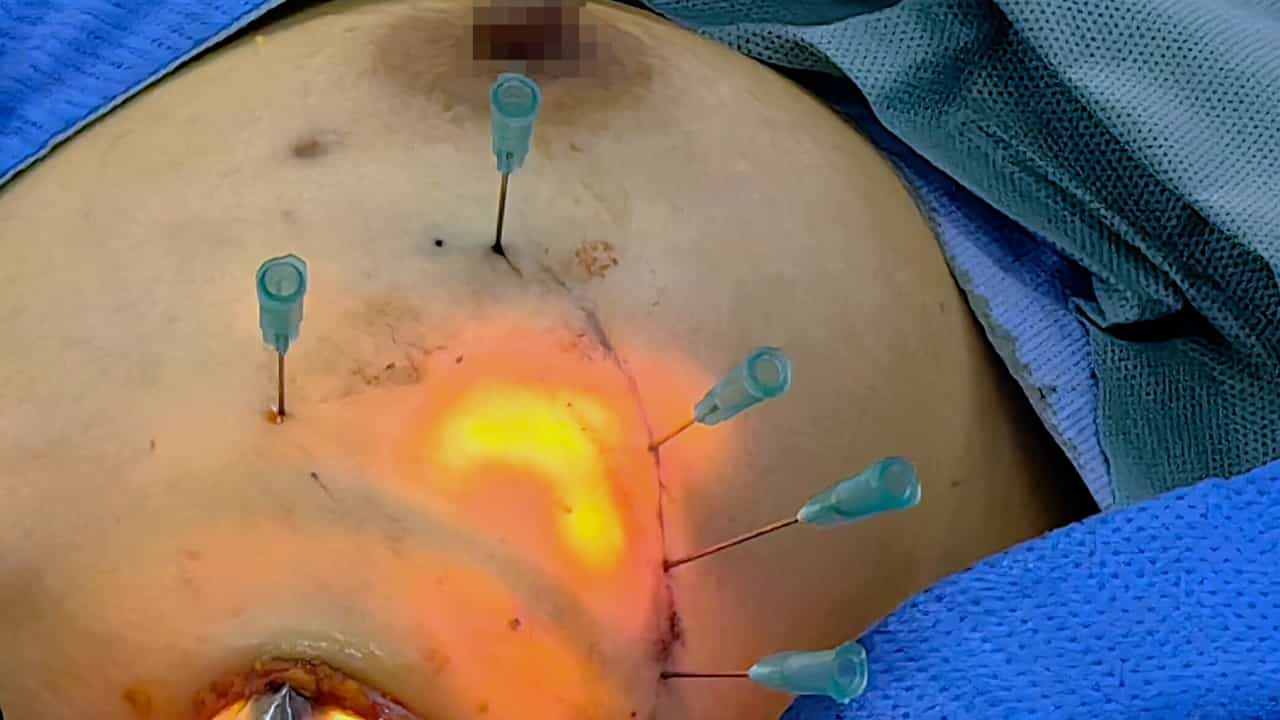
Single-Port Robotic-assisted Transaxillary Breast-conserving Surgery: A Prospective, Single-arm, Non-randomized Phase IIa Clinical Trial
Published on: August 19, 2025
Dose Escalation for Prostate Adenocarcinoma: A Long-Term Update on the Outcomes of a Phase 3, Single Institution
Dario Pasalic1, Deborah A Kuban1, Pamela K Allen1
1Department of Radiation Oncology, The University of Texas MD Anderson Cancer Center, Houston, Texas.

Purpose:
To determine the long-term outcomes for prostate adenocarcinoma when escalating radiation dose from 70 Gy to 78 Gy.
Methods And Materials:
Between 1993 and 1998, 301 patients with biopsy-proven clinical stage T1b-T3 prostate adenocarcinoma, any prostate-specific antigen level, and any Gleason score were randomized to 70 Gy in 35 fractions versus 78 Gy in 39 fractions of photon radiation therapy using a 4-field box technique without hormone deprivation therapy. The primary outcome was powered to detect a 15% difference in biochemical or clinical failure. Secondary outcomes included survival, prostate cancer mortality, biochemical failure, local failure, nodal failure, distant failure, and secondary malignancy rates.
Results:
With a median follow-up of 14.3 years, the cumulative incidence of 15-year biochemical or clinical failure was 18.9% versus 12.0% in the 70 Gy versus 78 Gy arms, respectively (subhazard ratio [sHR], 0.61; 95% confidence interval [CI], 0.38-0.98; Fine-Gray P = .042). The 15-year cumulative incidence of distant metastasis was 3.4% versus 1.1%, respectively (sHR, 0.33; 95% CI, 0.13-0.82; Fine-Gray P = .018). The 15-year cumulative incidence of prostate cancer-specific mortality was 6.2% versus 3.2%, respectively, (sHR, 0.52; 95% CI, 0.27-0.98; Fine-Gray P = .045). There were no differences in overall survival (HR, 1.10; 95% CI, 0.84-1.45; log rank P = .469) or other-cause survival (sHR, 1.33; 95% CI, 0.99-1.79; Fine-Gray P = .061). Salvage therapy was more common in the 70 Gy arm, at 38.7% versus 21.9% in the 78 Gy arm (P = .002). There was a 2.3% secondary solid malignancy rate (1 bladder, 6 rectal) within the radiation treatment field, which was not significantly different between treatment arms.
Conclusions:
Dose escalation by 8 Gy (78 Gy vs 70 Gy) provided a sustained improvement in biochemical and clinical failure, which translated into lower salvage rates and improved prostate cancer-specific mortality, but not overall survival. Long-term follow-up demonstrated a low incidence of potential solid tumor secondary malignancies.

Related Concept Videos
 01:16
Clinical Trials
There are four phases in a clinical trial. A phase one...
 01:11
Clinical Trials: Overview
 01:28
Inductance: Single-Phase And Three-Phase Line
Single-Phase Two-Wire Line:
A single-phase line consists of two solid cylindrical conductors, denoted as x and y. Each conductor carries phasor currents ix and iy, respectively. Given that the sum of these currents is...
 01:25
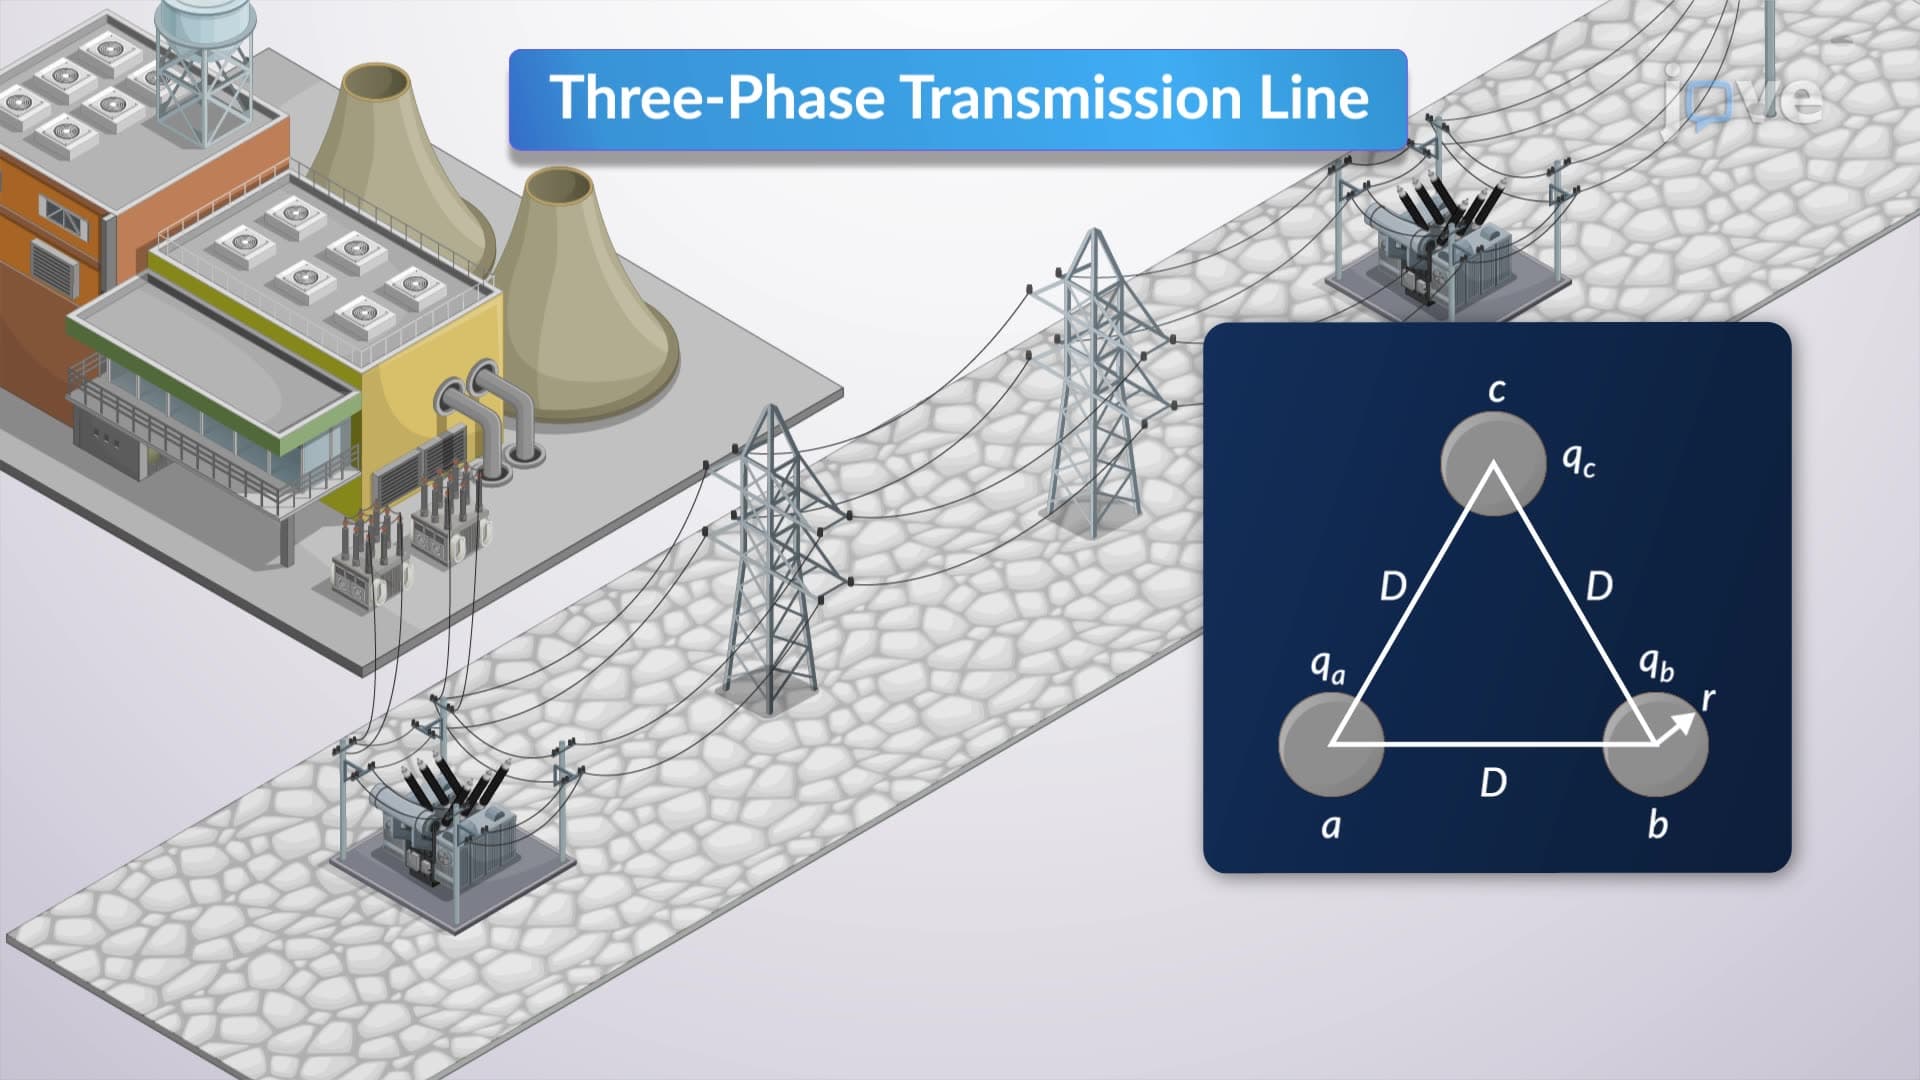
Capacitance: Single-Phase And Three-Phase Line
Single-Phase Lines
Consider a single-phase, two-wire transmission line with equal phase spacing energized by a voltage source. One conductor carries a uniform positive charge, while the other carries an equal negative charge. The capacitance C of the line can be derived from the voltage V between the conductors. For a one-meter section of the line, the capacitance is given...
 01:12
Statistical Software for Data Analysis and Clinical Trials
 01:17
Power Distribution in Three-phase and Single Phase Circuits
Single-Phase Power Distribution:
Single-phase circuits are typical in household settings;...