Related Experiment Video
Updated: Aug 16, 2026

Bedside Ultrasound for Guiding Fluid Removal in Patients with Pulmonary Edema: The Reverse-FALLS Protocol
Published on: July 28, 2018
Furosemide pharmacodynamics: effect of respiratory and acid-base disturbances

Abstract:
The aims of this study were to investigate the effect of changes in arterial blood gases and pH on furosemide pharmacodynamics and kinetics. Five groups of conscious rabbits were used: a control group breathing air with normoxia and normocarbia; a second group with hypercapnia and respiratory acidosis; a third with hypoxemia; a fourth with hypercapnia and respiratory acidosis combined with hypoxemia (HCHO); and the fifth group with metabolic acidosis. All experimental conditions, except hypoxemia, increased sodium tubular reabsorption and therefore, decreased urinary excretion of sodium. Renal blood flow was decreased by HCHO and metabolic acidosis. In response to 5 mg/kv i.v. of furosemide, natriuresis and diuresis were decreased by an average of 44% in animals with HCHO (P less than .05). The kinetics of furosemide were not affected by any of the experimental conditions except HCHO, in which the renal clearance of furosemide was reduced from 7.5 +/- 1.4 ml/min/kg (controls) to 2.7 +/- 0.7 ml/min/kg (P less than .05). The reduction in renal clearance of furosemide was associated with a decrease in urinary excretion of sodium (P less than .05). The reduction in renal clearance of furosemide was probably secondary to the decrease in renal blood flow and an increase in furosemide tubular reabsorption. Finally, HCHO did not decrease plasma volume, suggesting that the reduction in renal blood flow was secondary to blood flow distribution. In conclusion, only hypercapnia and respiratory acidosis combined with hypoxemia decreases the natriuretic and diuretic effect of furosemide.
More Related Videos
 10:18
Real-Time, Semi-Automated Fluorescent Measurement of the Airway Surface Liquid pH of Primary Human Airway Epithelial Cells
Published on: June 13, 2019
 09:36
Halogenated Agent Delivery in Porcine Model of Acute Respiratory Distress Syndrome via an Intensive Care Unit Type Device
Published on: September 24, 2020
Related Concept Videos
 01:28
Antihypertensive Drugs: Potassium-Sparing Diuretics
 01:22
Heart Failure Drugs: Diuretics
 01:18
Respiratory Regulation of Acid-Base Balance
When carbon dioxide levels increase in the blood, more H+ and HCO3⁻ are produced, leading to a...
 01:29
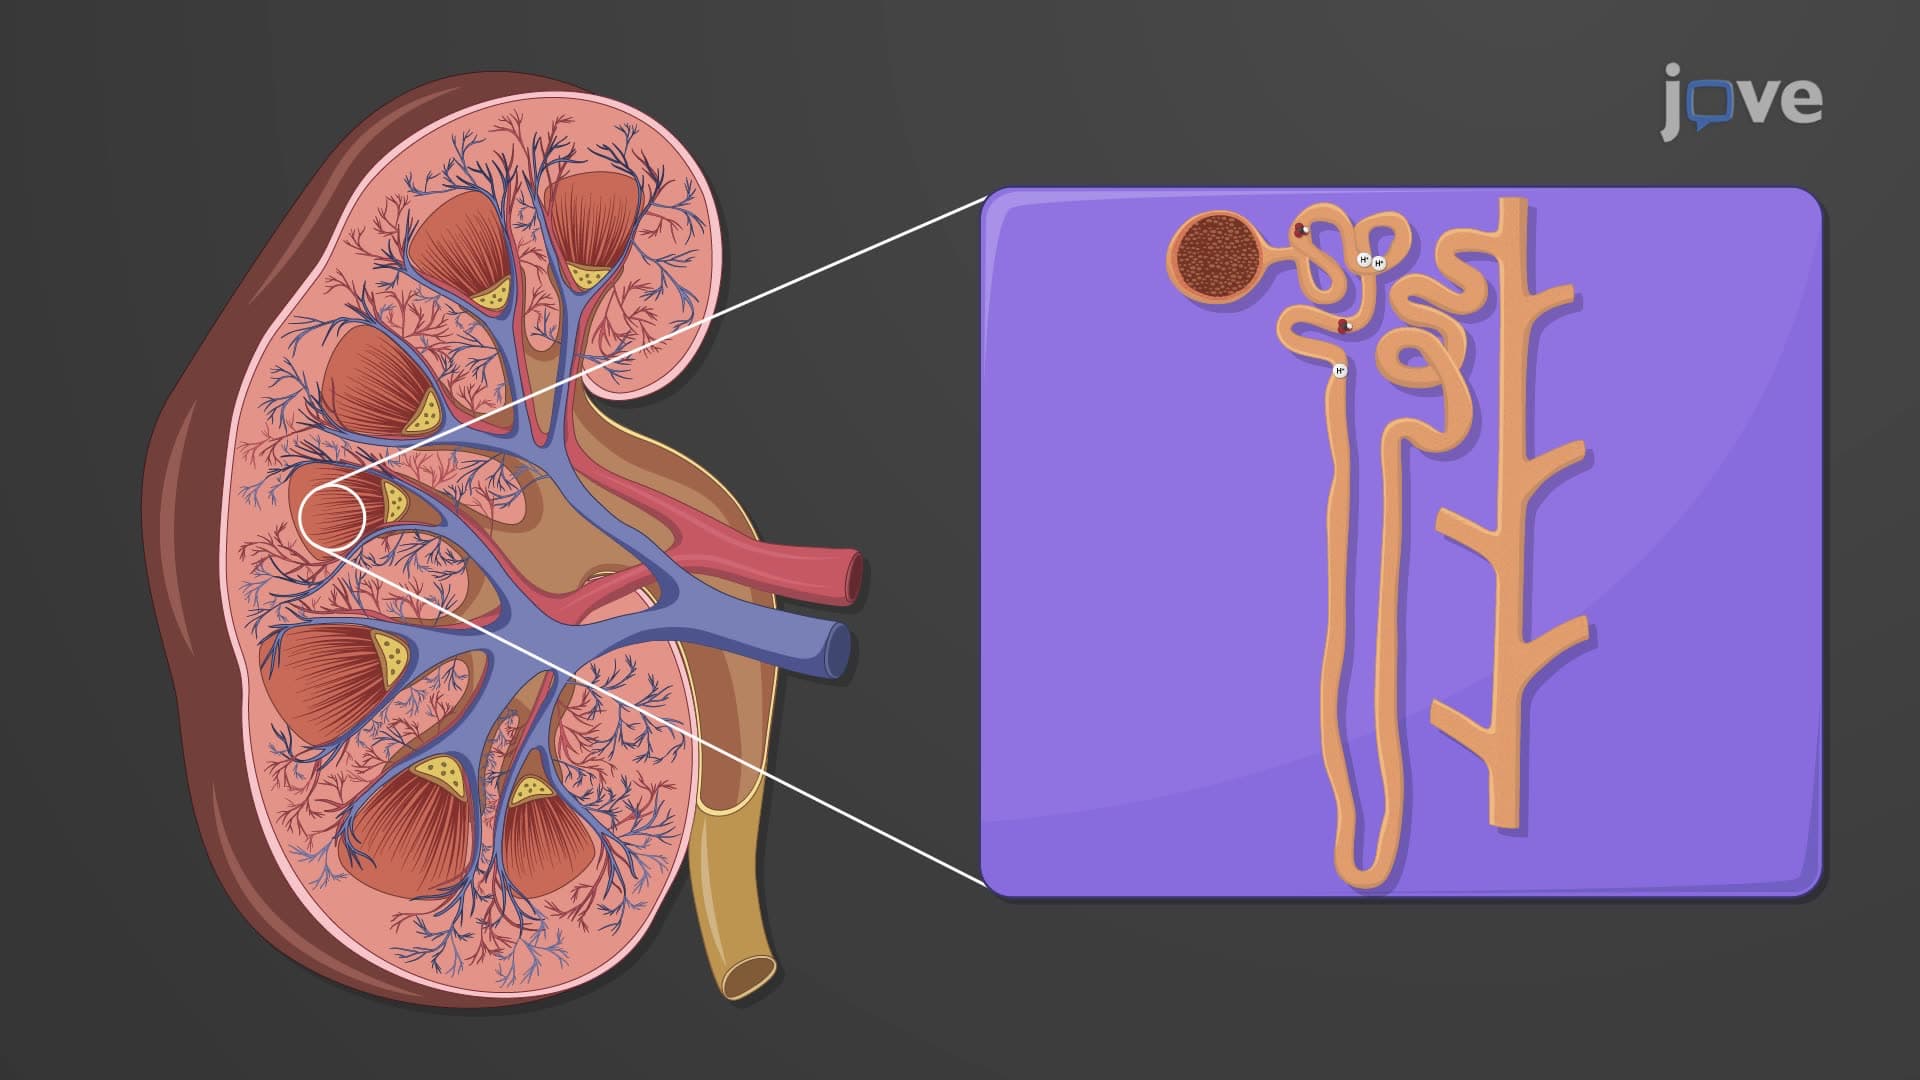
Renal Regulation of Acid-Base Balance
In the kidneys, cells within the proximal convoluted tubules (PCT) and the collecting ducts secrete hydrogen ions (H+) into the tubular fluid. Specifically, in the PCT, Na+/H+ antiporters secrete H+ while reabsorbing Na+.
However, the intercalated cells in...
 01:22
Renal Drug Excretion: Effect of Urine pH, Flow Rate, and Drug pKa
The pKa of a drug,...
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...