Risk factors and outcomes for bowel ischemia after open and endovascular abdominal aortic aneurysm repair
Related Experiment Video
Updated: Jan 28, 2026
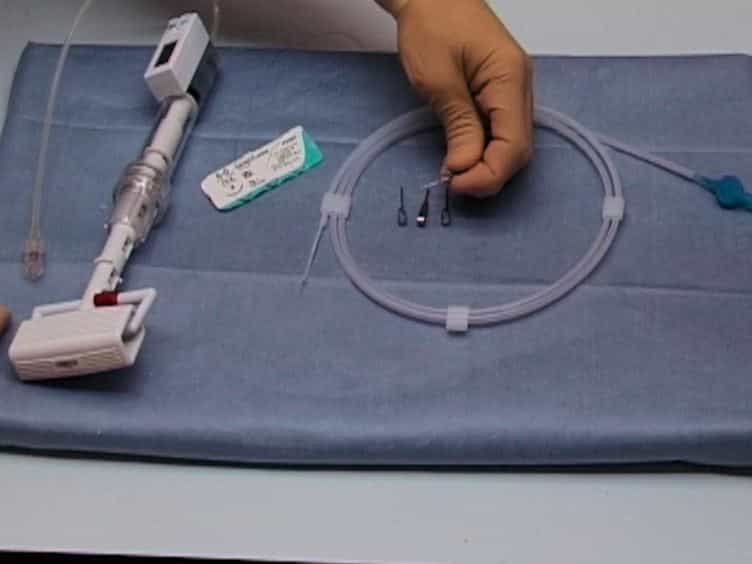
A New Murine Model of Endovascular Aortic Aneurysm Repair
Published on: July 7, 2013
Merve Gurakar1, Satinderjit Locham2, Husain N Alshaikh3
1Johns Hopkins Bloomberg School of Public Health, Baltimore, Md.

Objective:
Bowel ischemia (BI) is a serious complication after abdominal aortic aneurysm (AAA) repair. We sought to identify the incidence and risk factors associated with the development of postoperative BI and the post-BI outcomes for patients undergoing open aortic repair (OAR) and endovascular aortic repair (EVAR) of AAAs.
Methods:
A retrospective analysis was conducted for all patients who had undergone OAR or EVAR from 2003 to 2017 using the Vascular Quality Initiative database. Univariate (Student's t test, χ2, median) and multivariable (logistic regression) analyses were used to identify independent factors associated with postoperative BI and compare the post-BI in-hospital outcomes and mortality.
Results:
We identified 45,474 patients who had undergone infrarenal AAA repair (OAR, 21.5%; EVAR, 78.5%). The overall incidence of postoperative BI was 1.9% (OAR, 6.2% vs EVAR, 0.8%; P < .001). OAR was associated with a threefold increased odds of BI compared with EVAR (adjusted odds ratio [aOR], 3.24; 95% confidence interval [CI], 2.49-4.22; P < .001). The independent factors associated with BI after OAR included older age (aOR per year of age, 1.02; 95% CI, 1.00-1.03), congestive heart failure (aOR, 1.44; 95% CI, 1.05-1.98), and ruptured aneurysm (aOR, 4.16; 95% CI, 2.98-5.81; P < .01 for all). We also found that transfusion ≥1 U (aOR, 1.69; 95% CI, 1.30-2.20), a transperitoneal approach (aOR, 2.13; 95% CI, 1.03-1.87), supraceliac clamping (aOR, 1.58; 95% CI, 1.08-2.33), and inferior mesenteric artery reimplantation (aOR, 1.41; 95% CI, 1.06-1.89) were associated with greater odds of BI after OAR (P < .01 for all). Similarly, we found that ruptured aneurysms, a longer operative time, and transfusion of ≥1 U of blood were associated with BI after EVAR (P < .001 for all). For both OAR and EVAR, the postoperative stay (median, 13 days [interquartile range (IQR), 7-26 days] vs 7 days [IQR, 5-10 days] and 11 days [IQR, 4-23 days] vs 1 day [IQR, 1-3 days], respectively) and 30-day mortality (35.0% vs 6.4% and 40.5% vs 1.9%, respectively) were significantly higher for patients with BI (P < .001 for all). The predictors of mortality for patients with BI were surgical management (aOR, 2.05; 95% CI, 1.28-3.30), older age (aOR, 1.05; 95% CI, 1.02-1.07), symptomatic aneurysm (aOR, 1.26; 95% CI, [0.60-2.62), ruptured aneurysm (aOR, 2.23; 95% CI, 1.43-3.48), longer operative time (aOR, 1.11; 95% CI, 1.01-1.22), and postoperative renal complications (aOR, 2.98; 95% CI, 1.80-4.96; P < .05 for all).
Conclusions:
Confirming the results from previous studies, we found that BI is more common after a ruptured aneurysm and OAR. Other associated intraoperative factors included a transperitoneal approach, supraceliac clamping, and a reimplanted inferior mesenteric artery. More than one third of patients who developed postoperative BI in our cohort had died within 30 days after AAA repair. The factors associated with mortality after BI included surgical management and postoperative renal failure. A high index of suspicion for the signs and symptoms of BI should be maintained postoperatively for patients presenting with the risk factors identified.

Related Concept Videos
 01:26
Factors Affecting the Risk of Infection
The integrity and count of the white blood cells help the body resist pathogens and fight infection. When impaired, it reduces the body's resistance to pathogens. The acidic pH levels of the gastrointestinal, genitourinary tracts, and skin...
 01:36
Mismatch Repair
 01:02
Long-patch Base Excision Repair
 02:25
Overview of DNA Repair
Chemically...
 01:54
Base Excision Repair
The first step of...
 01:08
Nucleotide Excision Repair