Related Experiment Video
Updated: Jan 28, 2026
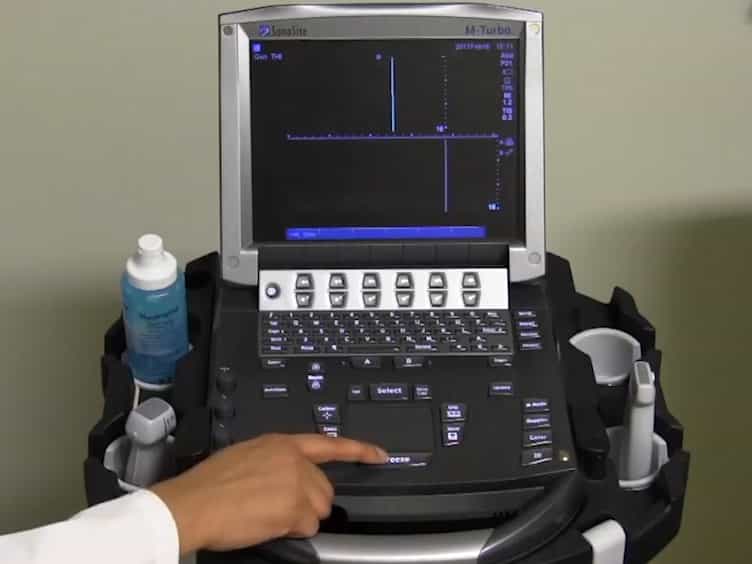

Bedside Ultrasound for Guiding Fluid Removal in Patients with Pulmonary Edema: The Reverse-FALLS Protocol
Published on: July 28, 2018
Successful Summit of Two 8000 m Peaks After Recent High Altitude Pulmonary Edema
Suvash Dawadi1, Subarna Adhikari2
1CIWEC Hospital and Travel Medicine Center, Kathmandu, Nepal; Mountain Medicine Society of Nepal, Kathmandu, Nepal.

Abstract:
There is little information in the literature on the safety of reascent to high altitude shortly after resolution of severe acute altitude illness, including high altitude pulmonary or cerebral edema. We present a case of a 52-y-old male climber who was diagnosed with high altitude pulmonary edema during the 2018 Everest spring climbing season, descended to low altitude for 9 d, received treatment, and returned to continue climbing with a very rapid ascent rate. Despite a very recent history of high altitude pulmonary edema and not using pharmacologic prophylaxis over a very rapid reascent profile, the climber successfully summited Mt. Everest (8848 m) and Lhotse (8516 m) without any problems.

Related Concept Videos
 02:17
Ecological Succession
 01:08
IR Spectrum Peak Splitting: Symmetric vs Asymmetric Vibrations
 00:55
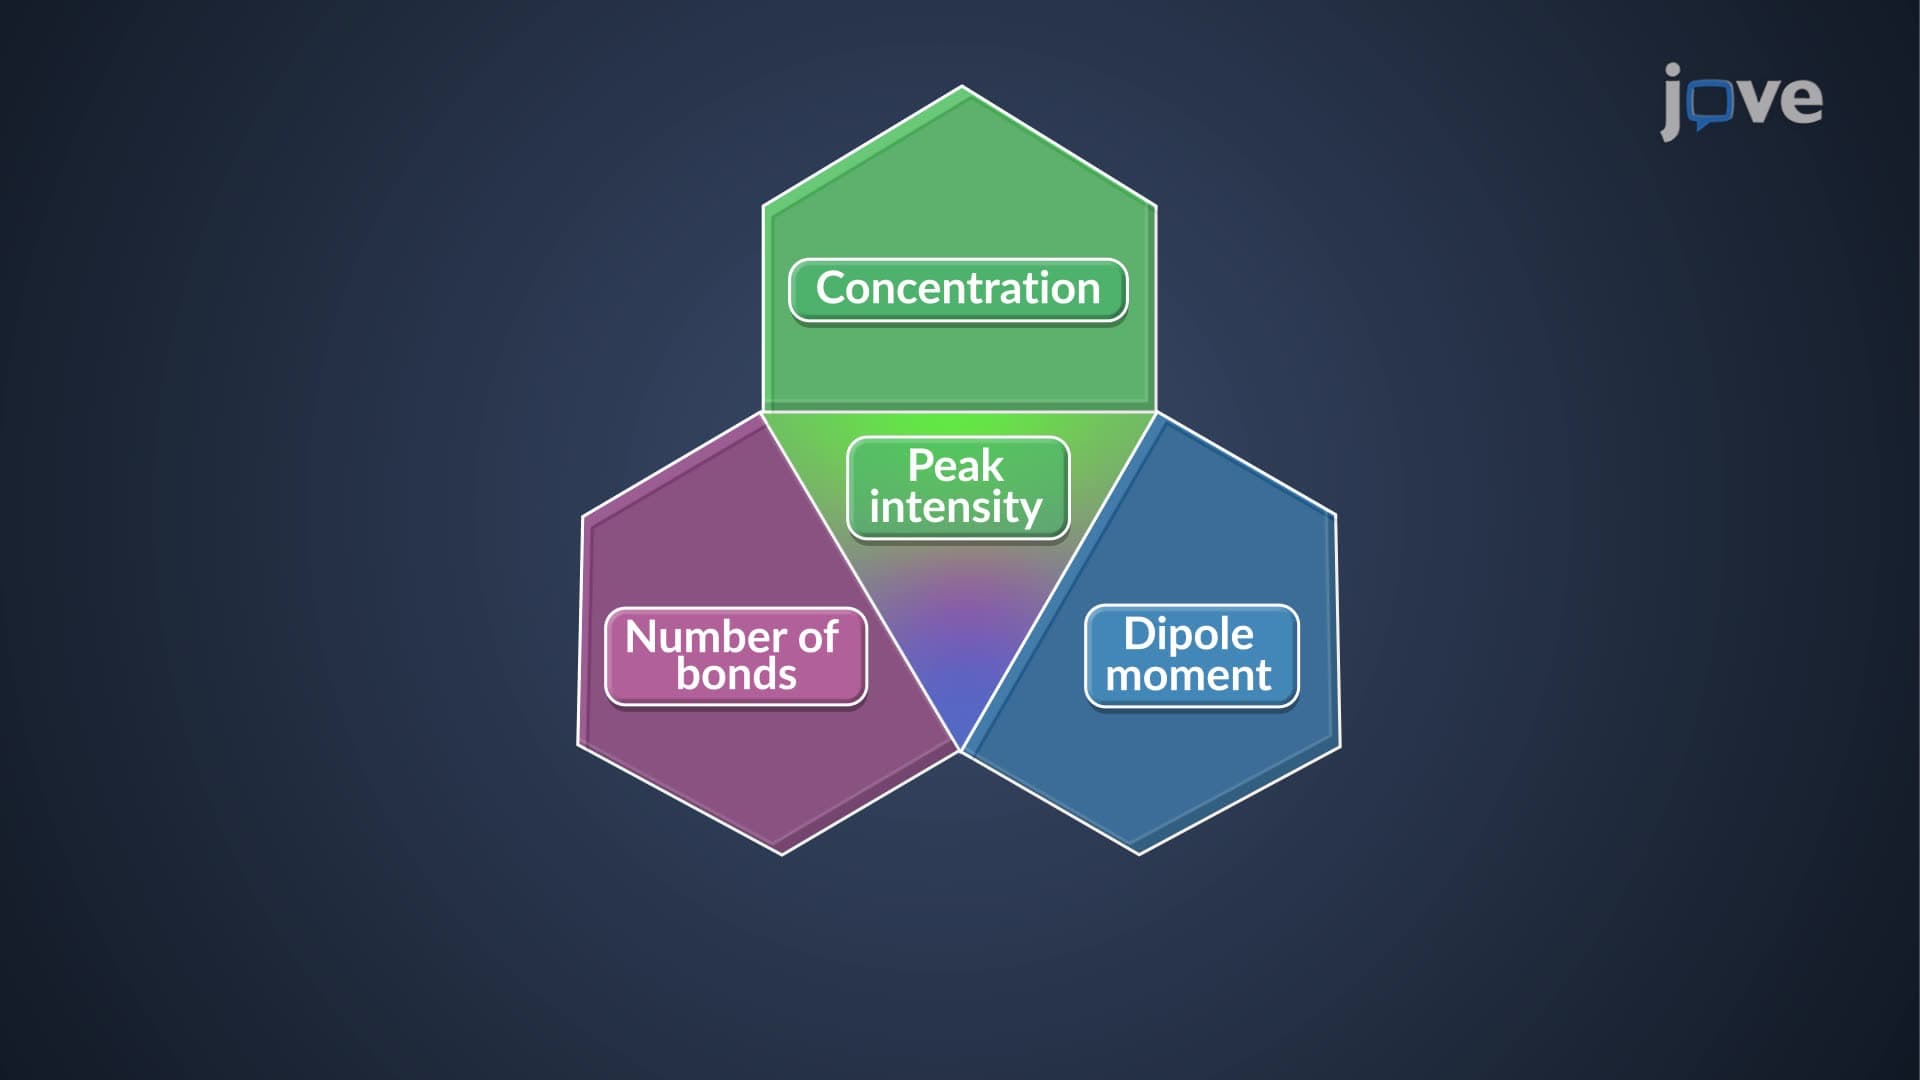
IR Spectrum Peak Intensity: Amount of IR-Active Bonds
 01:23
IR Spectrum Peak Broadening: Hydrogen Bonding
However, the extent of hydrogen bonding influences the observed stretching frequency and band broadening. Intermolecular or intramolecular...
 01:20
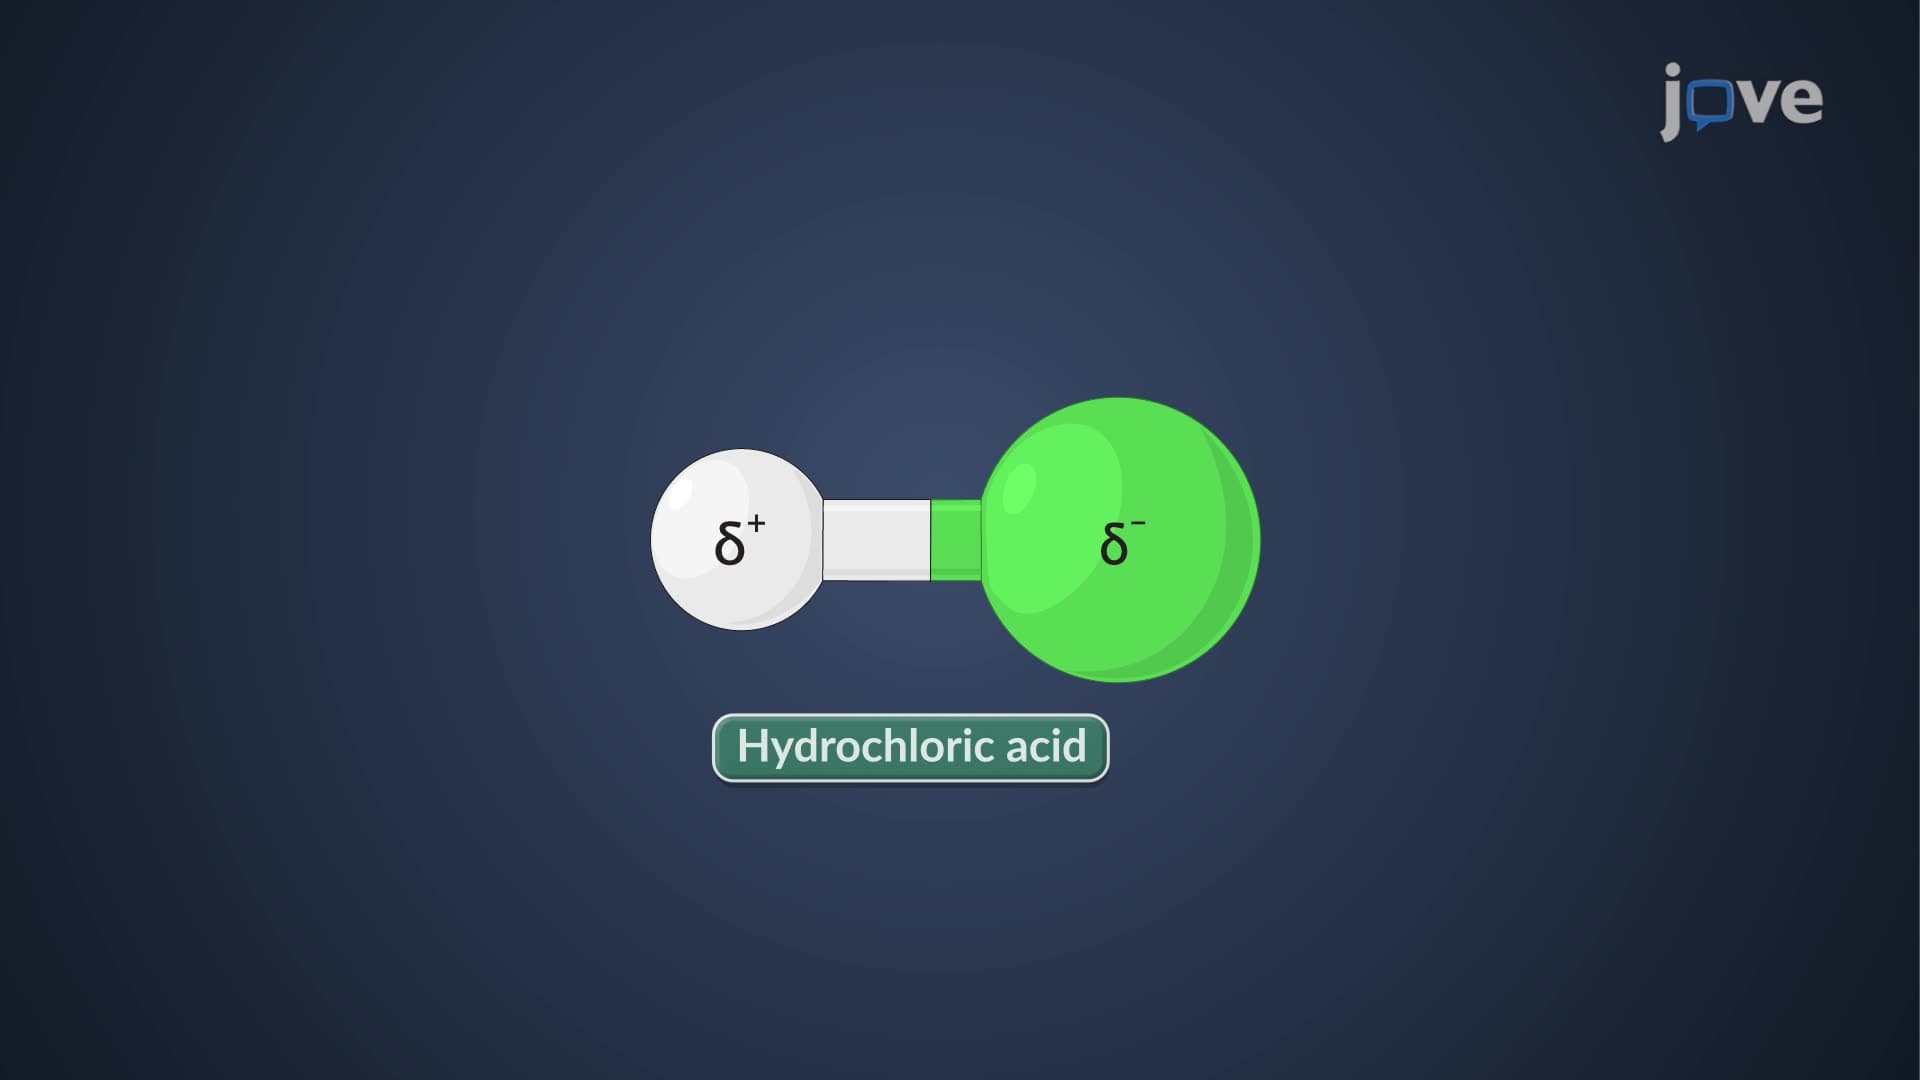
IR Spectrum Peak Intensity: Dipole Moment
 01:29
Pulmonary Tuberculosis I
Causative Organism
The primary infectious agent causing tuberculosis is Mycobacterium tuberculosis, a slow-growing, acid-fast, aerobic rod that exhibits sensitivity to heat and ultraviolet light. Instances of Mycobacterium bovis and Mycobacterium avium contributing to the development of TB infection are rare.
Mode of...