Related Experiment Video
Updated: Jan 27, 2026
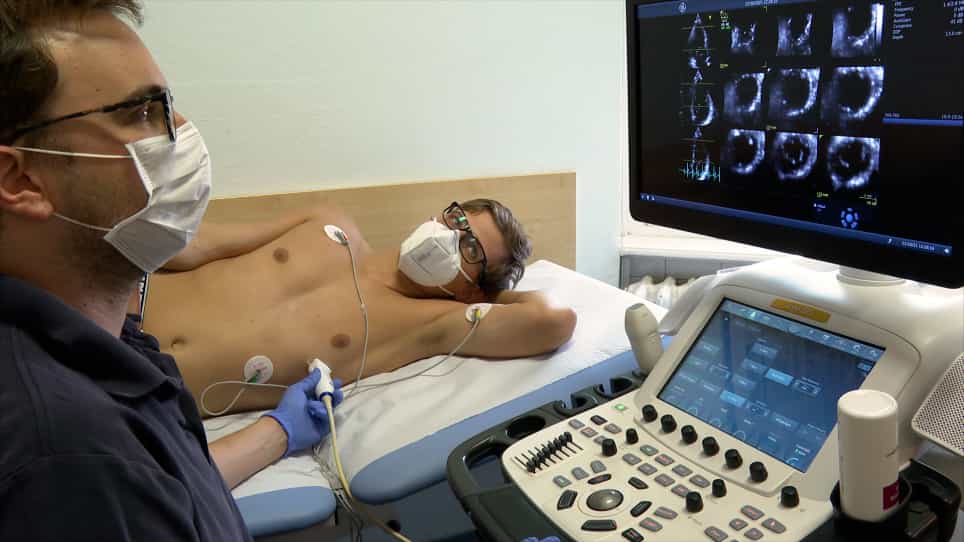

Evaluation of Left Ventricular Structure and Function using 3D Echocardiography
Published on: October 28, 2020
Accuracy of Left Ventricular Cavity Volume and Ejection Fraction for Conventional Estimation Methods and 3D Surface
11 Department of Radiation Oncology University of Florida College of Medicine Gainesville FL.

Insights
Estimating left ventricular volume (LVV) and ejection fraction (LVEF) has significant errors. A 3D surface model using multiple views dramatically improves accuracy for better cardiac disease detection.
Area of Science:
- Cardiovascular Imaging
- Medical Physics
- Biomedical Engineering
Background:
- Left ventricular cavity volume (LVV) and ejection fraction (LVEF) are critical for clinical decisions.
- Current estimation methods have underappreciated and unquantified clinical errors.
Purpose of the Study:
- To rigorously quantify the accuracy and precision of common geometric-model-based LVV and LVEF estimation methods.
- To evaluate the impact of slice number and orientation on LVV and LVEF accuracy.
Main Methods:
- Utilized a high-resolution magnetic resonance imaging dataset with an independent ground truth.
- Assessed various geometric modeling techniques, including short-axis, long-axis, and combined 3D surface models.
- Investigated the influence of slice count and orientation on measurement uncertainty.
Main Results:
- Standard methods with limited views can yield LVEF uncertainty up to 49%.
- A 3D surface model incorporating multi-view anatomical data achieved superior accuracy: LVEF error <4% and LVV error <2.5% with 6 slices per view.
- Combined 3D models significantly outperformed methods relying solely on short-axis images.
Conclusions:
- Integrating multi-view anatomical data into conformal 3D surface models substantially reduces LVV and LVEF estimation errors.
- This improved accuracy holds significant potential for earlier and more reliable cardiac disease detection in clinical practice.
Abstract:
Background While left ventricular cavity volume ( LVV ) and ejection fraction ( LVEF ) are used routinely for clinical decision-making, the errors in LVV and LVEF estimates in the clinic have yet to be rigorously quantified and are perhaps underappreciated. Methods and Results The goal of this study was to quantify the accuracy and precision of several common geometric-model-based methods for estimating LVV and LVEF using a highly sampled, high-resolution magnetic resonance imaging data set and an independent ground truth. The effect on LVV and LVEF accuracy of slice number and orientation was also studied. When using the common geometric assumptions and limited short- and/or long-axis views, the expected LVEF measurement uncertainty can be as high as 49%. The composite midpoint rule applied to a stack of short-axis slices can achieve LVEF error <3% and LVV error of ≈10%, but in the clinic an additional ≈8% uncertainty is expected. An analogous approach applied to a series of radially prescribed long-axis slices can achieve higher LVEF accuracy, up to 3.9% with 12 slices, and more reliable LVV measurements than methods based solely on short-axis images. Using a mathematical 3-dimensional surface model that incorporates anatomic information from multiple views achieves superior accuracy, with LVEF error <4% and LVV error <2.5% when using 6 slices in each short- and long-axis view. Conclusions Combining anatomical information from multiple views into a conformal 3-dimensional surface model greatly reduces errors in LVV and LVEF estimates, with potential clinical benefit via improved early detection of cardiac disease.


Related Concept Videos
 01:15
Line, Surface, and Volume Integrals
 02:07
Improving Translational Accuracy
 01:13
Induced-fit Model
Enzymes exhibit substrate specificity, meaning that they can only bind to certain substrates. This is mainly determined by the shape and chemical...
 03:37
Uncertainty in Measurement: Accuracy and Precision
 00:57
Inclusive Fitness
 01:16
Goodness-of-Fit Test