Related Experiment Video
Updated: Jan 27, 2026
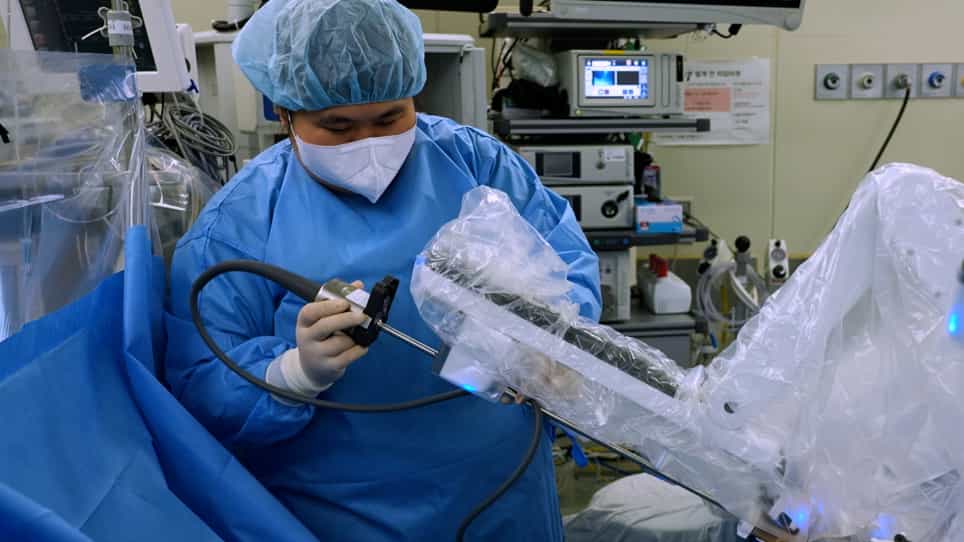

Robot-Assisted Kidney Transplantation
Published on: July 19, 2021
Kidney Transplantation After Hematopoietic Cell Transplantation in Plasma Cell Dyscrasias: Case Reports
V Domínguez-Pimentel1, A Rodríguez-Muñoz1, M Froment-Brum1
1Nephrology Service, University Hospital Nuestra Señora de Candelaria, Santa Cruz de Tenerife, Spain.

Insights
Hematopoietic cell transplant (HCT) followed by kidney transplant (KT) can be an optimal treatment for plasma cell dyscrasias (PCDs) with renal impairment. Careful management of immunosuppression and potential complications is crucial for successful outcomes.
Area of Science:
- Nephrology
- Hematology
- Oncology
Background:
- Plasma cell dyscrasias (PCDs) like multiple myeloma frequently cause renal impairment, necessitating treatment.
- Hematopoietic cell transplant (HCT) offers a cure for PCDs but can complicate management of renal disease.
- Kidney transplant (KT) is an alternative for end-stage renal disease, but its use after HCT is sparsely documented.
Observation:
- This study reports on 4 patients with PCD who underwent HCT followed by KT.
- The study observed the outcomes of KT in patients with a history of HCT.
Findings:
- The study found that KT after HCT in PCD patients yielded optimal progress and outcomes.
- Key considerations include managing potential cytopenia from combined immunosuppression and increased risks of infection and PCD relapse.
Implications:
- Kidney transplant (KT) following hematopoietic cell transplant (HCT) is a viable option for PCD patients with renal failure.
- Optimal adjustment of immunosuppression and vigilant monitoring for infections and disease relapse are essential for successful KT post-HCT.
Abstract:
The plasma cell dyscrasias (PCDs) include a number of entities such as multiple myeloma, primary amyloidosis, and monoclonal immunoglobulin deposition disease. Hematopoietic cell transplant (HCT) is the only cure for a variety of hematologic and oncologic diseases. Clinically significant renal impairment is a common feature in plasma cell myeloma, affecting 20% to 55% of patients at initial diagnosis; 2% to 3% of patients present with failure sufficiently severe to require hemodialysis. This circumstance is associated with a high early mortality. The necessity for immunosuppression after HCT could complicate its management and may precipitate the development of complications. In some patients an effective alternative could be kidney transplant (KT); however, the presence of 2 transplants will require optimal adjustment of immunosuppression and management of complications. At present, there are few published cases of KT after HCT, and the experience of managing 2 transplants is limited. We would like to describe our experience with 4 patients who had a PCD and initially received HCT and received subsequent KT. In our experience the progress and outcome of KT after HCT were optimal. We would like to address that a higher incidence of cytopenia associated with the combination of immunosuppression (lenalidomide, tacrolimus, mycophenolate, etc.) and other drugs (ie, valganciclovir) should be considered together with an increased risk of opportunistic infections and PCD relapse.
Related Concept Videos
 01:28
Kidney Transplant I: Introduction
 01:26
Kidney Transplant II: Surgical Procedure
 01:16
Kidney Transplant III: Nursing Management
 01:24
Tissue Transplantation
The Biology of Tissue Transplantation
The biology of tissue transplantation hinges on the Major Histocompatibility Complex (MHC) molecules. These molecules...
 01:19
Multipotency of Hematopoietic Stem Cells
 01:01
Regulation of Hematopoietic Stem Cells