Related Experiment Video
Updated: Jan 27, 2026


Postconditioning with Lactate-enriched Blood for Cardioprotection in ST-segment Elevation Myocardial Infarction
Published on: May 28, 2019
Coronary Angiography after Cardiac Arrest without ST-Segment Elevation
Jorrit S Lemkes1, Gladys N Janssens1, Nina W van der Hoeven1
1From the Departments of Cardiology (J.S.L., G.N.J., N.W.H., N.R.), Intensive Care Medicine (P.W.G.E., H.M.O.-S.), and Epidemiology and Biostatistics (P.M.V.), Amsterdam University Medical Center VUmc, the Departments of Cardiology (J.P.H.) and Intensive Care Medicine (A.P.J.V.), Amsterdam University Medical Center AMC, and the Departments of Cardiology (M.A.V.) and Intensive Care Medicine (B.B.), Onze Lieve Vrouwe Gasthuis, Amsterdam, the Thorax Center, Erasmus Medical Center (L.S.D.J., E.A.D.), and the Departments of Cardiology (G.J.V.) and Intensive Care Medicine (B.J.W.E.), Maasstad Hospital, Rotterdam, the Departments of Cardiology (M. Meuwissen) and Intensive Care Medicine (T.A.R.), Amphia Hospital, Breda, the Departments of Cardiology (H.A.B.) and Intensive Care Medicine (M.J.B.), Rijnstate Hospital, Arnhem, the Departments of Cardiology (G.B.B.) and Intensive Care Medicine (R.B.), Haga Hospital, and the Department of Cardiology, Haaglanden Medical Center (P.V.O.), The Hague, the Departments of Cardiology (P.H.) and Intensive Care Medicine (I.C.C.H.), University of Groningen, Groningen, the Departments of Cardiology (M.V.) and Intensive Care Medicine (J.J.H.), University Medical Center Utrecht, Utrecht, the Departments of Intensive Care Medicine (A.B.) and Cardiology (M.S.), Medisch Spectrum Twente, Enschede, the Departments of Cardiology (C.C., N.R.) and Intensive Care Medicine (H.H.), Radboud University Medical Center, Nijmegen, the Departments of Cardiology (T.A.C.M.H.) and Intensive Care Medicine (W.R.), Noordwest Ziekenhuisgroep, Alkmaar, the Departments of Intensive Care Medicine (T.S.R.D.) and Cardiology (H.J.G.M.C.), Maastricht University Medical Center, Maastricht, the Department of Cardiology, Scheper Hospital, Emmen (G.A.J.J.), the Department of Cardiology, Isala Hospital, Zwolle (M.T.M.G.), the Department of Cardiology, Tergooi Hospital, Blaricum (K.P.), and the Department of Cardiology, Elisabeth-Tweesteden Hospital, Tilburg (M. Magro) - all in the Netherlands.

Insights
Immediate coronary angiography after cardiac arrest without STEMI is not superior to delayed angiography for 90-day survival. This finding impacts treatment strategies for cardiac arrest patients, guiding decisions on urgent cardiac interventions.
Area of Science:
- Cardiology
- Emergency Medicine
- Critical Care Medicine
Background:
- Ischemic heart disease is a leading cause of out-of-hospital cardiac arrest.
- The optimal timing for coronary angiography and percutaneous coronary intervention (PCI) in successfully resuscitated cardiac arrest patients without ST-segment elevation myocardial infarction (STEMI) is unclear.
Purpose of the Study:
- To compare the efficacy of immediate versus delayed coronary angiography in patients resuscitated from cardiac arrest without STEMI.
Main Methods:
- A multicenter trial randomized 552 cardiac arrest patients (no STEMI) to immediate or delayed coronary angiography.
- Percutaneous coronary intervention (PCI) was performed as indicated.
- The primary endpoint was 90-day survival; secondary endpoints included neurological status and organ injury.
Main Results:
- 90-day survival was similar: 64.5% in the immediate group vs. 67.2% in the delayed group (OR, 0.89; 95% CI, 0.62-1.27; P=0.51).
- Median time to target temperature was slightly longer in the immediate group (5.4 hours vs. 4.7 hours).
- No significant differences were observed in secondary endpoints between the groups.
Conclusions:
- Immediate coronary angiography does not improve 90-day survival compared to delayed angiography in cardiac arrest survivors without STEMI.
- The findings suggest that a delayed strategy is a viable option for these patients.
Background:
Ischemic heart disease is a major cause of out-of-hospital cardiac arrest. The role of immediate coronary angiography and percutaneous coronary intervention (PCI) in the treatment of patients who have been successfully resuscitated after cardiac arrest in the absence of ST-segment elevation myocardial infarction (STEMI) remains uncertain.
Methods:
In this multicenter trial, we randomly assigned 552 patients who had cardiac arrest without signs of STEMI to undergo immediate coronary angiography or coronary angiography that was delayed until after neurologic recovery. All patients underwent PCI if indicated. The primary end point was survival at 90 days. Secondary end points included survival at 90 days with good cerebral performance or mild or moderate disability, myocardial injury, duration of catecholamine support, markers of shock, recurrence of ventricular tachycardia, duration of mechanical ventilation, major bleeding, occurrence of acute kidney injury, need for renal-replacement therapy, time to target temperature, and neurologic status at discharge from the intensive care unit.
Results:
At 90 days, 176 of 273 patients (64.5%) in the immediate angiography group and 178 of 265 patients (67.2%) in the delayed angiography group were alive (odds ratio, 0.89; 95% confidence interval [CI], 0.62 to 1.27; P = 0.51). The median time to target temperature was 5.4 hours in the immediate angiography group and 4.7 hours in the delayed angiography group (ratio of geometric means, 1.19; 95% CI, 1.04 to 1.36). No significant differences between the groups were found in the remaining secondary end points.
Conclusions:
Among patients who had been successfully resuscitated after out-of-hospital cardiac arrest and had no signs of STEMI, a strategy of immediate angiography was not found to be better than a strategy of delayed angiography with respect to overall survival at 90 days. (Funded by the Netherlands Heart Institute and others; COACT Netherlands Trial Register number, NTR4973.).
More Related Videos
 06:25
Author Spotlight: Innovative Technique for Coronary Angiography in Marginal Donors
Published on: July 12, 2024
 18:11
A Research Method For Detecting Transient Myocardial Ischemia In Patients With Suspected Acute Coronary Syndrome Using Continuous ST-segment Analysis
Published on: December 28, 2012
Related Concept Videos
 03:12
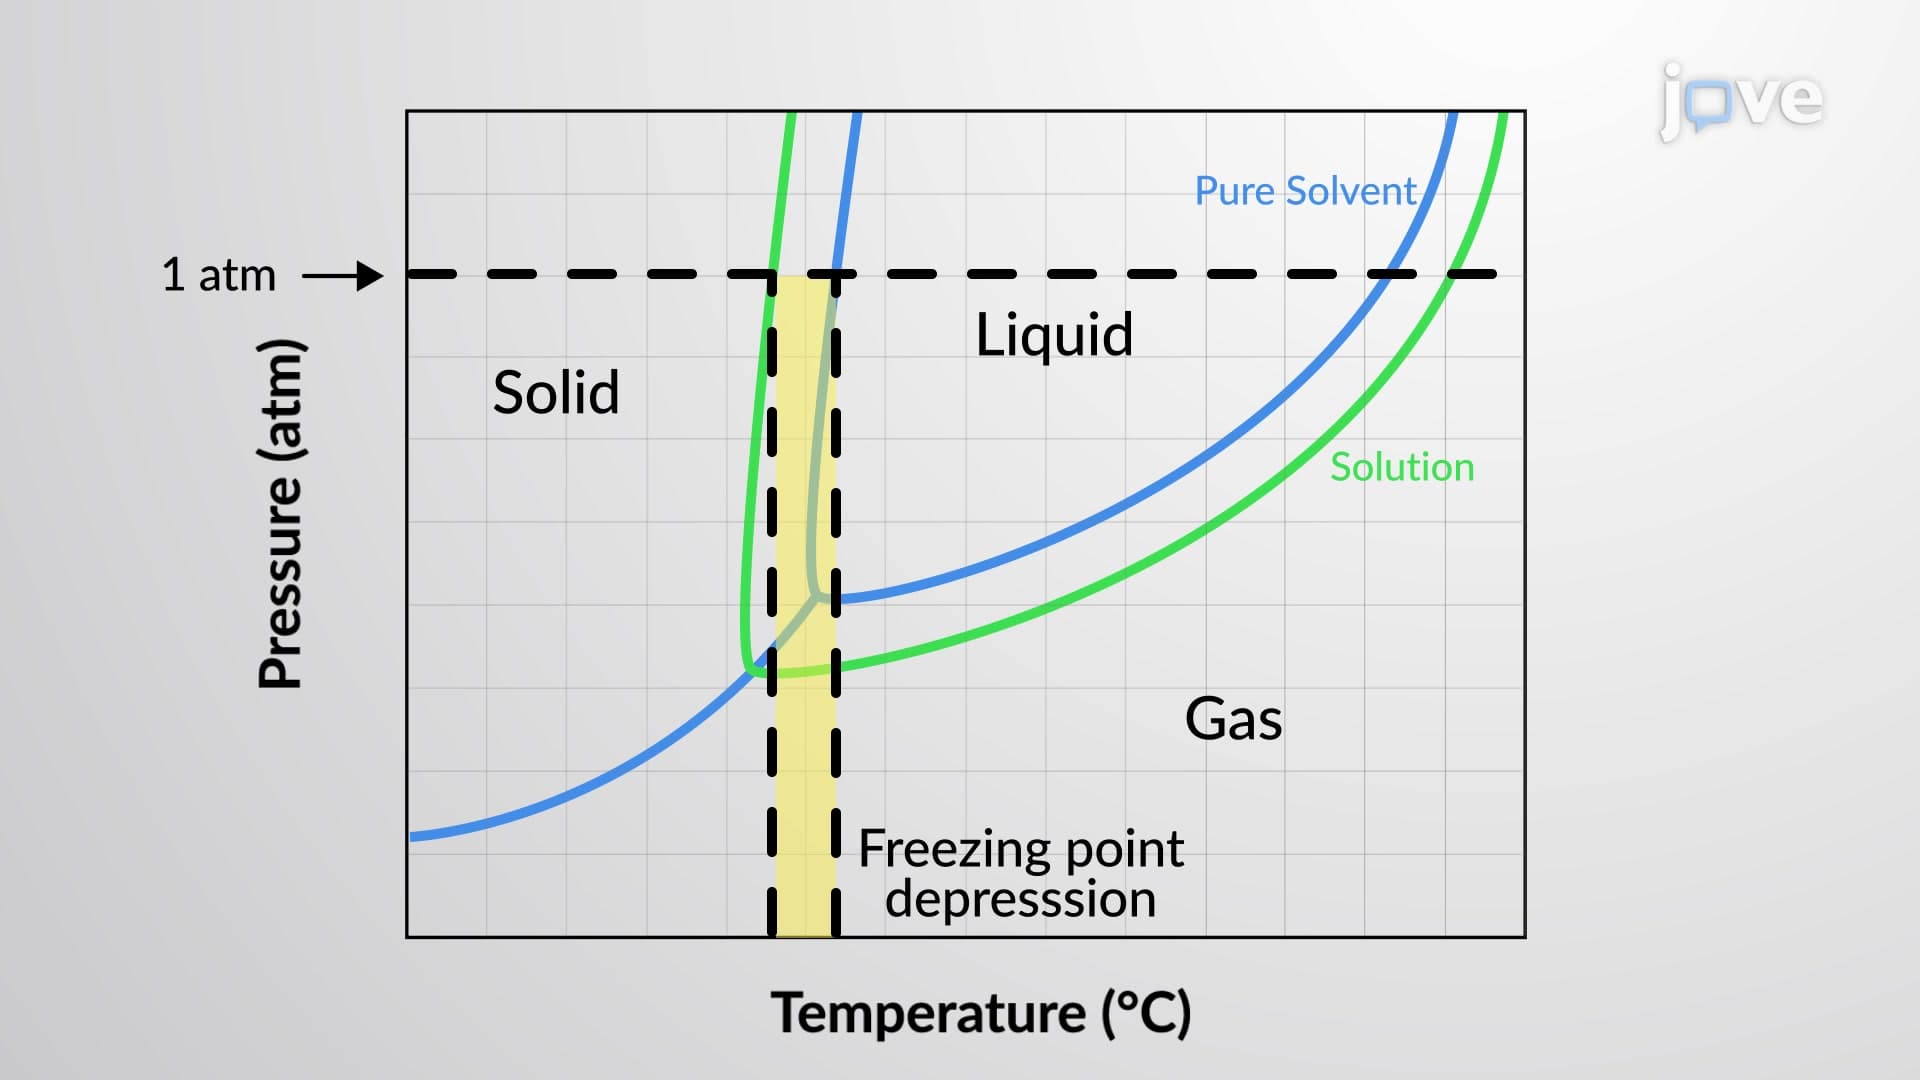
Freezing Point Depression and Boiling Point Elevation
The boiling point of a liquid is the temperature at which its vapor pressure is equal to ambient atmospheric pressure. Since the vapor pressure of a solution is lowered due to the presence of nonvolatile solutes, it stands to reason that the solution’s boiling point will subsequently be increased. Vapor pressure increases with temperature, and so a solution will require a higher temperature than will pure solvent to achieve any given vapor pressure, including one...
 01:20
Elevation of Intermediate Points on Vertical Curves
 01:21
Coronary Circulation
Coronary circulation begins at the base of the aorta, where two main arteries arise—the left and right coronary arteries. These arteries encircle the heart in the coronary sulcus and supply the...
 01:30
Coronary Artery Disease I: Introduction
 01:22
Cardiac Output II: Effect of Stroke Volume on Cardiac Output
Preload
Preload refers to the initial elongation of the cardiac myocytes before contraction and is related to the volume of blood filling the heart at the end of diastole, or end-diastolic volume. The...
 01:19
Cardiac Output I:Effect of Heart Rate on Cardiac Output
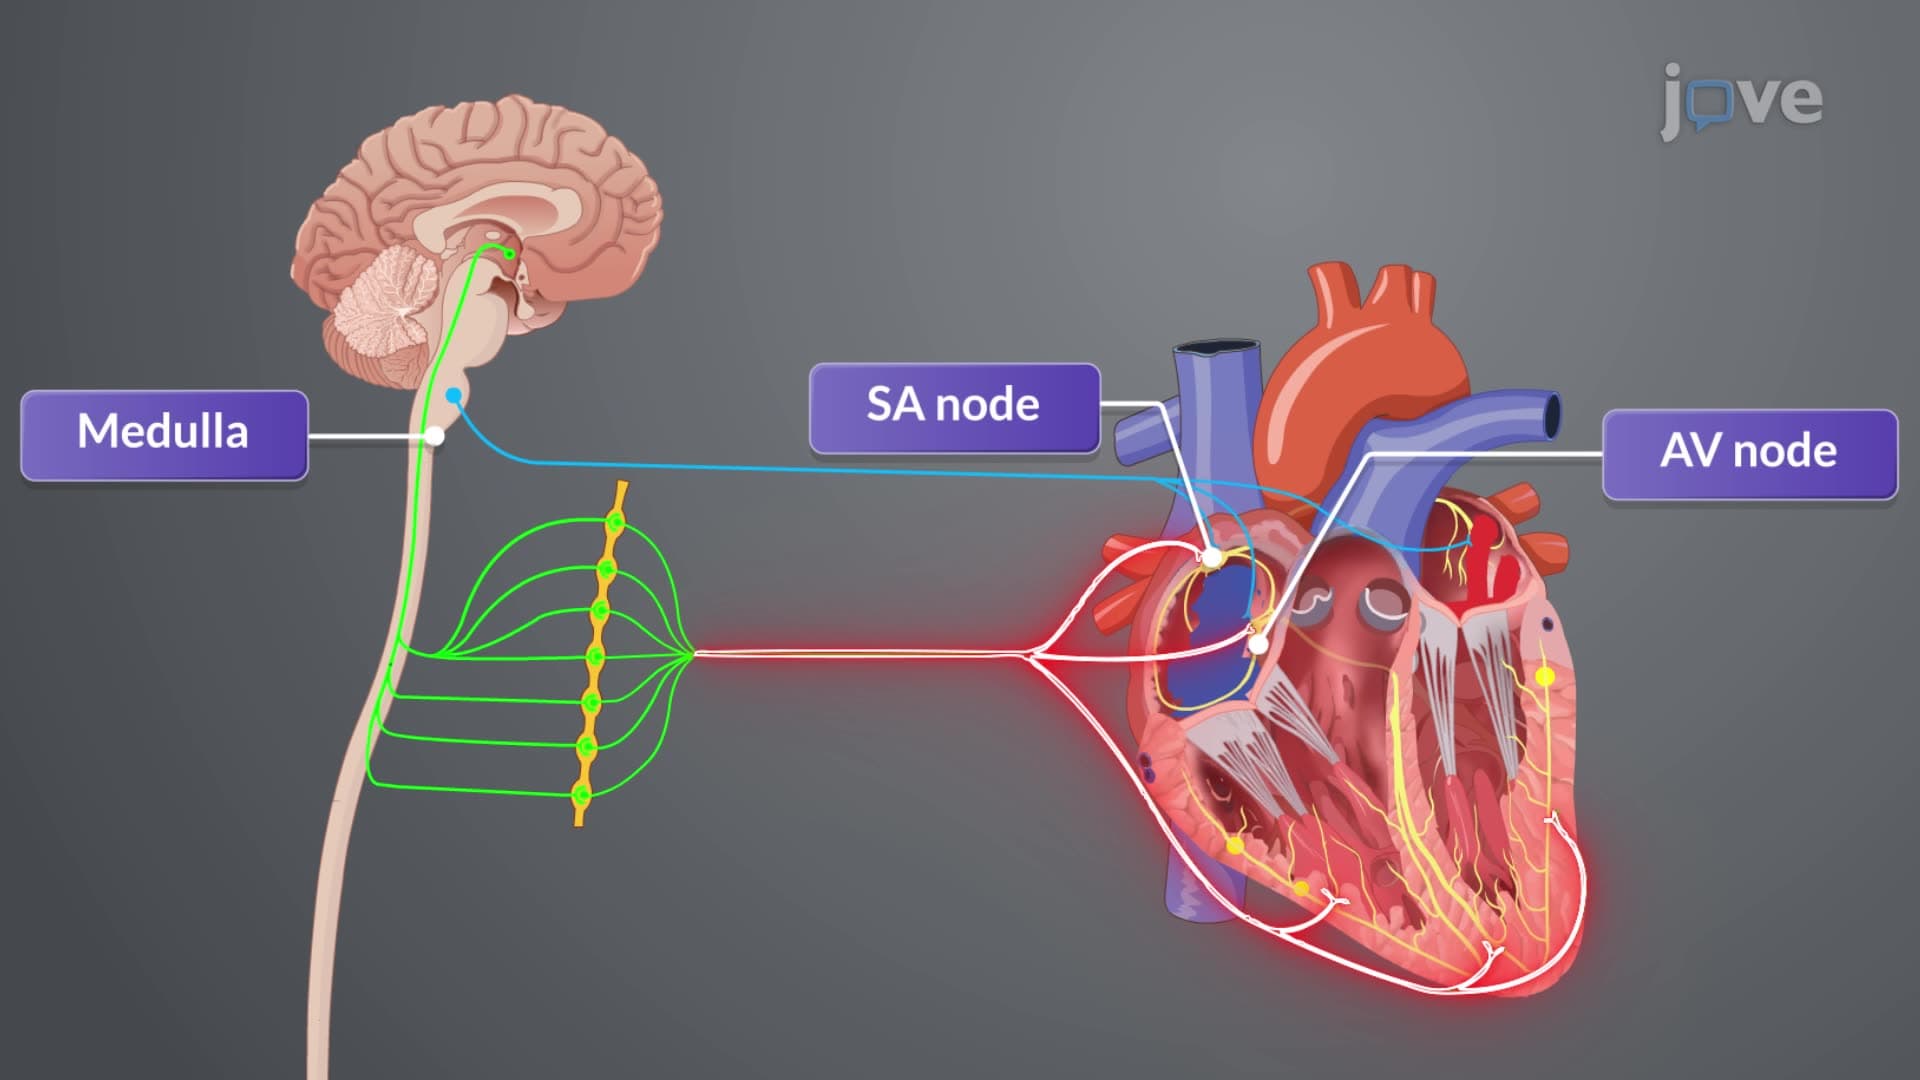
Cardiac output (CO) refers to the total amount of blood ejected by one of the ventricles in liters per minute (L/min). In a resting adult, CO ranges from 5 to 6 L/min, adjusting according to the body's metabolic requirements.
Effect of Heart Rate on Cardiac Output
Cardiac output adapts to metabolic demands during stress, physical activity, or illness. The autonomic nervous system regulates heart rate via the sinoatrial node. The parasympathetic nervous system decreases heart...