Related Experiment Video
Updated: Jan 27, 2026


Laparoscopic Repair of Para-Esophageal Hernia Using Absorbable Biosynthetic Mesh
Published on: September 11, 2021
Characterization of Esophageal Motility in Infants With Congenital Diaphragmatic Hernia Using High-resolution
Maissa Rayyan1,2, Taher Omari3, Anne Debeer1,2
1Neonatal Intensive Care Unit, University Hospitals Leuven, Leuven.

Objectives:
The aim of the study was to characterize esophageal motility and esophagogastric junction (EGJ) function in infants who underwent repair of an isolated congenital diaphragmatic hernia (iCDH).
Methods:
High-resolution manometry with impedance was used to investigate esophageal motility and EGJ function after diaphragmatic repair in 12 infants with iCDH (11 left-sided; 9 patch repair). They had esophageal motility studies during neonatal admission (n = 12), at 6 months (n = 10) and at 12 months of life (n = 7). Swallows were analyzed using conventional esophageal pressure topography and pressure flow analysis and were compared with 11 healthy preterm born infants at near-term age.
Results:
Esophageal peristaltic motor patterns in patients with iCDH were comparable to controls. EGJ end-expiratory pressure was higher in patients with patch repair compared with controls (P = 0.050) and those without patch (P = 0.009). The difference between inspiratory and expiratory pressures at the EGJ was lower in patients with iCDH with patch (P = 0.045) compared to patients without. Patients with iCDH with patch showed increased Pressure Flow Index, resistance of bolus flow at the EGJ, compared with controls (P = 0.043).
Conclusions:
Normal esophageal wave patterns are present in the investigated patients with iCDH. EGJ end-expiratory pressure seems lower in patients with iCDH without patch suggesting a decreased EGJ barrier function hence increased vulnerability to gastroesophageal reflux. Patch repair appears to increase end-expiratory pressure at the EGJ above that of controls suggesting that patch surgery tightens the EGJ, thereby increasing flow resistance. This is in line with the increased Pressure Flow Index. In infants with a patch, the inspiration-expiration pressure difference is lower, reflecting diminished activity of the crural diaphragm.


Related Concept Videos
 01:24
Esophageal Varices-I: Introduction
 01:22
Esophageal Perforation-I: Introduction
The location of esophageal perforation can vary, occurring anywhere along the esophagus....
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...
 01:16
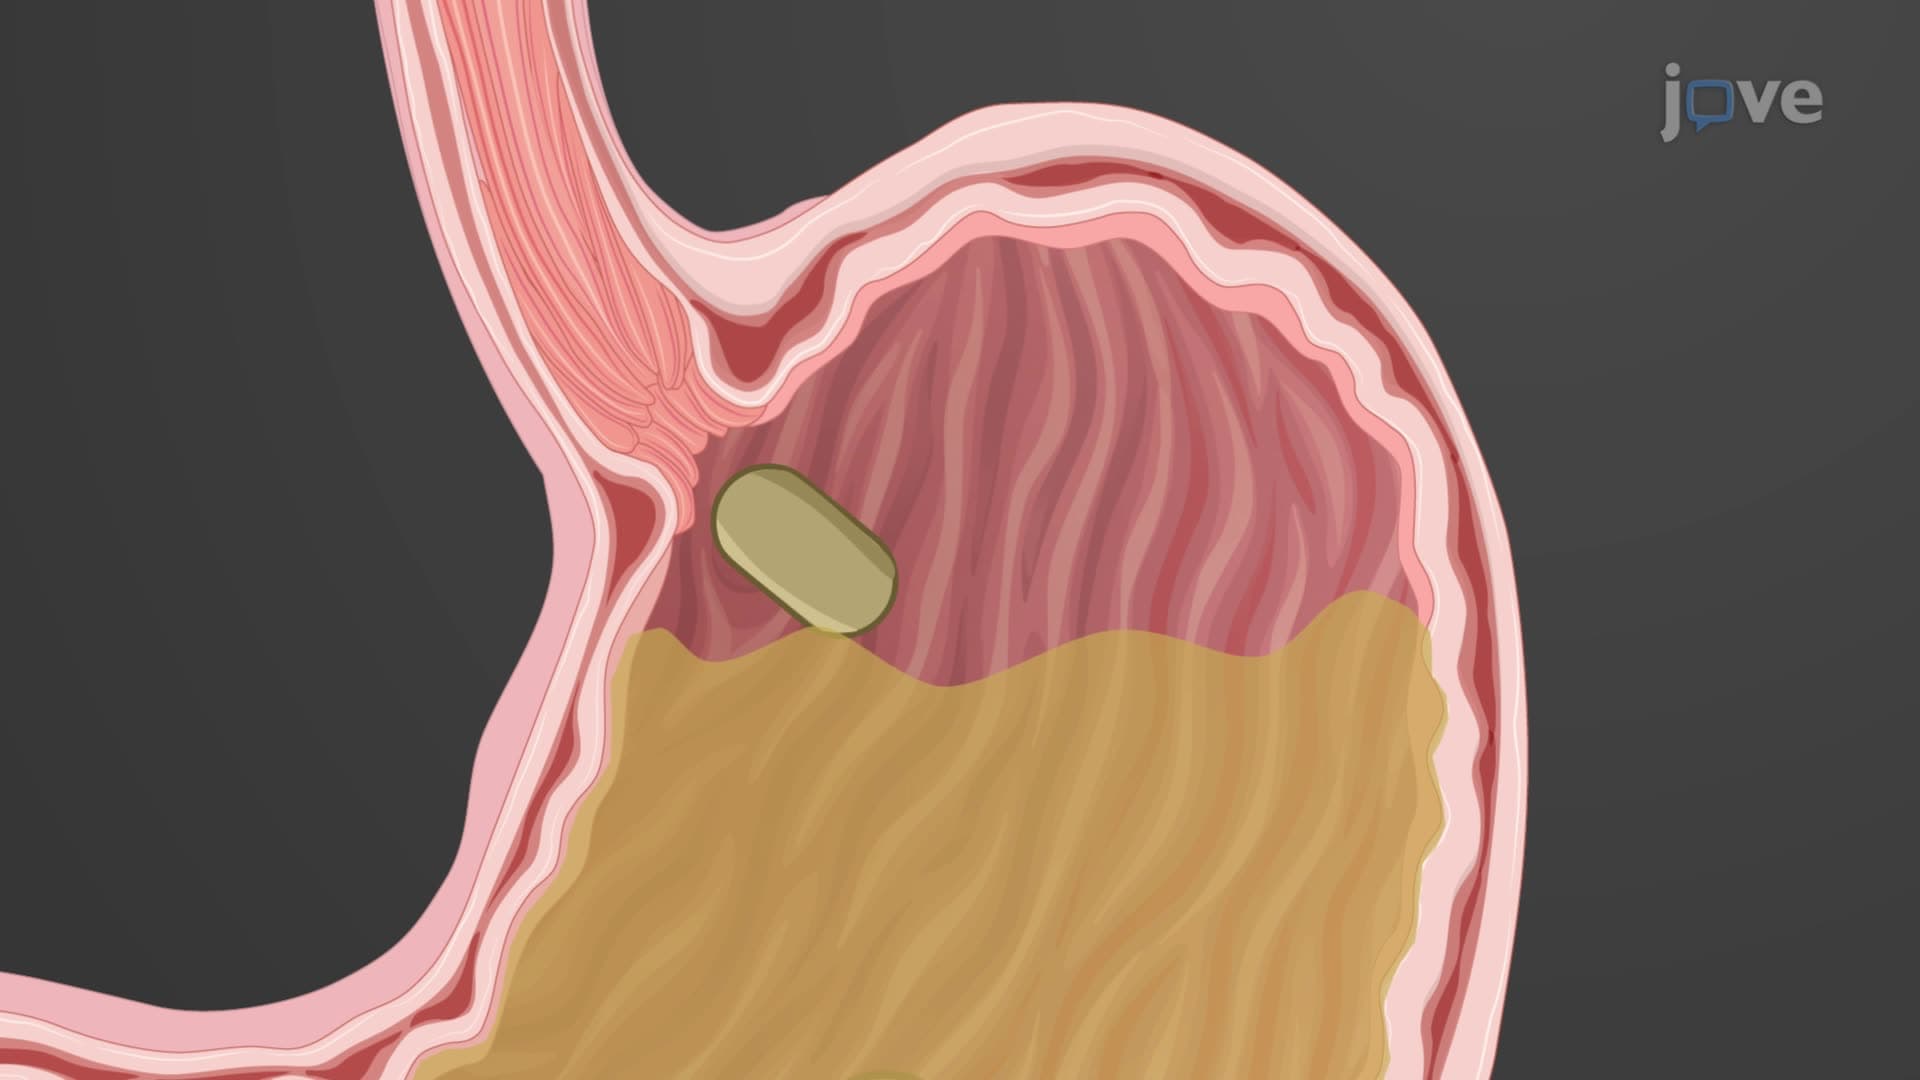
Gastric Motility
Peristaltic Waves and Chyme Formation
Upon food entry, the stomach initiates...
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:29
Drug Dosing: Infants and Children