Related Experiment Video
Updated: Nov 26, 2025
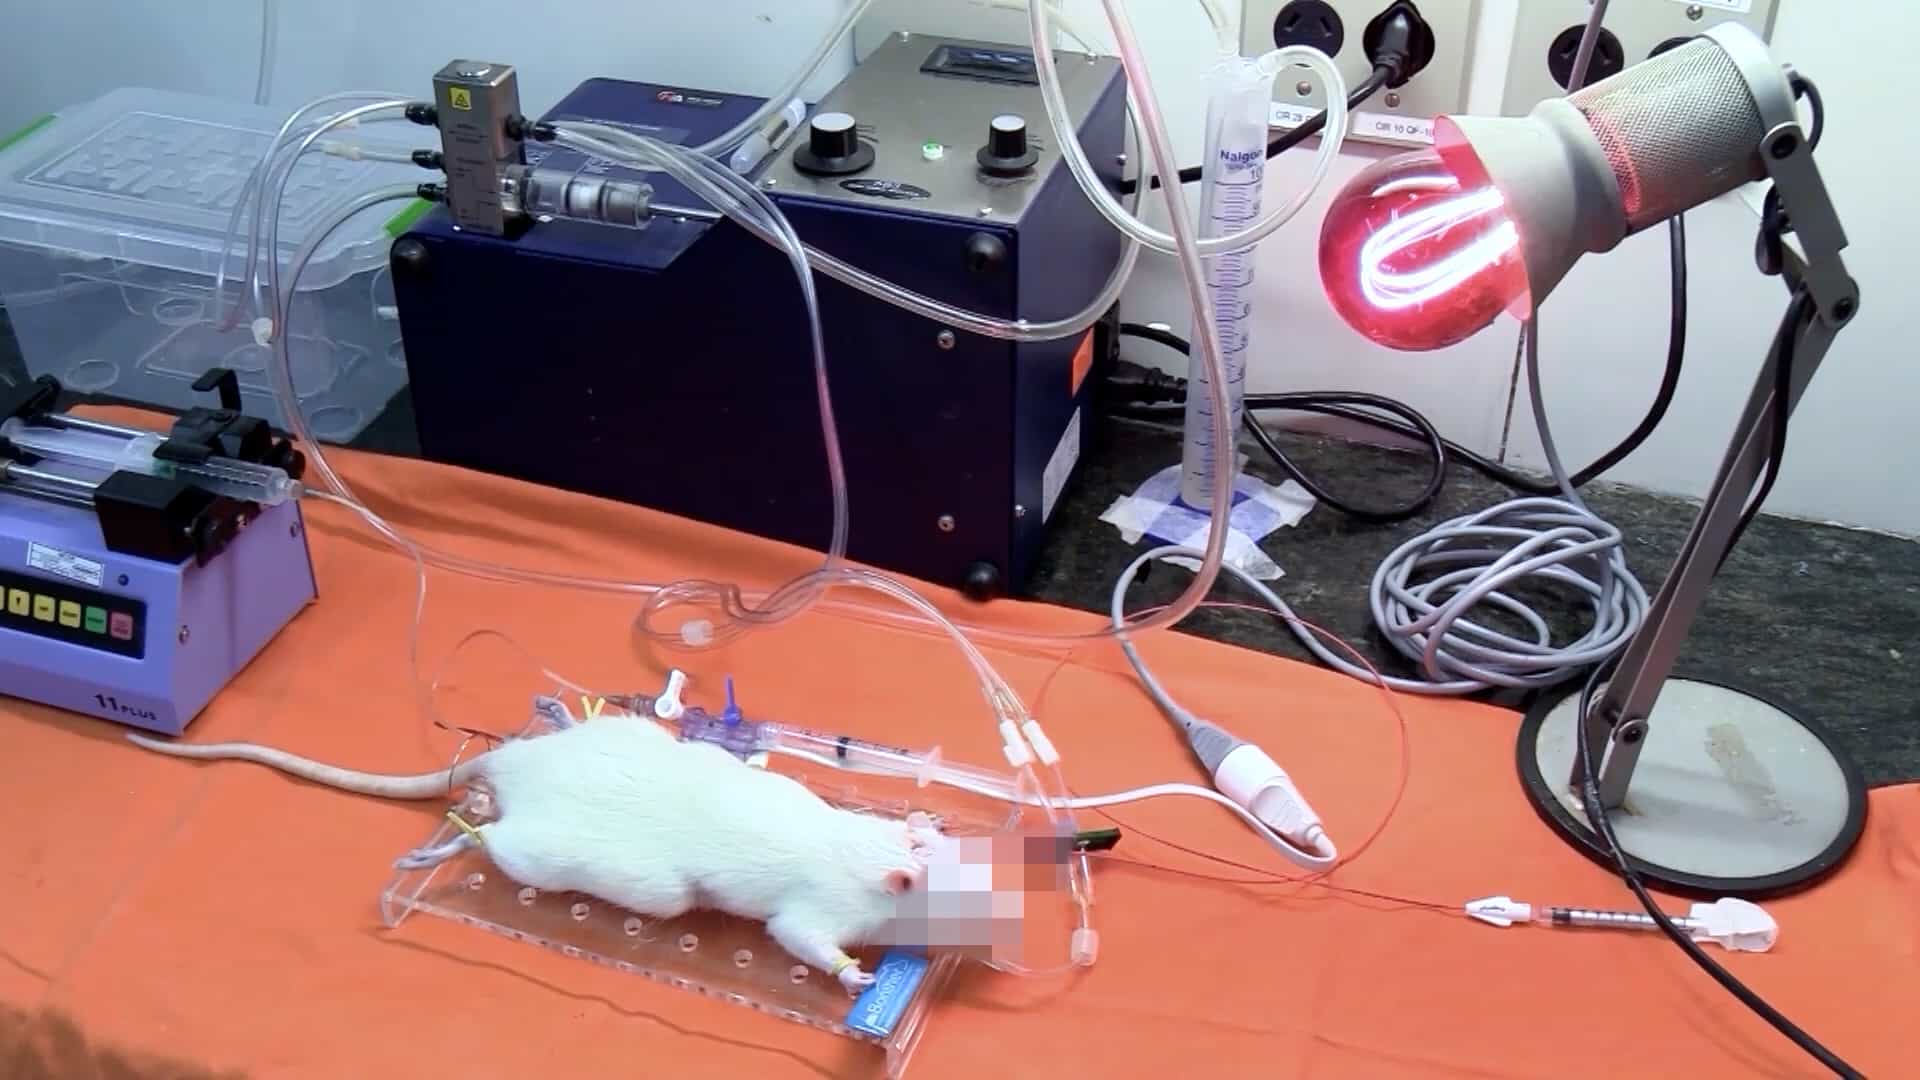

Study of Experimental Organ Donation Models for Lung Transplantation
Published on: March 15, 2024
Clinical Determination of Brain Death in Children Supported by Extracorporeal Membrane Oxygenation
Dana B Harrar1,2, Vinay Kukreti3,4, Nathan P Dean3
1Division of Neurology, Children's National Medical Center, 111 Michigan Avenue NW, Washington, DC, 20010, USA. dharrar@childrensnational.org.

Insights
Determining brain death in children on extracorporeal membrane oxygenation (ECMO) is possible. Modifying the ECMO circuit allows for safe apnea testing, aiding in clinical brain death determination for pediatric patients.
Area of Science:
- Pediatric critical care medicine
- Neurology
- Cardiopulmonary support
Background:
- Children on extracorporeal membrane oxygenation (ECMO) face risks of severe neurological injury, including brain death.
- Establishing brain death in these patients is crucial for families, resource management, and organ donation.
- Previous reports on clinical brain death determination in pediatric ECMO patients are scarce, particularly regarding apnea testing.
Purpose of the Study:
- To evaluate the feasibility and safety of clinical brain death determination, including apnea testing, in pediatric patients supported by veno-arterial ECMO (VA-ECMO).
- To describe modifications to the VA-ECMO circuit during apnea testing to maintain hemodynamic stability and achieve adequate hypercarbia.
Main Methods:
- Retrospective review of medical records for pediatric patients undergoing brain death examinations while on VA-ECMO from 2010 to 2018.
- Analysis of 14 brain death examinations, including apnea tests, in eight pediatric patients.
- Detailed examination of VA-ECMO circuit modifications employed during apnea testing.
Main Results:
- Six out of eight pediatric patients met clinical criteria for brain death after undergoing apnea testing on VA-ECMO.
- Apnea testing was successfully performed in 13 out of 14 examinations.
- Modifications such as decreased sweep flow, addition of carbon dioxide, and increased pump flow were used to maintain oxygenation and hemodynamic stability.
Conclusions:
- Clinical brain death determination, including apnea testing, is achievable in pediatric patients supported by VA-ECMO.
- The VA-ECMO circuit can be safely modified to facilitate apnea testing, ensuring adequate carbon dioxide levels and hemodynamic stability.
Background/Objective:
Children supported by extracorporeal membrane oxygenation (ECMO) are at risk of catastrophic neurologic injury and brain death. Timely determination of brain death is important for minimizing psychological distress for families, resource allocation, and organ donation. Reports of successful determination of brain death in pediatric patients supported by ECMO are limited. The determination of brain death by clinical criteria requires apnea testing, which has historically been viewed as challenging in patients supported by ECMO. We report eight pediatric patients who underwent a total of 14 brain death examinations, including apnea testing, while supported by veno-arterial ECMO (VA-ECMO), resulting in six cases of clinical determination of brain death.
Methods:
We performed a retrospective review of the medical records of pediatric patients who underwent brain death examination while supported by VA-ECMO between 2010 and 2018 at a single tertiary care children's hospital.
Results:
Eight patients underwent brain death examination, including apnea testing, while supported by VA-ECMO. Six patients met criteria for brain death, while two had withdrawal of technical support after the first examination. During the majority of apnea tests (n = 13/14), the ECMO circuit was modified to achieve hypercarbia while maintaining oxygenation and hemodynamic stability. The sweep flow was decreased prior to apnea testing in ten brain death examinations, carbon dioxide was added to the circuit during three examinations, and ECMO pump flows were increased in response to hypotension during two examinations.
Conclusions:
Clinical determination of brain death, including apnea testing, can be performed in pediatric patients supported by ECMO. The ECMO circuit can be effectively modified during apnea testing to achieve a timely rise in carbon dioxide while maintaining oxygenation and hemodynamic stability.

