Related Experiment Video
Updated: Jan 27, 2026

TBase - an Integrated Electronic Health Record and Research Database for Kidney Transplant Recipients
Published on: April 13, 2021
Electronically delivered interventions to reduce antibiotic prescribing for respiratory infections in primary care:
Martin C Gulliford1,2, Dorota Juszczyk1,2, A Toby Prevost1,2,3
1School of Population Health and Environmental Sciences, King's College London, London, UK.

Background:
Unnecessary prescribing of antibiotics in primary care is contributing to the emergence of antimicrobial drug resistance.
Objectives:
To develop and evaluate a multicomponent intervention for antimicrobial stewardship in primary care, and to evaluate the safety of reducing antibiotic prescribing for self-limiting respiratory infections (RTIs).
Interventions:
A multicomponent intervention, developed as part of this study, including a webinar, monthly reports of general practice-specific data for antibiotic prescribing and decision support tools to inform appropriate antibiotic prescribing.
Design:
A parallel-group, cluster randomised controlled trial.
Setting:
The trial was conducted in 79 general practices in the UK Clinical Practice Research Datalink (CPRD).
Participants:
All registered patients were included.
Main Outcome Measures:
The primary outcome was the rate of antibiotic prescriptions for self-limiting RTIs over the 12-month intervention period.
Cohort Study:
A separate population-based cohort study was conducted in 610 CPRD general practices that were not exposed to the trial interventions. Data were analysed to evaluate safety outcomes for registered patients with 45.5 million person-years of follow-up from 2005 to 2014.
Results:
There were 41 intervention trial arm practices (323,155 patient-years) and 38 control trial arm practices (259,520 patient-years). There were 98.7 antibiotic prescriptions for RTIs per 1000 patient-years in the intervention trial arm (31,907 antibiotic prescriptions) and 107.6 per 1000 patient-years in the control arm (27,923 antibiotic prescriptions) [adjusted antibiotic-prescribing rate ratio (RR) 0.88, 95% confidence interval (CI) 0.78 to 0.99; p = 0.040]. There was no evidence of effect in children aged < 15 years (RR 0.96, 95% CI 0.82 to 1.12) or adults aged ≥ 85 years (RR 0.97, 95% CI 0.79 to 1.18). Antibiotic prescribing was reduced in adults aged between 15 and 84 years (RR 0.84, 95% CI 0.75 to 0.95), that is, one antibiotic prescription was avoided for every 62 patients (95% CI 40 to 200 patients) aged 15-84 years per year. Analysis of trial data for 12 safety outcomes, including pneumonia and peritonsillar abscess, showed no evidence that these outcomes might be increased as a result of the intervention. The analysis of data from non-trial practices showed that if a general practice with an average list size of 7000 patients reduces the proportion of RTI consultations with antibiotics prescribed by 10%, then 1.1 (95% CI 0.6 to 1.5) more cases of pneumonia per year and 0.9 (95% CI 0.5 to 1.3) more cases of peritonsillar abscesses per decade may be observed. There was no evidence that mastoiditis, empyema, meningitis, intracranial abscess or Lemierre syndrome were more frequent at low-prescribing practices.
Limitations:
The research was based on electronic health records that may not always provide complete data. The number of practices included in the trial was smaller than initially intended.
Conclusions:
This study found evidence that, overall, general practice antibiotic prescribing for RTIs was reduced by this electronically delivered intervention. Antibiotic prescribing rates were reduced for adults aged 15-84 years, but not for children or the senior elderly.
Future Work:
Strategies for antimicrobial stewardship should employ stratified interventions that are tailored to specific age groups. Further research into the safety of reduced antibiotic prescribing is also needed.
Trial Registration:
Current Controlled Trials ISRCTN95232781.
Funding:
This project was funded by the National Institute for Health Research (NIHR) Health Technology Assessment programme and will be published in full in Health Technology Assessment; Vol. 23, No. 11. See the NIHR Journals Library website for further project information.
More Related Videos
 07:31
Implementation of a Real-Time Psychosis Risk Detection and Alerting System Based on Electronic Health Records using CogStack
Published on: May 15, 2020
 07:00
Preparing Lamellae from Vitreous Biological Samples Using a Dual-Beam Scanning Electron Microscope for Cryo-Electron Tomography
Published on: August 5, 2021
Related Concept Videos
 01:28
Electron Transport Chains
The ETC is comprised of...
 03:07
Electron Affinity
 01:24
Electron Carriers
Over the many stages of cellular respiration, glucose breaks down into carbon dioxide and water. Electron carriers pick up electrons lost by glucose in these reactions, temporarily storing and releasing them into the electron...
 00:54
Electron Behavior
Electrons are negatively charged subatomic particles that are attracted to an orbit around the positively-charged nucleus of an atom. They reside in locations that are associated with energy levels called shells and are further organized into sub-shells and orbitals within each shell.
Electrons Orbit the Nucleus
Electrons are found in specific locations outside of the nucleus. The shell in which an electron resides indicates the general energy level of the electron: those closer to the...
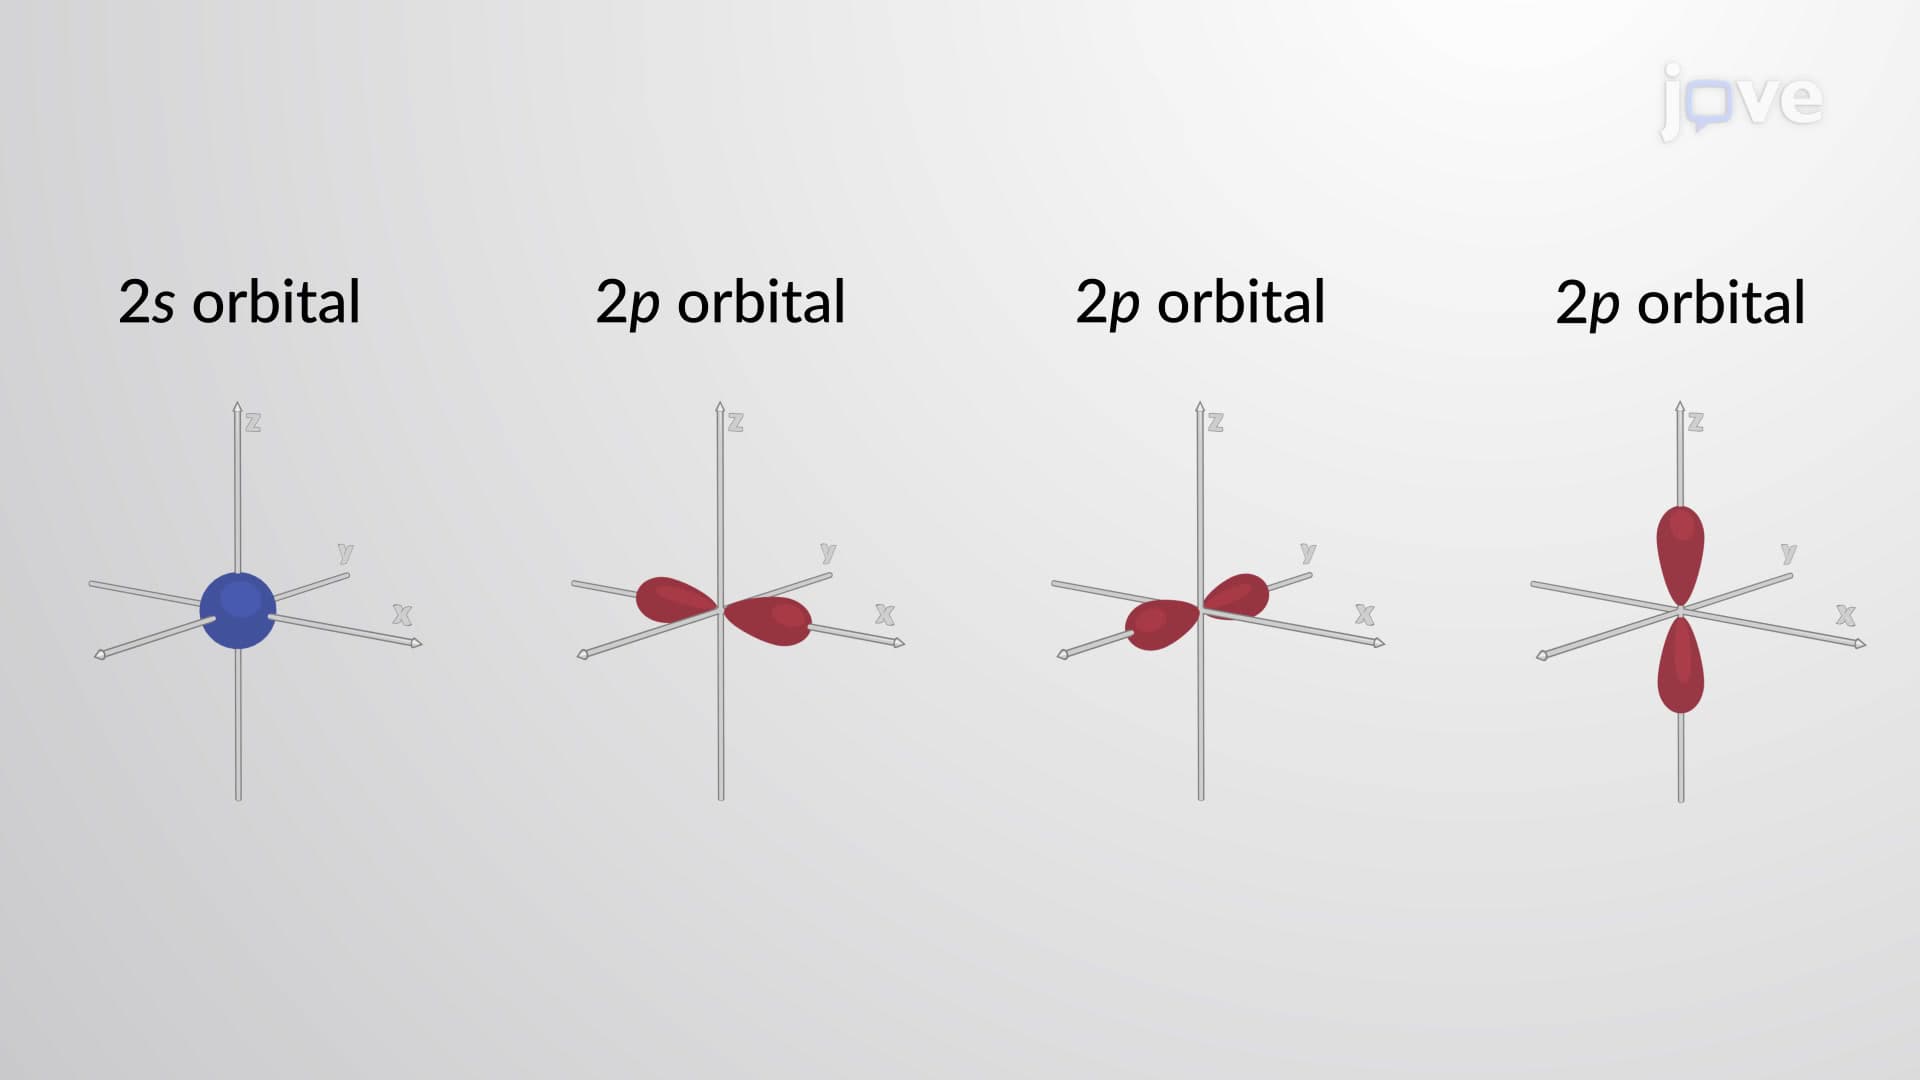 01:18
Electron Orbital Model
The first shell is closest to the nucleus, and it has only one subshell with a single spherical orbital called the...
 03:26
Electron Configuration of Multielectron Atoms