Related Experiment Video
Updated: Jan 27, 2026


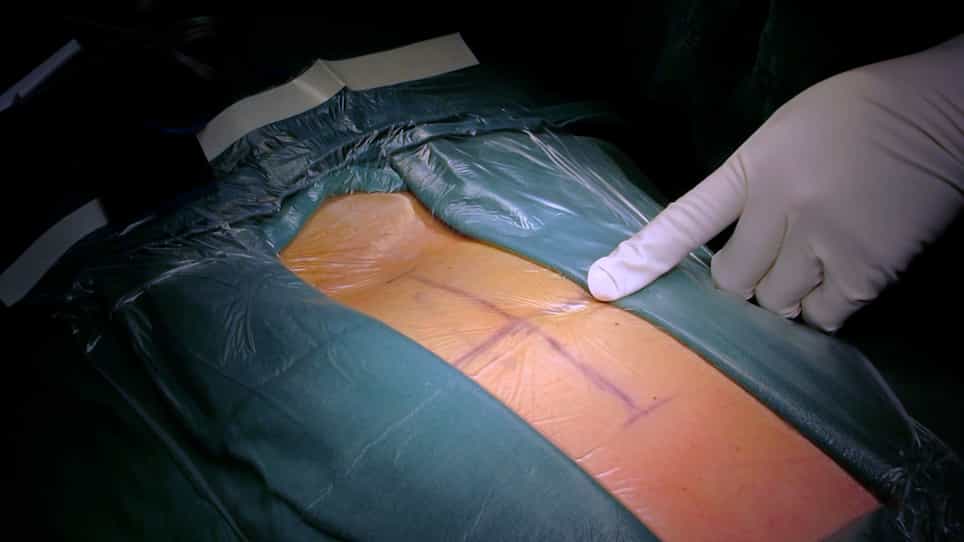
Minimally Invasive Treatment for Thoracolumbar Burst Fracture Using Sagittal Alignment Screws and A Trauma Reduction Device
Published on: November 8, 2024
Comparison of Two Segment Combined Instrumentation and Fusion versus Three Segment Posterior Instrumentation in
Gurkan Gumussuyu1, Nazir Cihangir Islam, Ozkan Kose
1Istinye University, School of Medicine, Department of Orthopaedics and Traumatology, Bahcelievler Medicalpark Hospital, Istanbul,Turkey.

Aim:
To compare the clinical and functional outcomes between combined anterior and posterior 2-segment spinal fusion and posterior 3-segment spinal fusion in patients with thoracolumbar (TL) burst fractures at risk for posttraumatic kyphosis without neurological deficit.
Material And Methods:
Twenty-seven patients with TL burst fracture, > 20° kyphosis and/or 50% collapse, and posterior ligament injury, but without neurological deficit, were randomly assigned into posterior and combined groups. Posterior treatment was 3-segment (1 level below, fractured level and 2 levels above) posterior spinal fusion. Combined treatment was including 1 cranial and 1 caudal levels posterior spinal fusion, followed by anterior corpectomy, cage, and bone grafting. Patients were followed-up for a mean duration of 117.7 ± 8.7 months (range, 98-132 months). At the final follow-up, the clinical and functional means of the groups were compared using degree of kyphosis, visual analogue scale (VAS), and Roland-Morris and Oswestry scores.
Results:
Mean patient age was 38.5 ± 2.4 years (range: 18-68 years). Fourteen and 13 patients were treated with the combined and posterior approach, respectively. Age (40.0 ± 10.3 and 37.0 ± 14.2 years; p=0.519), sex (female/male, 3:10 and 5:9; p=0.385), mechanism of injury (p=0.513), fractured levels (p=0.185), type of fracture (p=0.293), degree of kyphosis at initial admission (p=0.616), collapse (p=0.155), canal narrowing (p=0.280), follow-up (p=0.076) and accompanied limb fracture (p=0.374) were similar between groups. Duration of hospital stay was similar between two groups (p=0.102). However, blood loss was higher in combined group (195 ml versus 358ml, p=0.003). A 14.2° correction was achieved in the posterior group and 16.9° in the combined group (p=0.61). Loss of correction at the last follow-up visit was 2.1° with a final kyphosis of 7.2° in the posterior group, and 1.2° with a final kyphosis of 5.5° in the combined group. The differences in the correction of kyphosis (p=0.616), postop kyphosis (p=0.756), loss of correction (p=0.141) and final kyphosis (p=0.085) between the treatment groups were not significant. At the last follow-up visit of the posterior and combined groups, the VAS (16.4 ± 14.8 vs. 17.6 ± 16.6; p=0.685), Roland-Morris (27.2 ± 27.3 vs. 29.6 ± 20.5; p=0.519), and Oswestry scores (15.0 ± 13.1 vs. 17.7 ± 11.5; p=0.302) were similar.
Conclusion:
Both treatment methods are similar in terms of clinical and functional outcomes.

Related Concept Videos
 01:23
Instrument Transformers
 01:12
Instrument Calibration
Analytical Balance Calibration
An analytical balance measures mass and requires regular calibration to...
 01:25
Instrumentation Amplifier
To overcome this challenge, an ECG machine utilizes an instrumentation amplifier. This specialized amplifier is...
 02:46
Uncertainty in Measurement: Reading Instruments
 01:20
Capillary Electrophoresis: Instrumentation
 01:25
Fluorescence and Phosphorescence: Instrumentation