Related Experiment Video
Updated: Jan 27, 2026
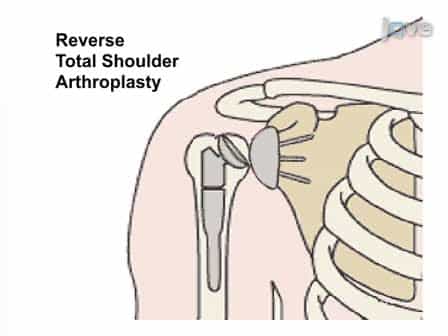
Reverse Total Shoulder Arthroplasty
Published on: July 5, 2011
Smoking Dependent Alterations in Bone Formation and Inflammation Represent Major Risk Factors for Complications
Sabrina Ehnert1, Romina H Aspera-Werz2, Christoph Ihle3
1Department of Trauma and Reconstructive Surgery, Siegfried Weller Research Institute, Eberhard Karls University Tuebingen, BG Trauma Center Tuebingen, 72076 Tuebingen, Germany. sabrina.ehnert@med.uni-tuebingen.de.

Abstract:
Numerous studies have described a correlation between smoking and reduced bone mass. This not only increases fracture risk but also impedes reconstruction/fixation of bone. An increased frequency of complications following surgery is common. Here, we investigate the effect of smoking on the clinical outcome following total joint arthroplasty (TJA). 817 patients receiving primary or revision (including clinical transfers) TJA at our level-one trauma center have been randomly interviewed twice (pre- and six months post-surgery). We found that 159 patients developed complications (infections, disturbed healing, revisions, thrombosis, and/or death). Considering nutritional status, alcohol and cigarette consumption as possible risk factors, OR was highest for smoking. Notably, mean age was significantly lower in smokers (59.2 ± 1.0a) than non-smokers (64.6 ± 0.8; p < 0.001). However, the number of comorbidities was comparable between both groups. Compared to non-smokers (17.8 ± 1.9%), the complication rate increases with increasing cigarette consumption (1⁻20 pack-years (PY): 19.2 ± 2.4% and >20 PY: 30.4 ± 3.6%; p = 0.002). Consequently, mean hospital stay was longer in heavy smokers (18.4 ± 1.0 day) than non-smokers (15.3 ± 0.5 day; p = 0.009) or moderate smokers (15.9 ± 0.6 day). In line with delayed healing, bone formation markers (BAP and CICP) were significantly lower in smokers than non-smokers 2 days following TJA. Although, smoking increased serum levels of MCP-1, OPG, sRANKL, and Osteopontin as well as bone resorption markers (TRAP5b and CTX-I) were unaffected. In line with an increased infection rate, smoking reduced 25OH vitamin D3 (immune-modulatory), IL-1β, IL-6, TNF-α, and IFN-γ serum levels. Our data clearly show that smoking not only affects bone formation after TJA but also suppresses the inflammatory response in these patients. Thus, it is feasible that therapies favoring bone formation and immune responses help improve the clinical outcome in smokers following TJA.
Related Concept Videos
 01:26
Factors Affecting the Risk of Infection
The integrity and count of the white blood cells help the body resist pathogens and fight infection. When impaired, it reduces the body's resistance to pathogens. The acidic pH levels of the gastrointestinal, genitourinary tracts, and skin...
 01:38
Inflammation
 02:13
The Representativeness Heuristic
 01:24
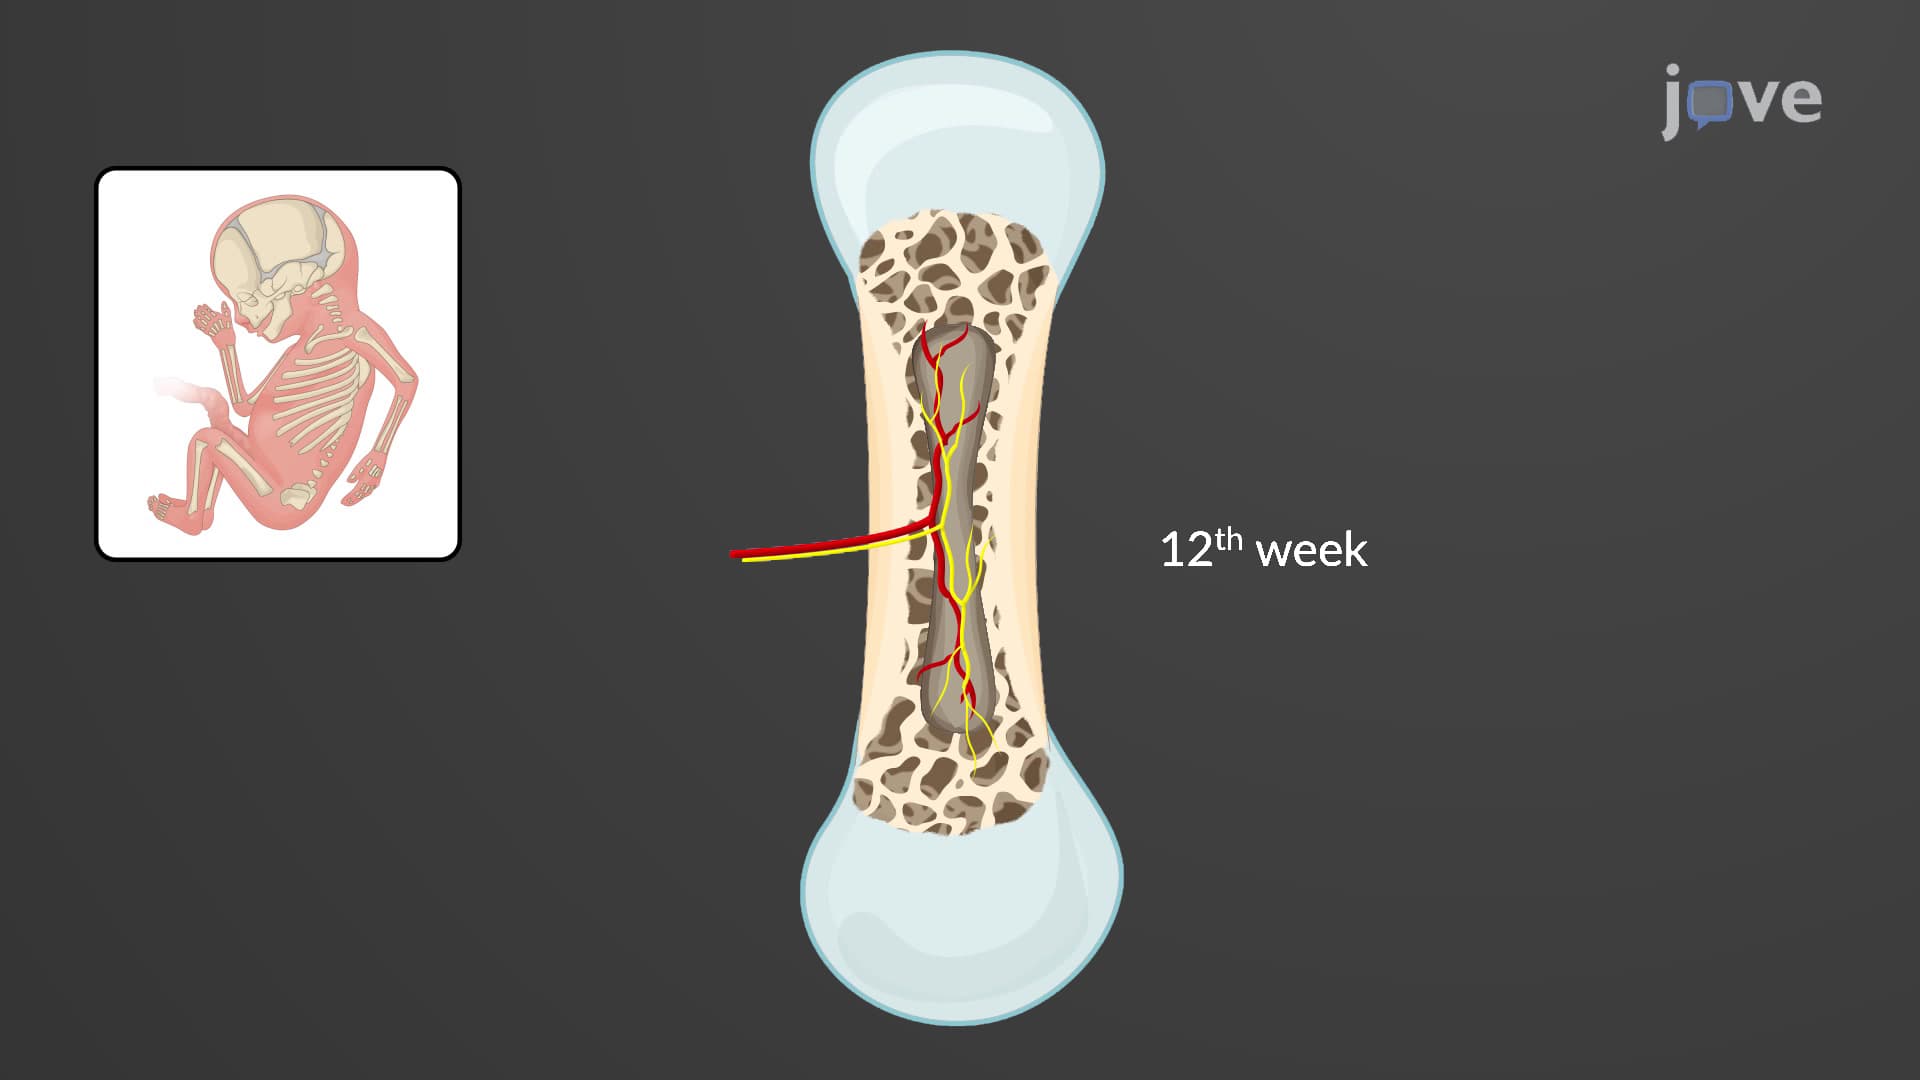
Bone Formation by Endochondral Ossification
 01:29
Bone Formation by Intramembranous Ossification
The process begins when mesenchymal cells in the embryonic skeleton gather together and differentiate into osteogenic cells, which then develop into ...
 02:16
Solution Formation
This selective...