Related Experiment Video
Updated: Jan 27, 2026

A Protocol for Explant Cultures of IDH1-mutant Diffuse Low-grade Gliomas
Published on: May 9, 2025
Cost-effectiveness of Intraoperative MRI for Treatment of High-Grade Gliomas
Peter Abraham1, Reith Sarkar1, Michael G Brandel1
1From the School of Medicine (P.A., R.S., M.G.B., C.L.R., J.P.), Department of Neurosurgery (A.R.W., R.C.R., J.A.S., D.R.S.D., V.C., J.S.P., A.A.K.), and Department of Radiation Oncology (J.D.M.), University of California-San Diego, 9300 Campus Point Dr, Mail Code 7893, La Jolla, CA 92037.

Abstract:
Background Intraoperative MRI has been shown to improve gross-total resection of high-grade glioma. However, to the knowledge of the authors, the cost-effectiveness of intraoperative MRI has not been established. Purpose To construct a clinical decision analysis model for assessing intraoperative MRI in the treatment of high-grade glioma. Materials and Methods An integrated five-state microsimulation model was constructed to follow patients with high-grade glioma. One-hundred-thousand patients treated with intraoperative MRI were compared with 100 000 patients who were treated without intraoperative MRI from initial resection and debulking until death (median age at initial resection, 55 years). After the operation and treatment of complications, patients existed in one of three health states: progression-free survival (PFS), progressive disease, or dead. Patients with recurrence were offered up to two repeated resections. PFS, valuation of health states (utility values), probabilities, and costs were obtained from randomized controlled trials whenever possible. Otherwise, national databases, registries, and nonrandomized trials were used. Uncertainty in model inputs was assessed by using deterministic and probabilistic sensitivity analyses. A health care perspective was used for this analysis. A willingness-to-pay threshold of $100 000 per quality-adjusted life year (QALY) gained was used to determine cost efficacy. Results Intraoperative MRI yielded an incremental benefit of 0.18 QALYs (1.34 QALYs with intraoperative MRI vs 1.16 QALYs without) at an incremental cost of $13 447 ($176 460 with intraoperative MRI vs $163 013 without) in microsimulation modeling, resulting in an incremental cost-effectiveness ratio of $76 442 per QALY. Because of parameter distributions, probabilistic sensitivity analysis demonstrated that intraoperative MRI had a 99.5% chance of cost-effectiveness at a willingness-to-pay threshold of $100 000 per QALY. Conclusion Intraoperative MRI is likely to be a cost-effective modality in the treatment of high-grade glioma. © RSNA, 2019 Online supplemental material is available for this article. See also the editorial by Bettmann in this issue.
More Related Videos


Related Concept Videos
 01:19
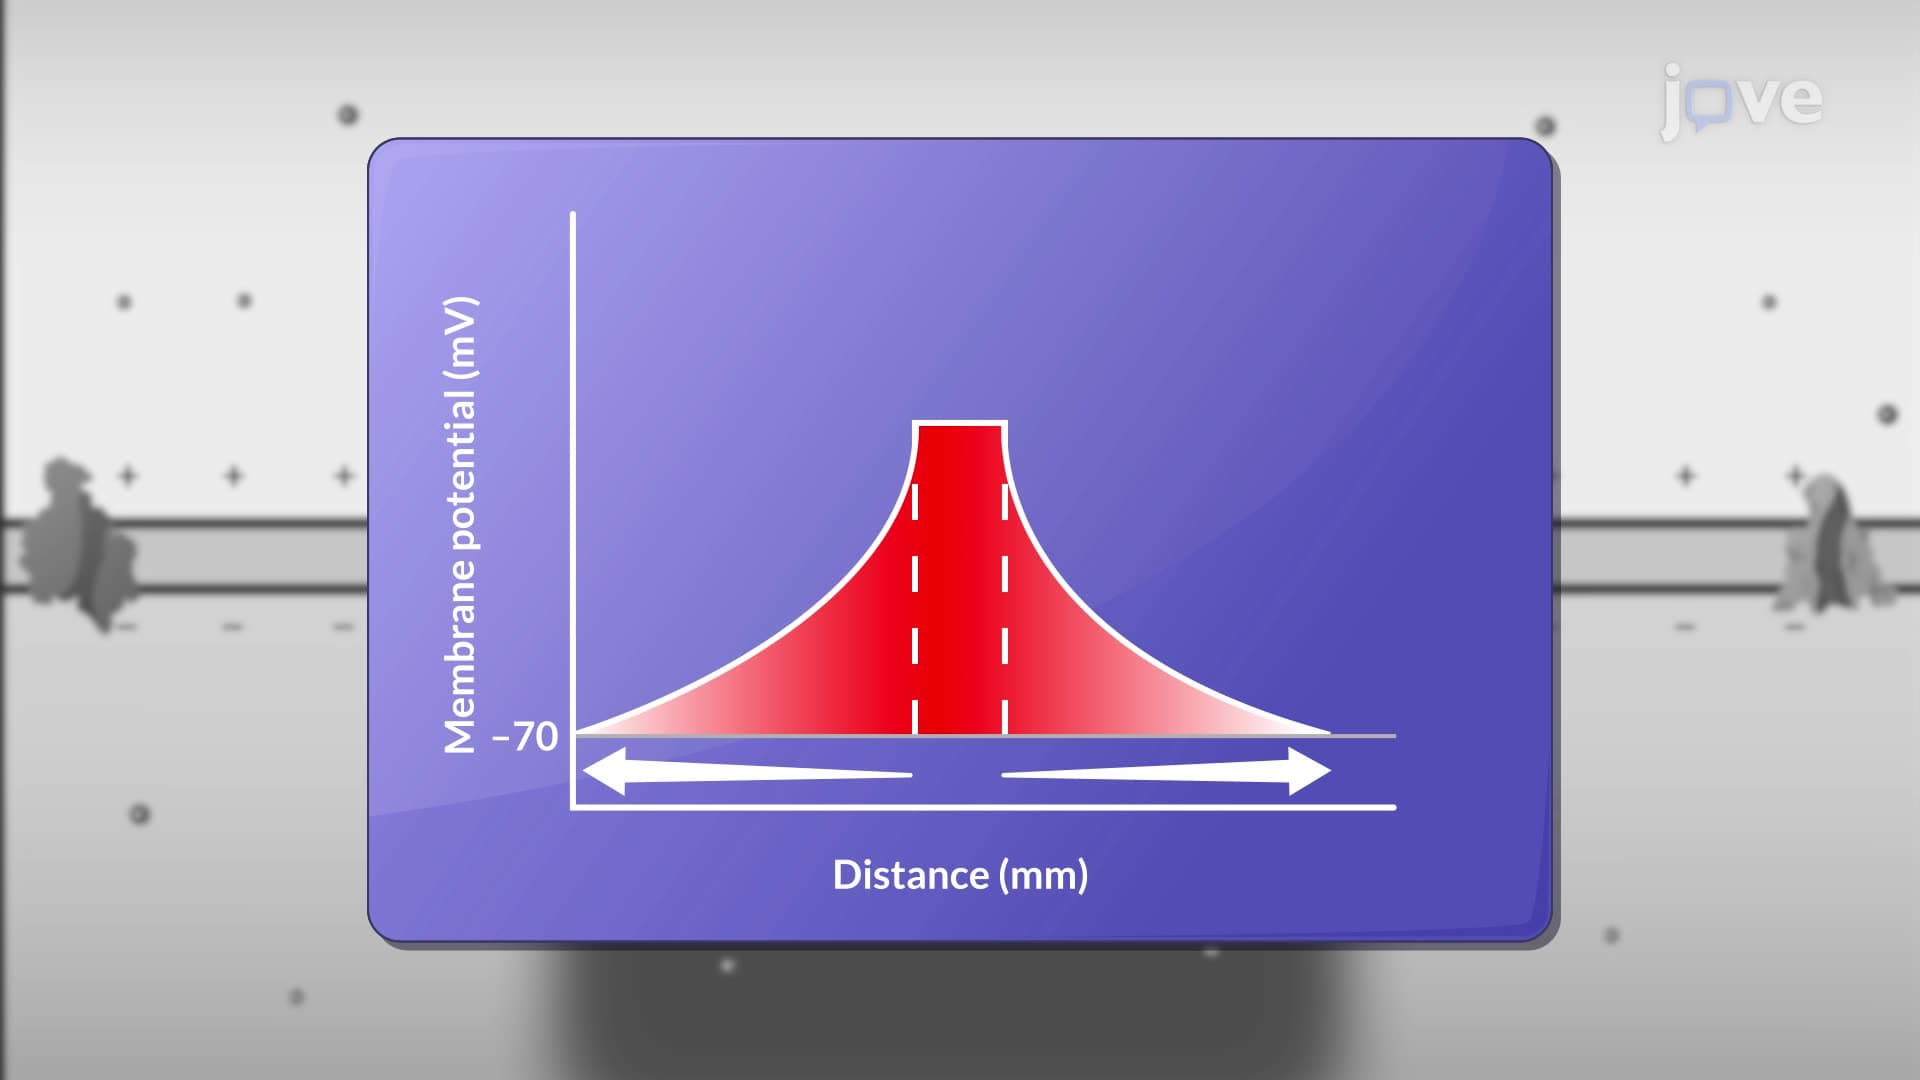
Graded Potential
Graded potentials fall into two categories: depolarizing and hyperpolarizing. Depolarizing graded potentials typically occur when sodium (Na+) or...
 01:15
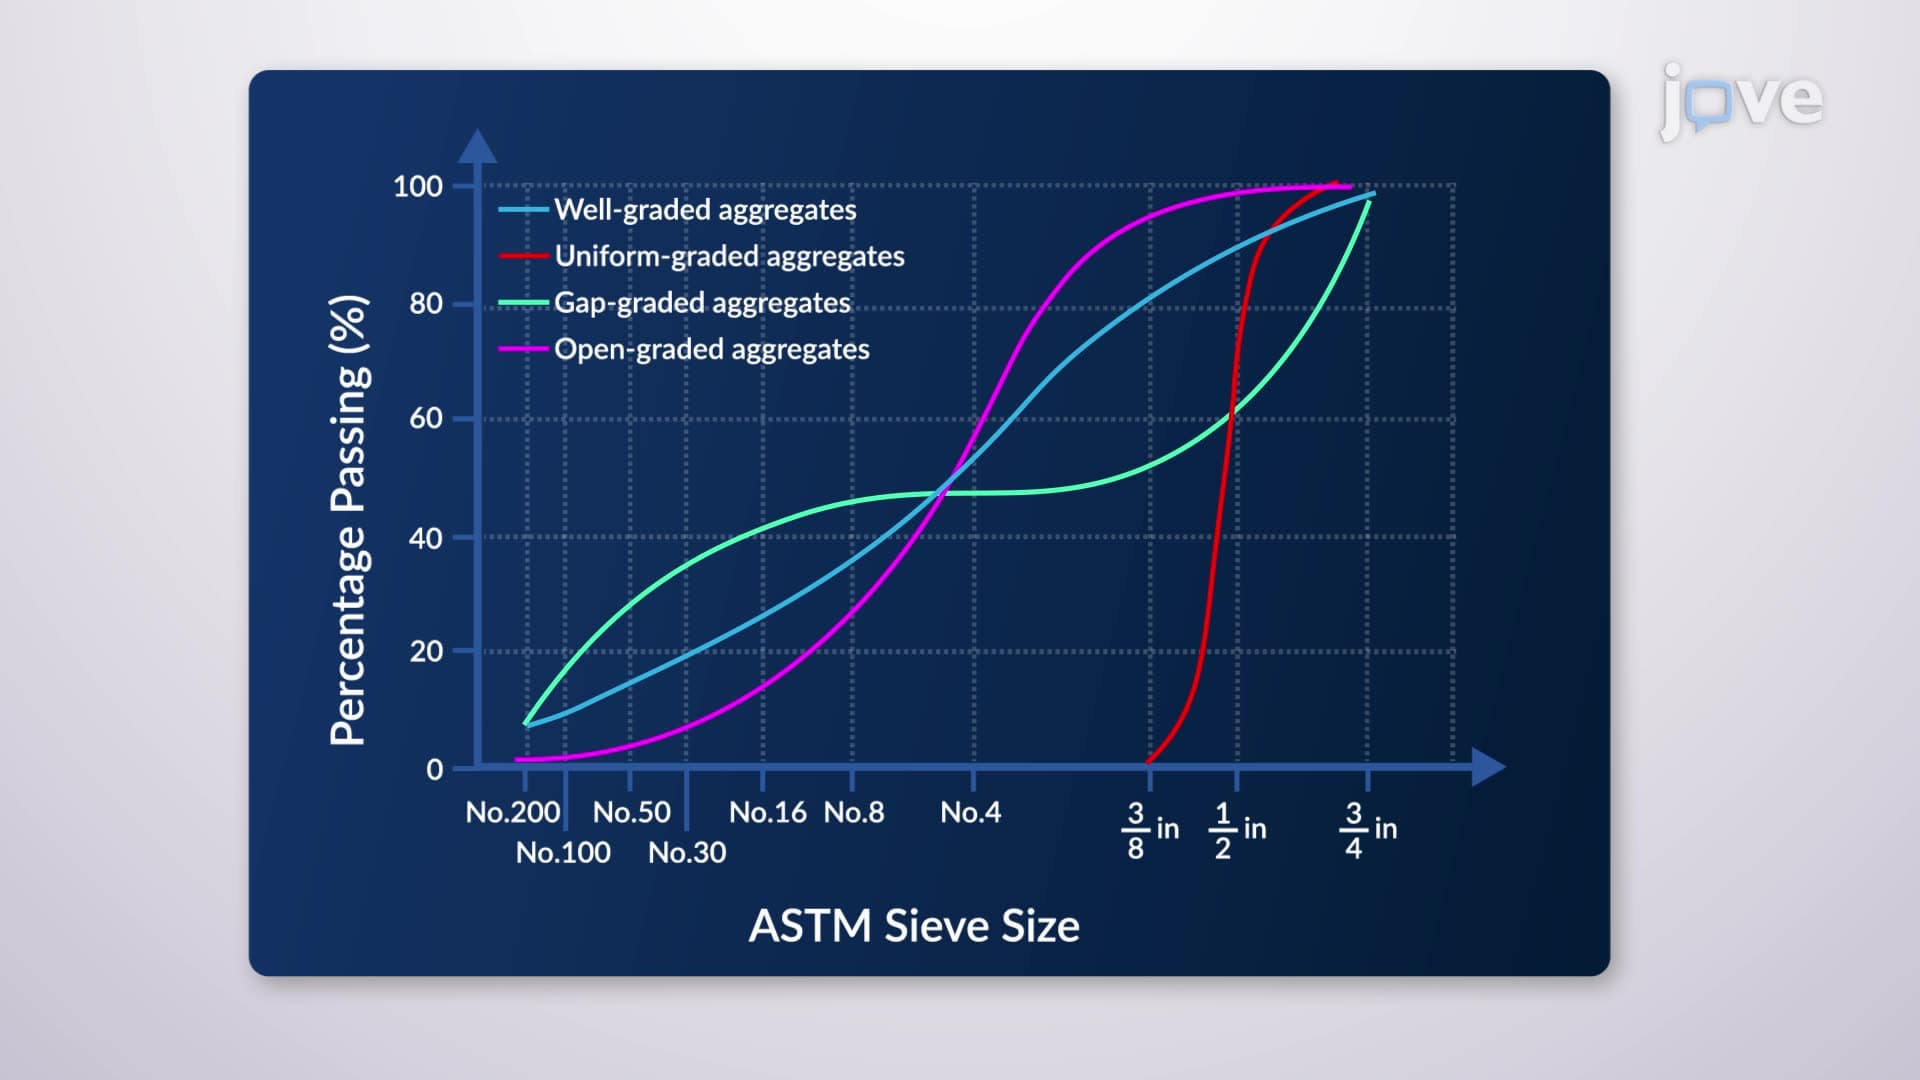
Types of Aggregate Grading
Well-graded aggregates include a complete range of necessary size fractions that fit together to create a dense matrix with minimal voids, represented by a smooth, continuous gradation curve. This type of grading ensures good...
 01:19
Sieve Analysis and Grading Curves
 01:14
Imaging Studies I: CT and MRI
Description of the Procedures
Computed Tomography (CT) scan:
Computed Tomography (CT) scans use X-ray technology to generate detailed images of bones, organs, and tissues. During the scan, the patient lies on a moving table...
 02:19
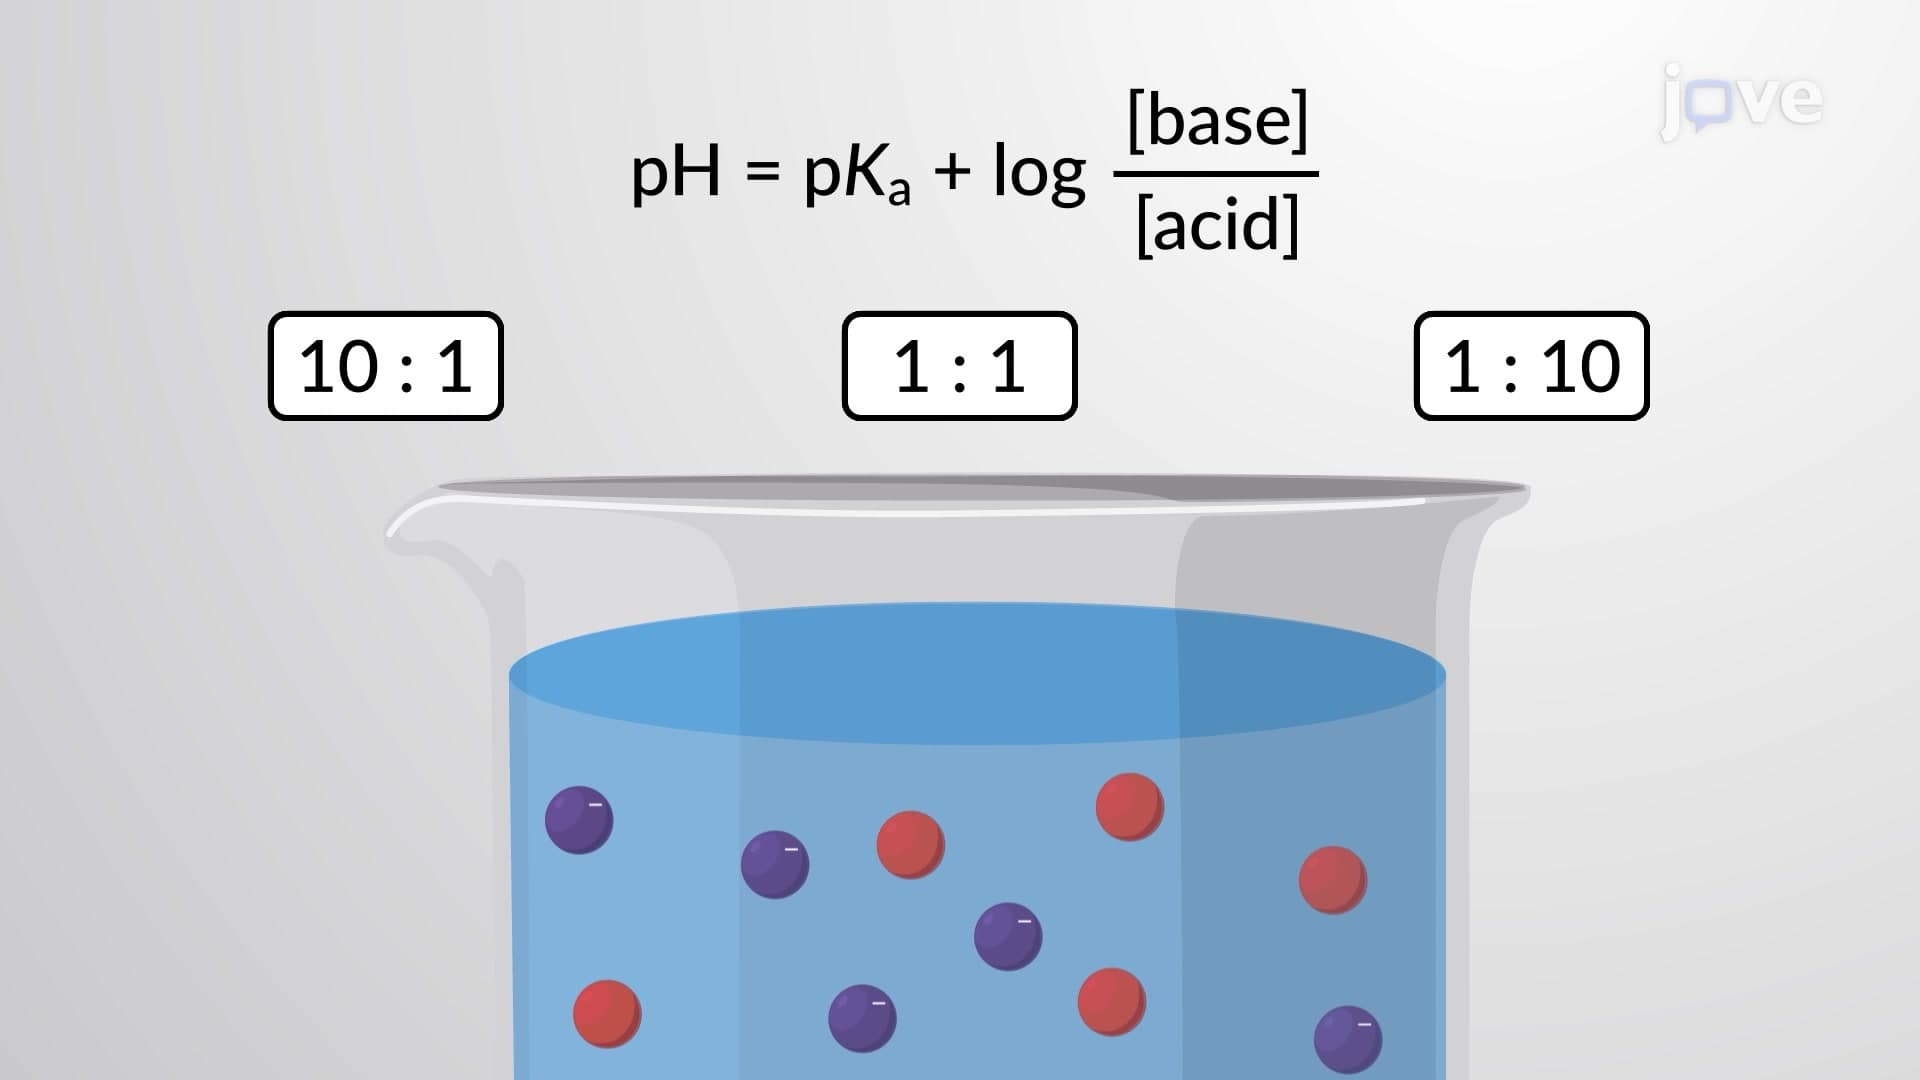
Buffer Effectiveness
The buffer capacity is the amount of acid or base that can be added to a given volume...
 03:26
Framing Effects