Related Experiment Video
Updated: Jan 27, 2026


Setup and Execution of the Rapid Cycle Deliberate Practice Death Notification Curriculum
Published on: August 5, 2020
Clinical Practice Guideline: Tonsillectomy in Children (Update)-Executive Summary
Ron B Mitchell1, Sanford M Archer2, Stacey L Ishman3
11 UT Southwestern Medical Center, Dallas, Texas, USA.

Insights
This updated guideline offers evidence-based recommendations for tonsillectomy in children aged 1-18. It emphasizes watchful waiting for recurrent infections and specific criteria for surgical intervention, including for sleep-disordered breathing.
Area of Science:
- Otolaryngology-Head and Neck Surgery
- Pediatric Surgery
- Evidence-Based Medicine
Background:
- Tonsillectomy is a common pediatric surgical procedure.
- Previous guidelines for tonsillectomy care were updated in 2011.
- This update addresses pre-, intra-, and postoperative care for children aged 1-18.
Purpose of the Study:
- To provide evidence-based recommendations for tonsillectomy in children.
- To optimize perioperative management and reduce variations in care.
- To improve clinician and caregiver education on tonsillectomy indications and outcomes.
Main Methods:
- Multidisciplinary guideline update group including various medical specialists and consumer advocates.
- Systematic review of new evidence, including clinical practice guidelines, systematic reviews, and randomized controlled trials.
- Development of key action statements (KASs) with strong recommendations and recommendations.
Main Results:
- Strong recommendations include watchful waiting for recurrent throat infections based on episode frequency, use of intraoperative dexamethasone, and postoperative pain management with ibuprofen/acetaminophen.
- Recommendations cover assessing modifying factors for tonsillectomy, polysomnography for obstructive sleep-disordered breathing, and counseling on potential persistence of issues post-surgery.
- Strong recommendations against perioperative antibiotics and the use of codeine in children under 12.
Conclusions:
- Updated guidelines provide clear actions for managing children undergoing tonsillectomy.
- Emphasis on shared decision-making, patient education, and specific criteria for surgical intervention.
- Focus on optimizing outcomes and minimizing risks associated with tonsillectomy in pediatric patients.
Objective:
This update of a 2011 guideline developed by the American Academy of Otolaryngology-Head and Neck Surgery Foundation provides evidence-based recommendations on the pre-, intra-, and postoperative care and management of children 1 to 18 years of age under consideration for tonsillectomy. Tonsillectomy is defined as a surgical procedure performed with or without adenoidectomy that completely removes the tonsil, including its capsule, by dissecting the peritonsillar space between the tonsil capsule and the muscular wall. Tonsillectomy is one of the most common surgical procedures in the United States, with 289,000 ambulatory procedures performed annually in children <15 years of age, based on the most recent published data. This guideline is intended for all clinicians in any setting who interact with children who may be candidates for tonsillectomy.
Purpose:
The purpose of this multidisciplinary guideline is to identify quality improvement opportunities in managing children under consideration for tonsillectomy and to create explicit and actionable recommendations to implement these opportunities in clinical practice. Specifically, the goals are to educate clinicians, patients, and/or caregivers regarding the indications for tonsillectomy and the natural history of recurrent throat infections. Additional goals include the following: optimizing the perioperative management of children undergoing tonsillectomy, emphasizing the need for evaluation and intervention in special populations, improving the counseling and education of families who are considering tonsillectomy for their children, highlighting the management options for patients with modifying factors, and reducing inappropriate or unnecessary variations in care. Children aged 1 to 18 years under consideration for tonsillectomy are the target patient for the guideline. For this guideline update, the American Academy of Otolaryngology-Head and Neck Surgery Foundation selected a panel representing the fields of nursing, anesthesiology, consumers, family medicine, infectious disease, otolaryngology-head and neck surgery, pediatrics, and sleep medicine.
Key Action Statements:
The guideline update group made strong recommendations for the following key action statements (KASs): (1) Clinicians should recommend watchful waiting for recurrent throat infection if there have been <7 episodes in the past year, <5 episodes per year in the past 2 years, or <3 episodes per year in the past 3 years. (2) Clinicians should administer a single intraoperative dose of intravenous dexamethasone to children undergoing tonsillectomy. (3) Clinicians should recommend ibuprofen, acetaminophen, or both for pain control after tonsillectomy. The guideline update group made recommendations for the following KASs: (1) Clinicians should assess the child with recurrent throat infection who does not meet criteria in KAS 2 for modifying factors that may nonetheless favor tonsillectomy, which may include but are not limited to multiple antibiotic allergies/intolerance, PFAPA (periodic fever, aphthous stomatitis, pharyngitis, and adenitis), or history of >1 peritonsillar abscess. (2) Clinicians should ask caregivers of children with obstructive sleep-disordered breathing and tonsillar hypertrophy about comorbid conditions that may improve after tonsillectomy, including growth retardation, poor school performance, enuresis, asthma, and behavioral problems. (3) Before performing tonsillectomy, the clinician should refer children with obstructive sleep-disordered breathing for polysomnography if they are <2 years of age or if they exhibit any of the following: obesity, Down syndrome, craniofacial abnormalities, neuromuscular disorders, sickle cell disease, or mucopolysaccharidoses. (4) The clinician should advocate for polysomnography prior to tonsillectomy for obstructive sleep-disordered breathing in children without any of the comorbidities listed in KAS 5 for whom the need for tonsillectomy is uncertain or when there is discordance between the physical examination and the reported severity of obstructive sleep-disordered breathing. (5) Clinicians should recommend tonsillectomy for children with obstructive sleep apnea documented by overnight polysomnography. (6) Clinicians should counsel patients and caregivers and explain that obstructive sleep-disordered breathing may persist or recur after tonsillectomy and may require further management. (7) The clinician should counsel patients and caregivers regarding the importance of managing posttonsillectomy pain as part of the perioperative education process and should reinforce this counseling at the time of surgery with reminders about the need to anticipate, reassess, and adequately treat pain after surgery. (8) Clinicians should arrange for overnight, inpatient monitoring of children after tonsillectomy if they are <3 years old or have severe obstructive sleep apnea (apnea-hypopnea index ≥10 obstructive events/hour, oxygen saturation nadir <80%, or both). (9) Clinicians should follow up with patients and/or caregivers after tonsillectomy and document in the medical record the presence or absence of bleeding within 24 hours of surgery (primary bleeding) and bleeding occurring later than 24 hours after surgery (secondary bleeding). (10) Clinicians should determine their rate of primary and secondary posttonsillectomy bleeding at least annually. The guideline update group made a strong recommendation against 2 actions: (1) Clinicians should not administer or prescribe perioperative antibiotics to children undergoing tonsillectomy. (2) Clinicians must not administer or prescribe codeine, or any medication containing codeine, after tonsillectomy in children younger than 12 years. The policy level for the recommendation about documenting recurrent throat infection was an option: (1) Clinicians may recommend tonsillectomy for recurrent throat infection with a frequency of at least 7 episodes in the past year, at least 5 episodes per year for 2 years, or at least 3 episodes per year for 3 years with documentation in the medical record for each episode of sore throat and ≥1 of the following: temperature >38.3°C (101°F), cervical adenopathy, tonsillar exudate, or positive test for group A beta-hemolytic streptococcus.
Differences From Prior Guideline:
Incorporating new evidence profiles to include the role of patient preferences, confidence in the evidence, differences of opinion, quality improvement opportunities, and any exclusion to which the action statement does not apply. There were 1 new clinical practice guideline, 26 new systematic reviews, and 13 new randomized controlled trials included in the current guideline update. Inclusion of 2 consumer advocates on the guideline update group. Changes to 5 KASs from the original guideline: KAS 1 (Watchful waiting for recurrent throat infection), KAS 3 (Tonsillectomy for recurrent infection with modifying factors), KAS 4 (Tonsillectomy for obstructive sleep-disordered breathing), KAS 9 (Perioperative pain counseling), and KAS 10 (Perioperative antibiotics). Seven new KASs: KAS 5 (Indications for polysomnography), KAS 6 (Additional recommendations for polysomnography), KAS 7 (Tonsillectomy for obstructive sleep apnea), KAS 12 (Inpatient monitoring for children after tonsillectomy), KAS 13 (Postoperative ibuprofen and acetaminophen), KAS 14 (Postoperative codeine), and KAS 15a (Outcome assessment for bleeding). Addition of an algorithm outlining KASs. Enhanced emphasis on patient and/or caregiver education and shared decision making.

Related Concept Videos
 01:04
5-Number Summary
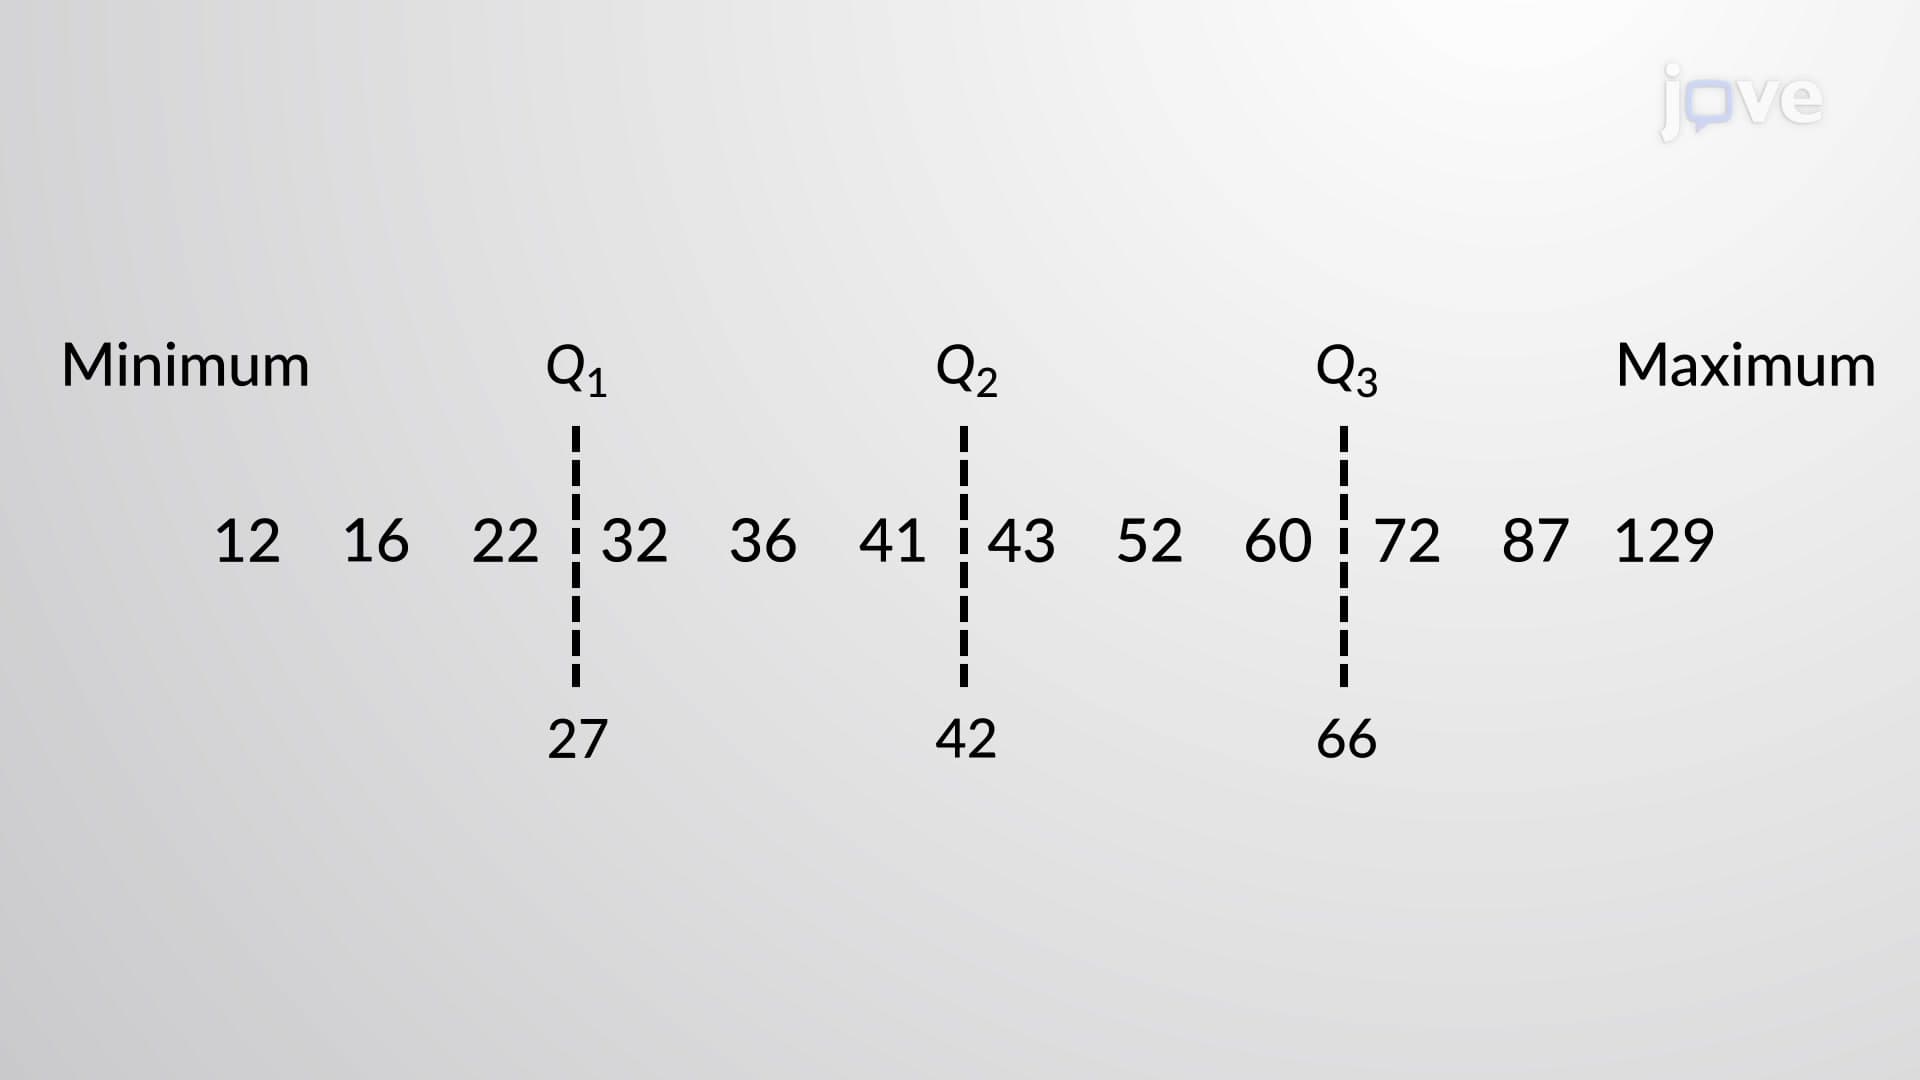
In a box plot, the minimum and maximum data values represent the lower and upper whiskers in the graph, and the median is designated as the center of the box in the chart. The first quartile and third...
 01:31
Discharge Summary Forms
Here's a detailed look at the key components and guidelines for preparing a discharge summary:
 01:26
Guidelines for Nursing Documentation II
Timely documentation is crucial to ensure continuity of care for patients. Any delays in recording or reporting medical information can result in medical errors and even adverse patient outcomes. From medication administration to diagnostic test results, every detail must be accurately and promptly documented to provide the best possible care for patients.
 01:06
Legal Guidelines for Documentation
 01:23
Guidelines for Sketching a Curve
 01:11
Guidelines for Writing Outcome
Patient outcomes reflect the patient's response to the goal rather than what the nurse aims to achieve. Terminology should be observable and measurable to avoid the reader's interpretation. The desired outcome should be realistic and achievable in the designated care timeframe. Expected outcomes should align with adjunctive therapies. The outcome should enhance care...