Related Experiment Video
Updated: Jan 27, 2026
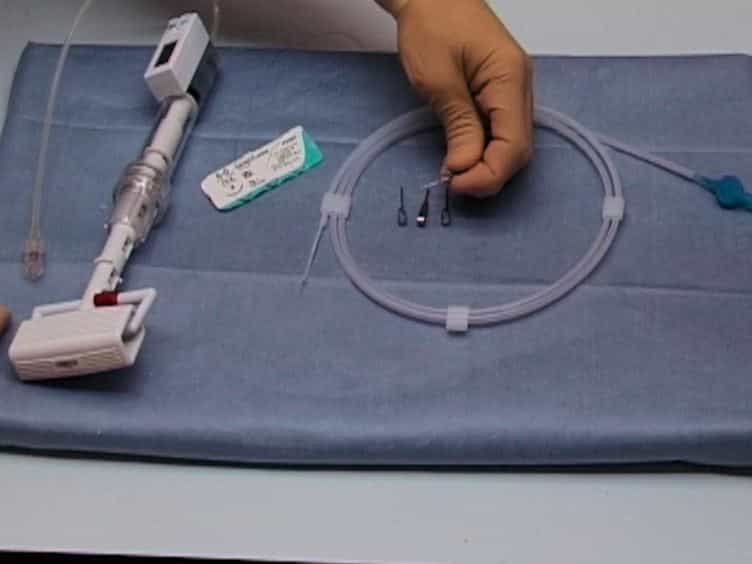
A New Murine Model of Endovascular Aortic Aneurysm Repair
Published on: July 7, 2013
Claims-based surveillance for reintervention after endovascular aneurysm repair among non-Medicare patients
Jesse A Columbo1, Art Sedrakyan2, Jialin Mao2
1Section of Vascular Surgery, Dartmouth-Hitchcock Medical Center, Lebanon, NH; The Dartmouth Institute for Health Policy and Clinical Practice, Lebanon, NH.

Objective:
Many patients who undergo endovascular aortic aneurysm repair (EVR) also undergo repeat procedures, or reinterventions, to address suboptimal device performance and prevent aneurysm rupture. Quality improvement initiatives measuring reintervention after EVR has focused on fee-for-service Medicare patients. However, because patients aged less than 65 years and those with Medicare Advantage represent an important growing subgroup, we used a novel approach leveraging a state data source that captures patients of all ages and with all types of insurance.
Methods:
We identified patients who underwent EVR (2011-2015) within the Vascular Quality Initiative registry and were also listed in the Statewide Planning and Research Cooperative System all-payer claims database of New York. We linked patients in the Vascular Quality Initiative to their Statewide Planning and Research Cooperative System claims file at the patient level with a 96% match rate. We compared outcomes between fee-for-service Medicare eligible, defined as age 65 or older or on dialysis, versus ineligible patients, defined as those younger than 65 and not on dialysis. Our primary outcome was reintervention. We used Cox proportional hazards regression and propensity score matching for risk adjustment.
Results:
We studied 1285 patients with a median follow-up of 16 months (range, 1-57 months). The mean age was 74 years, 79% were male, and 84% of procedures were elective. Nearly one in six patients were not Medicare eligible (14%), and the remainder (86%) were Medicare eligible. Medicare-eligible patients were less likely to be male (77% vs 91%; P < .001), have a history of smoking (79% vs 93%; P < .001), and have a nonelective procedure (15% vs 23%; P = .013). The 3-year Kaplan-Meier rate of reintervention was 21%. We found similar rates of reintervention between Medicare-eligible patients and those who were not (19% vs 20%, log-rank P = .199; unadjusted hazard ratio [HR], 0.75; 95% confidence interval [CI], 0.49-1.16). This finding persisted in both the adjusted and propensity-matched analyses (adjusted HR, 0.82; 95% CI, 0.50-1.34; propensity-matched HR, 0.70; 95% CI, 0.36-1.37).
Conclusions:
Reintervention can be monitored using administrative claims from both Medicare and non-Medicare payers, and serve as an important outcome metric after EVR in patients of all ages. The rate of reintervention seems to be similar between older, Medicare-eligible individuals, and those who are not yet eligible.
Related Concept Videos
 01:54
Base Excision Repair
The first step of...
01:54Base Excision Repair
 01:02
Long-patch Base Excision Repair
 01:11
Testing a Claim about Mean: Known Population SD
Estimating a population mean requires the samples to be distributed normally. The data should be collected from the randomly selected samples having no sampling bias. The sample size needed to be higher than 30, and most importantly, the population standard deviation should be already known.
In most realistic situations, the population standard deviation is often unknown, but in rare circumstances, when it...
 01:36
Mismatch Repair
 02:27
Base-pairing and DNA Repair