Related Experiment Video
Updated: Jan 27, 2026


Author Spotlight: Advancing Labor Management Through Electromyometrial Imaging for Understanding Uterine Contractions
Published on: May 26, 2023
Timing of delivery in women with prior uterine rupture: a decision analysis
Zoë C Frank1, Vanessa R Lee1, Alyssa R Hersh1
1Department of Obstetrics and Gynecology, Oregon Health and Sciences University, Portland, OR, USA.

Background: Uterine rupture is an obstetric complication with high rates of associated maternal and neonatal morbidity and mortality. However, limited guidance for the timing of delivery in women with a history of prior uterine rupture exists.Objective: To determine the optimal gestational age of delivery in women with prior uterine rupture.Study design: A decision-analytic model was built using TreeAge software to compare the outcomes of repeat cesarean delivery when performed at 32, 33, 34, 35, or 36 weeks gestation in a theoretical cohort of 1000 women with prior uterine rupture. Strategies involved expectant management until a later gestational age accounting for the risks of spontaneous uterine rupture, spontaneous labor, uterine rupture following spontaneous labor, and stillbirth during each successive week that a woman was still pregnant. Maternal outcomes included uterine rupture, hysterectomy, and death. Neonatal outcomes included hypoxic-ischemic encephalopathy, cerebral palsy, and death. Probabilities were derived from the literature and total quality-adjusted life years (QALYs) were calculated. Sensitivity analyses were used to vary model inputs to investigate the robustness of our baseline assumptions.Results: In our theoretical cohort of 1000 pregnant women with a history of prior uterine rupture, cesarean delivery at 34 weeks maximized maternal and neonatal QALYs. Compared to delivery at 36 weeks, delivery at 34 weeks would prevent 38.6 uterine ruptures, 0.079 maternal deaths, 6.10 hysterectomies, and 12.1 neonatal deaths but results in 4.70 more cases of cerebral palsy. Univariate sensitivity analysis found that repeat cesarean at 34 weeks remained the optimal strategy until the probability of spontaneous repeat uterine rupture (baseline estimate: 0.68%) fell below 0.2% or rose above 0.9%, at which point, a strategy of delivery at 35 or 32 weeks became optimal, respectively. However, Monte Carlo simulation demonstrated that delivery at 35 weeks was the optimal strategy 37% of the time, whereas 34 weeks was the optimal strategy 17% of the time.Conclusion: The optimal time for repeat cesarean delivery in women with prior uterine rupture appears to be between 34-0/7 and 35-6/7 weeks gestation.
Background: Uterine rupture is an obstetric complication with high rates of associated maternal and neonatal morbidity and mortality. However, limited guidance for the timing of delivery in women with a history of prior uterine rupture exists.Objective: To determine the optimal gestational age of delivery in women with prior uterine rupture.Study design: A decision-analytic model was built using TreeAge software to compare the outcomes of repeat cesarean delivery when performed at 32, 33, 34, 35, or 36 weeks gestation in a theoretical cohort of 1000 women with prior uterine rupture. Strategies involved expectant management until a later gestational age accounting for the risks of spontaneous uterine rupture, spontaneous labor, uterine rupture following spontaneous labor, and stillbirth during each successive week that a woman was still pregnant. Maternal outcomes included uterine rupture, hysterectomy, and death. Neonatal outcomes included hypoxic-ischemic encephalopathy, cerebral palsy, and death. Probabilities were derived from the literature and total quality-adjusted life years (QALYs) were calculated. Sensitivity analyses were used to vary model inputs to investigate the robustness of our baseline assumptions.Results: In our theoretical cohort of 1000 pregnant women with a history of prior uterine rupture, cesarean delivery at 34 weeks maximized maternal and neonatal QALYs. Compared to delivery at 36 weeks, delivery at 34 weeks would prevent 38.6 uterine ruptures, 0.079 maternal deaths, 6.10 hysterectomies, and 12.1 neonatal deaths but results in 4.70 more cases of cerebral palsy. Univariate sensitivity analysis found that repeat cesarean at 34 weeks remained the optimal strategy until the probability of spontaneous repeat uterine rupture (baseline estimate: 0.68%) fell below 0.2% or rose above 0.9%, at which point, a strategy of delivery at 35 or 32 weeks became optimal, respectively. However, Monte Carlo simulation demonstrated that delivery at 35 weeks was the optimal strategy 37% of the time, whereas 34 weeks was the optimal strategy 17% of the time.Conclusion: The optimal time for repeat cesarean delivery in women with prior uterine rupture appears to be between 34-0/7 and 35-6/7 weeks gestation.


Related Concept Videos
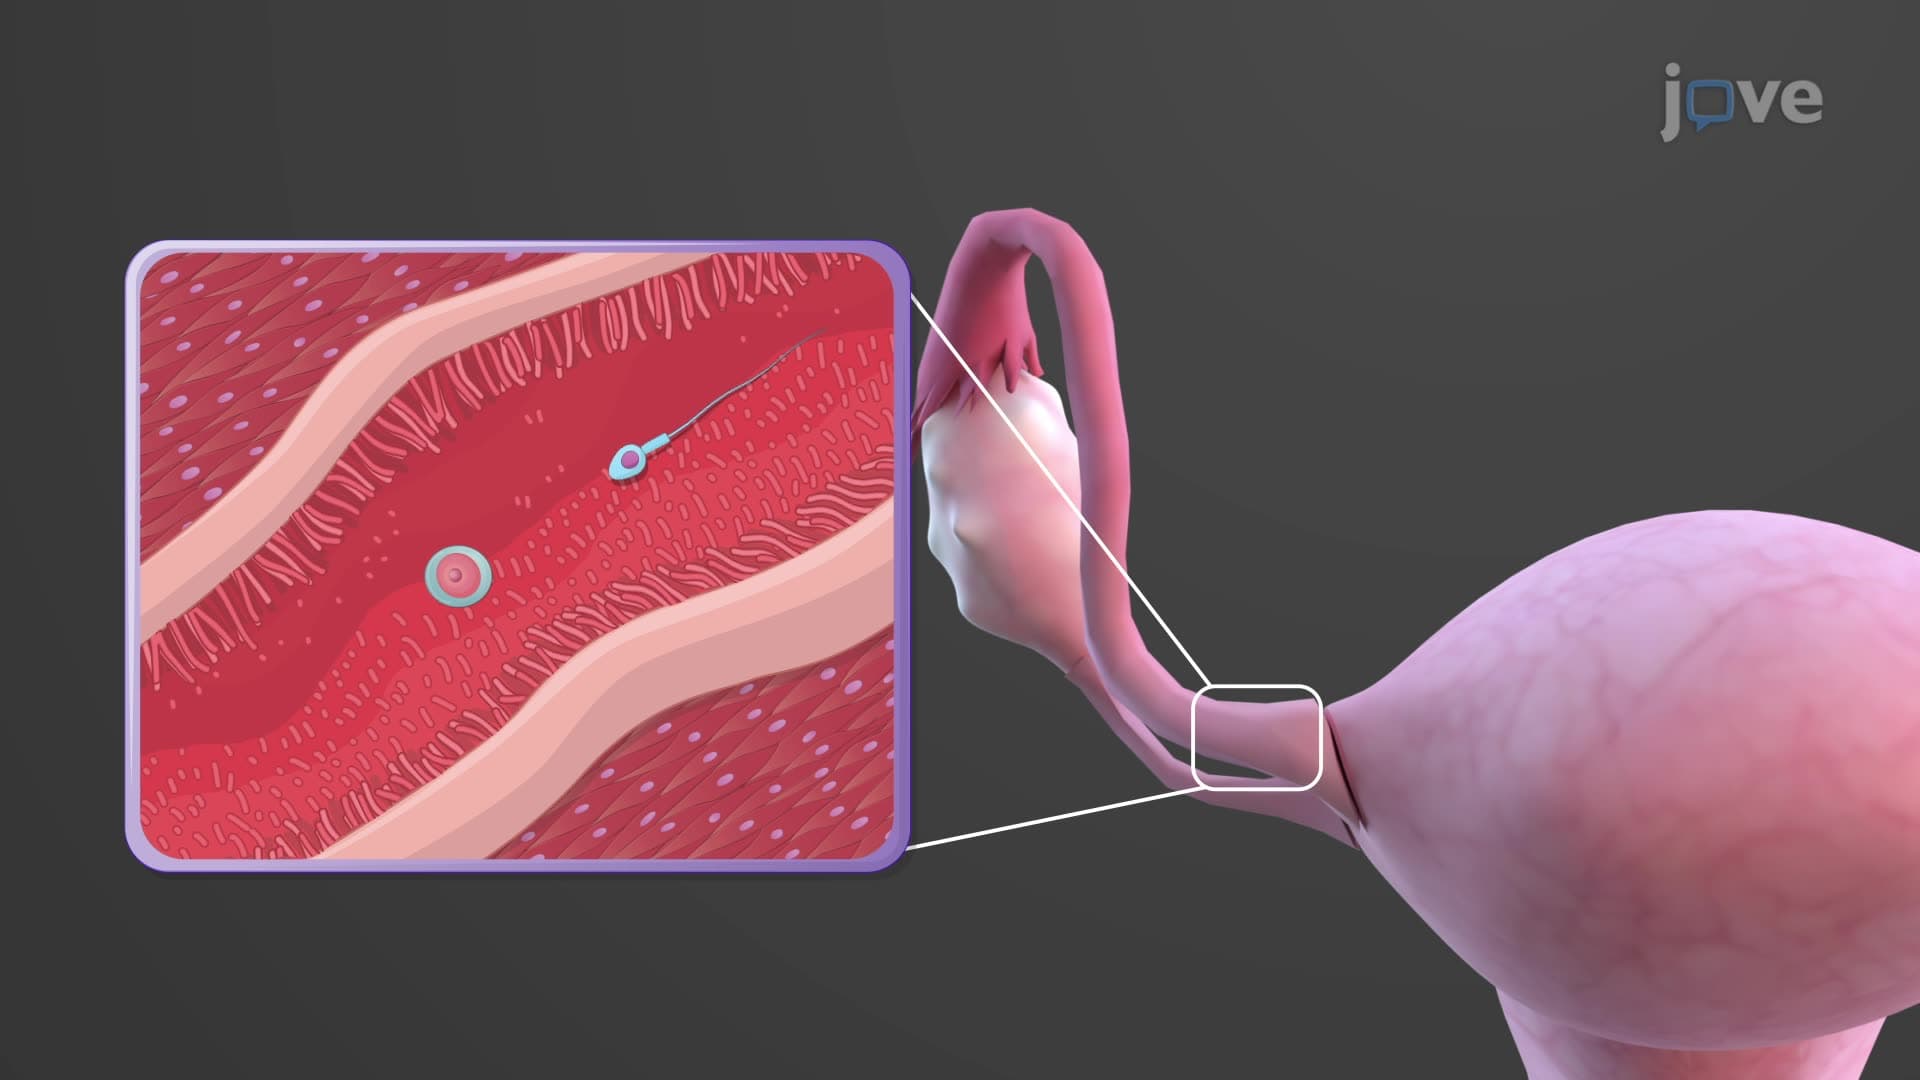 01:16
Uterine Tubes
 01:20
Decision Making
Automatic decision-making is fast, intuitive, and relies on gut feelings...
 01:05
Noncompartmental Analysis: Mean Residence Time
After the administration of a drug through intravenous bolus injection, the drug molecules are distributed throughout the body and remain there for varying periods. The MRT represents the average time these drug molecules stay in the...
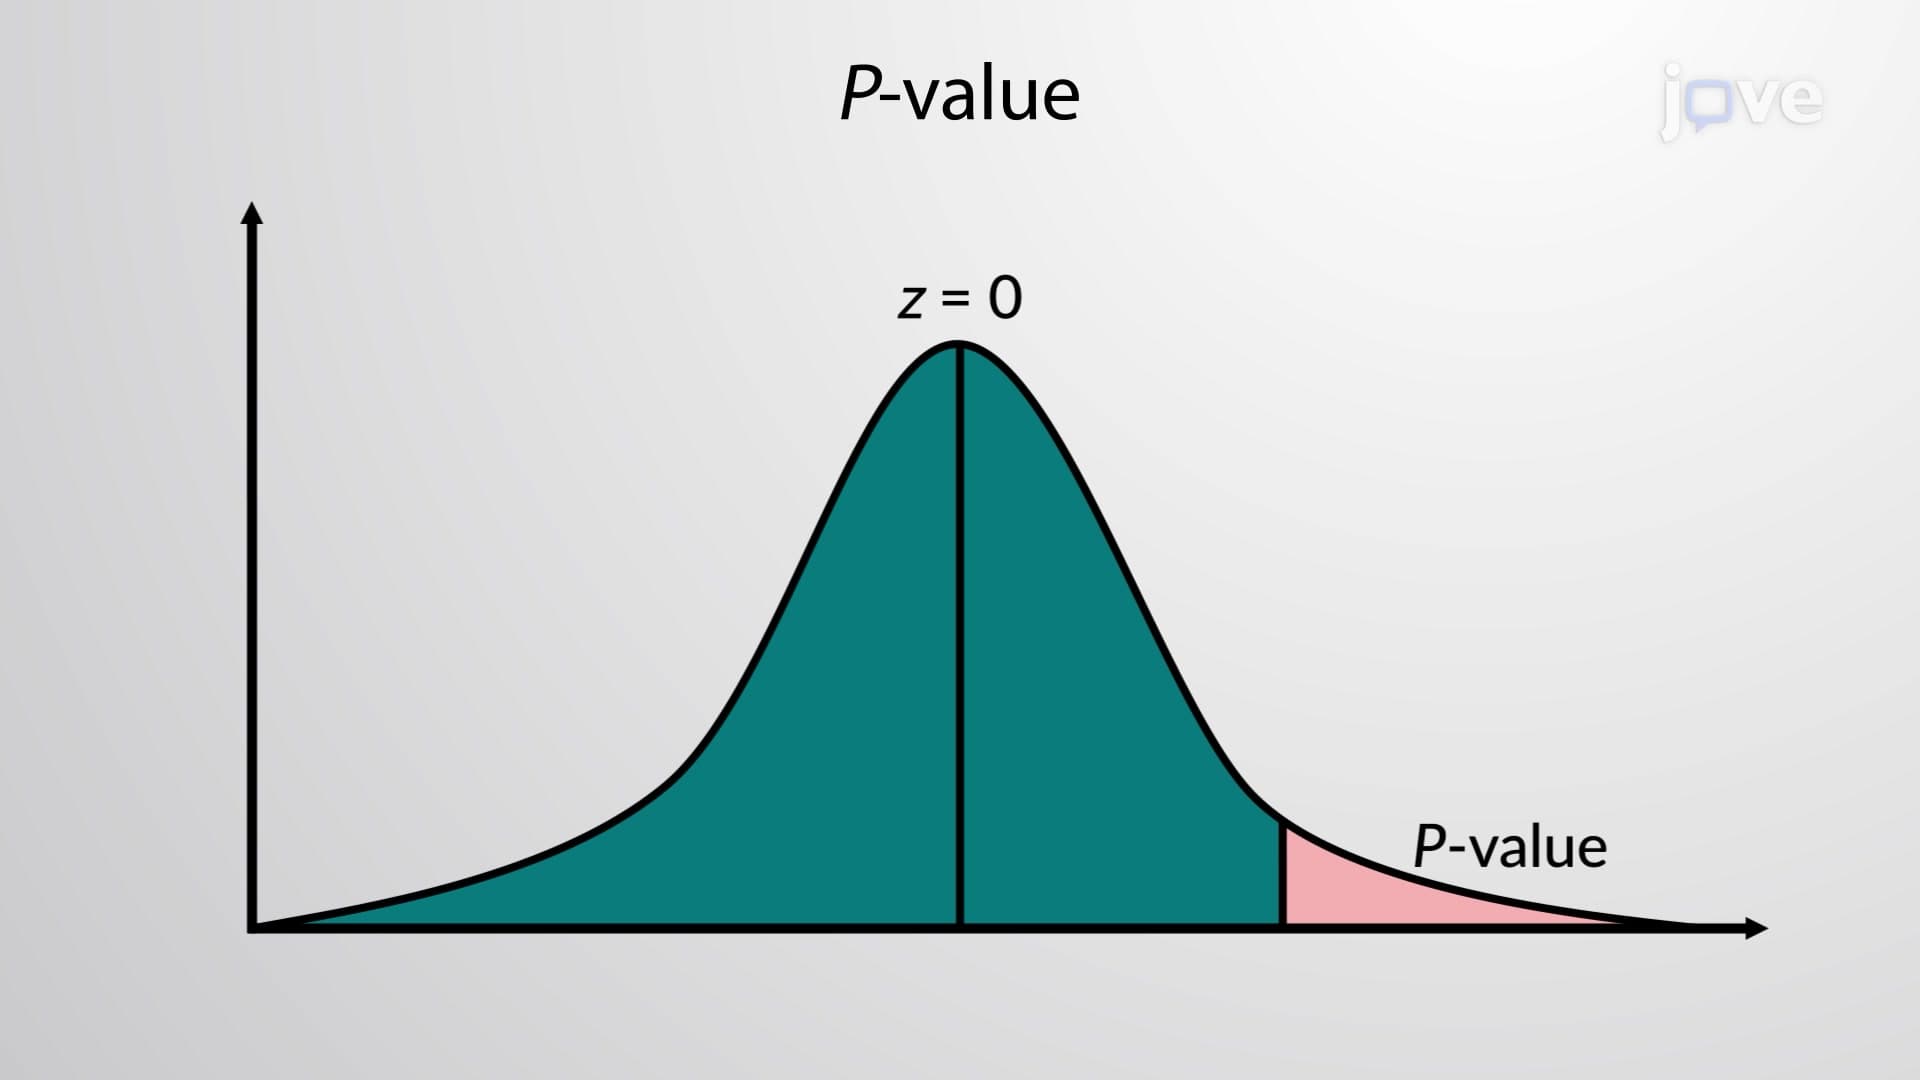 01:09
Decision Making: P-value Method
First, a specific claim about the population parameter is proposed. The claim is based on the research question and is stated in a simple form. Further, an opposing statement to the claim is also stated. These statements can act as null and alternative hypotheses: a null hypothesis would be a neutral statement while the alternative hypothesis can...
 01:14
Decision Making: Traditional Method
First, a specific claim about the population parameter is decided based on the research question and is stated in a simple form. Further, an opposing statement to this claim is also stated. These statements can act as null and alternative hypotheses, out of which a null hypothesis would be a...
 01:02
Noncompartmental Analysis: Mean Transit, Absorption and Dissolution Time
One of the key parameters is the mean transit time (MTT), which refers to the total duration required for drug molecules to transit through the body. MTT is determined by calculating the ratio of the area under the moment curve to the area...