Related Experiment Video
Updated: Jan 26, 2026
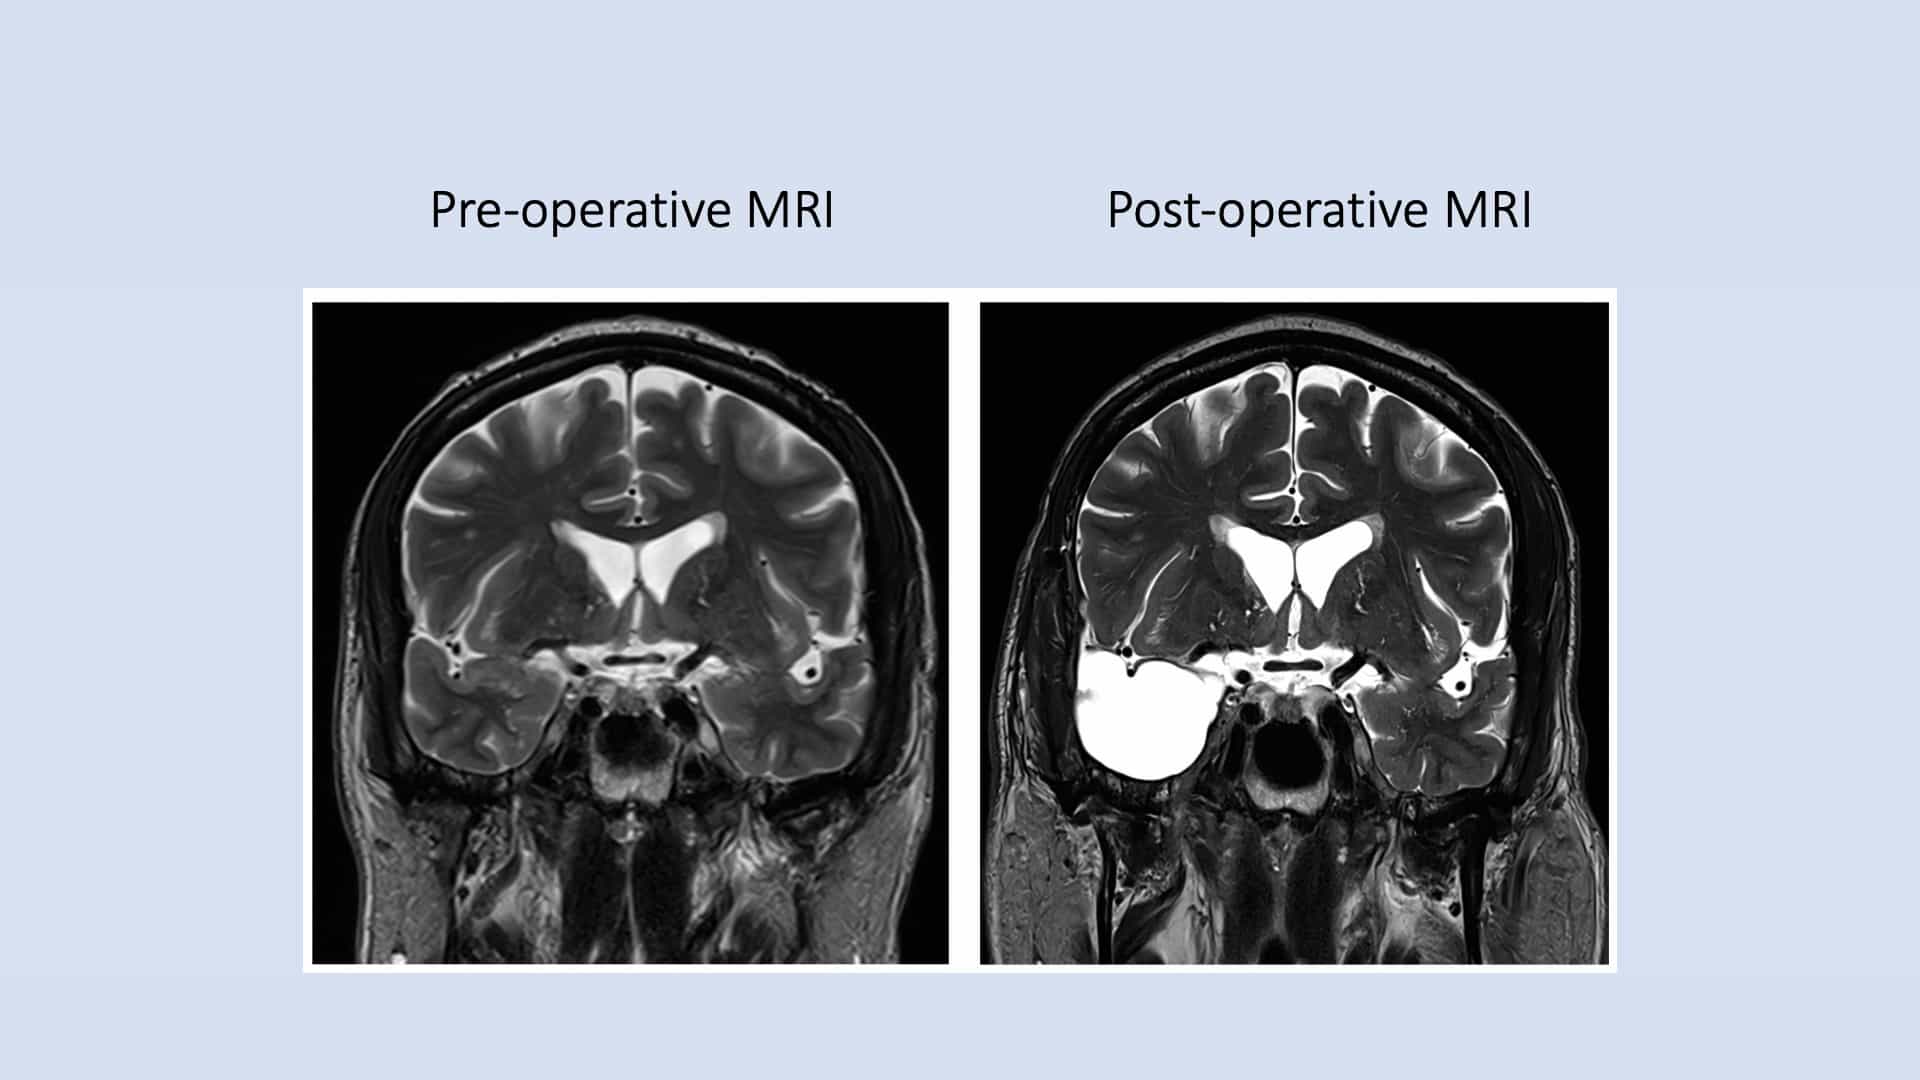

Anteromesial Temporal Lobectomy for Medically Intractable Temporal Lobe Epilepsy: An Operative Study
Published on: August 15, 2025
Making Rash Decisions in Epilepsy: Evaluating Hypersensitivity Reactions to Anti-seizure Medications

Insights
Antiepileptic drugs (AEDs) can cause hypersensitivity reactions in children, with 5.4% experiencing them. Aromatic AEDs significantly increase this risk, necessitating close patient monitoring.
Area of Science:
- Pediatric Neurology
- Clinical Immunology
- Pharmacovigilance
Background:
- Antiepileptic drugs (AEDs) are associated with a spectrum of hypersensitivity reactions in children, ranging from mild rashes to severe cutaneous adverse events.
- Understanding the frequency and clinical presentation of these reactions is crucial for patient safety.
Purpose of the Study:
- To determine the prevalence and clinical features of hypersensitivity reactions to AEDs in pediatric patients.
- To identify risk factors associated with AED hypersensitivity in children.
Main Methods:
- A prospective study monitored children prescribed AEDs for the first time, evaluating those who developed skin rashes.
- Data on patient demographics, AEDs used, and reaction types were collected and analyzed.
- A separate analysis of the US FDA Adverse Event Reporting System quantified SJS/TEN risk associated with AEDs.
Main Results:
- Hypersensitivity reactions occurred in 5.4% of pediatric patients, with cutaneous reactions in 71% and severe reactions in 29%.
- Younger age (<12 years), use of aromatic AEDs, and polytherapy were associated with increased hypersensitivity risk.
- AEDs as a class showed a 9-fold increased risk of Stevens-Johnson Syndrome/Toxic Epidermal Necrolysis (SJS/TEN) compared to non-AEDs, with specific AEDs like zonisamide and lamotrigine having high-risk estimates.
Conclusions:
- Allergic reactions to AEDs, though rare, can lead to life-threatening SJS/TEN, emphasizing the need for vigilance.
- Close monitoring of patients on AEDs, particularly aromatic ones, is essential.
- Increased awareness of AED-associated SJS/TEN risks and early recognition of symptoms can help mitigate adverse events.
Abstract:
The Frequency and Clinical Features of Hypersensitivity Reactions to Antiepileptic Drugs in Children: A Prospective Study Guvenir H, Dibek Misirlioglu E, Civelek E. J Allergy Clin Immunol Pract. 2018;6(6):2043-2050.
Background:
Antiepileptic drugs (AEDs) can cause hypersensitivity reactions during childhood. Studies report a wide clinical spectrum of reactions with AED use, ranging from a mild rash to severe cutaneous reactions.
Objective:
To determine the prevalence and clinical features of AED hypersensitivity reactions during childhood.
Methods:
Patients in our pediatric neurology clinic who were prescribed an AED for the first time between November 2015 and November 2016 were monitored and those who developed skin rash during this period were evaluated.
Results:
A total of 570 patients were evaluated. The median age of the patients was 8.86 (interquartile range, 4.2-13.7) years, and 55.8% (318) of patients were male. The most frequently used AEDs were valproic acid (42%, n = 285) and carbamazepine (20.4%, n = 116). Hypersensitivity reactions to AEDs developed in 5.4% of patients. Of these patients, 71% (29) had cutaneous drug reactions and 29% (9) had severe cutaneous drug reactions; 61.3% (19) were using aromatic AEDs, and the leading suspected AED was carbamazepine (45.2%). Comparison of patients who did and did not develop AED hypersensitivity showed that hypersensitivity was more frequent among patients who were younger than 12 years, who used aromatic AEDs, or who used multiple AEDs. In addition, according to regression analysis results, aromatic AED use significantly increased the risk of AED hypersensitivity ( P < .001).
Conclusions:
Although allergic reactions to AEDs are rare, they are of significance because they can cause life-threatening severe cutaneous drug reactions. Therefore, patients receiving AEDs, especially aromatic AEDs, must be monitored closely. Stevens-Johnson Syndrome and Toxic Epidermal Necrolysis With Antiepileptic Drugs: An Analysis of the US Food and Drug Administration Adverse Event Reporting System Borrelli EP, Lee EY, Descoteaux AM, Kogut SJ, Caffrey AR. Epilepsia. 2018;59(12):2318-2324.
Objective:
Stevens-Johnson syndrome (SJS) and toxic epidermal necrolysis (TEN) are rare and potentially fatal adverse skin reactions that are most commonly triggered by certain medications. One class of medications that has been highly associated with SJS/TEN reactions is antiepileptic drugs (AEDs). We sought to quantify the risk of SJS/TEN associated with AEDs as a class, as well as individual AEDs, in the United States.
Methods:
An analysis was performed of the US Food and Drug Administration Adverse Event Reporting System from July 2014 through December 2017. Rates of SJS/TEN were calculated for each AED compared with all other non-AEDs. Reporting odds ratios (RORs), proportional reporting ratios (PRRs), and 95% confidence intervals (CIs) were calculated using OpenEpi.
Results:
With 198 reports, AEDs had more reports of SJS/TEN than any other medication class. The AEDs as a class had an ROR of 8.7 (95% CI, 7.5-10.2) and a PRR of 8.7 (95% CI, 7.5-10.2) compared with all other non-AEDs. The AEDs with the highest risk estimates were zonisamide (ROR, 70.2; 95% CI, 33.1-148.7; PRR, 68.7; 95% CI, 32.9-143.5), rufinamide (ROR, 60.0; 95% CI, 8.3-433.5; PRR, 58.9; 95% CI, 8.4-411.5), clorazepate (ROR, 56.0; 95% CI, 7.8-404.1; PRR, 55.1; 95% CI, 7.8-385.0), lamotrigine (ROR, 53.0; 95% CI, 43.2-64.9; PRR, 52.2; 95% CI, 42.7-63.7), phenytoin (ROR, 26.3; 95% CI, 15.5-44.7; PRR, 26.1; 95% CI, 15.4-44.2), and carbamazepine (ROR, 24.5; 95% CI, 16.0-37.5; PRR, 24.3; 95% CI, 16.0-37.1).
Significance:
Although AEDs as a class were associated with 9 times the risk of SJS/TEN compared with non-AEDs, there were 6 AEDs with risk estimates greater than 20. Increased awareness of this risk among both prescribers and patients, particularly variations in risk among different AEDs, along with education on early recognition of SJS/TEN signs/symptoms, may help mitigate the number and severity of these adverse events.

Related Concept Videos
 01:24
Epilepsy and Seizures: Overview
Various factors can trigger epilepsy, including genetic factors, brain damage, metabolic causes, and unknown etiology. Diagnosis of epilepsy involves electroencephalography (EEG), which...
 01:30
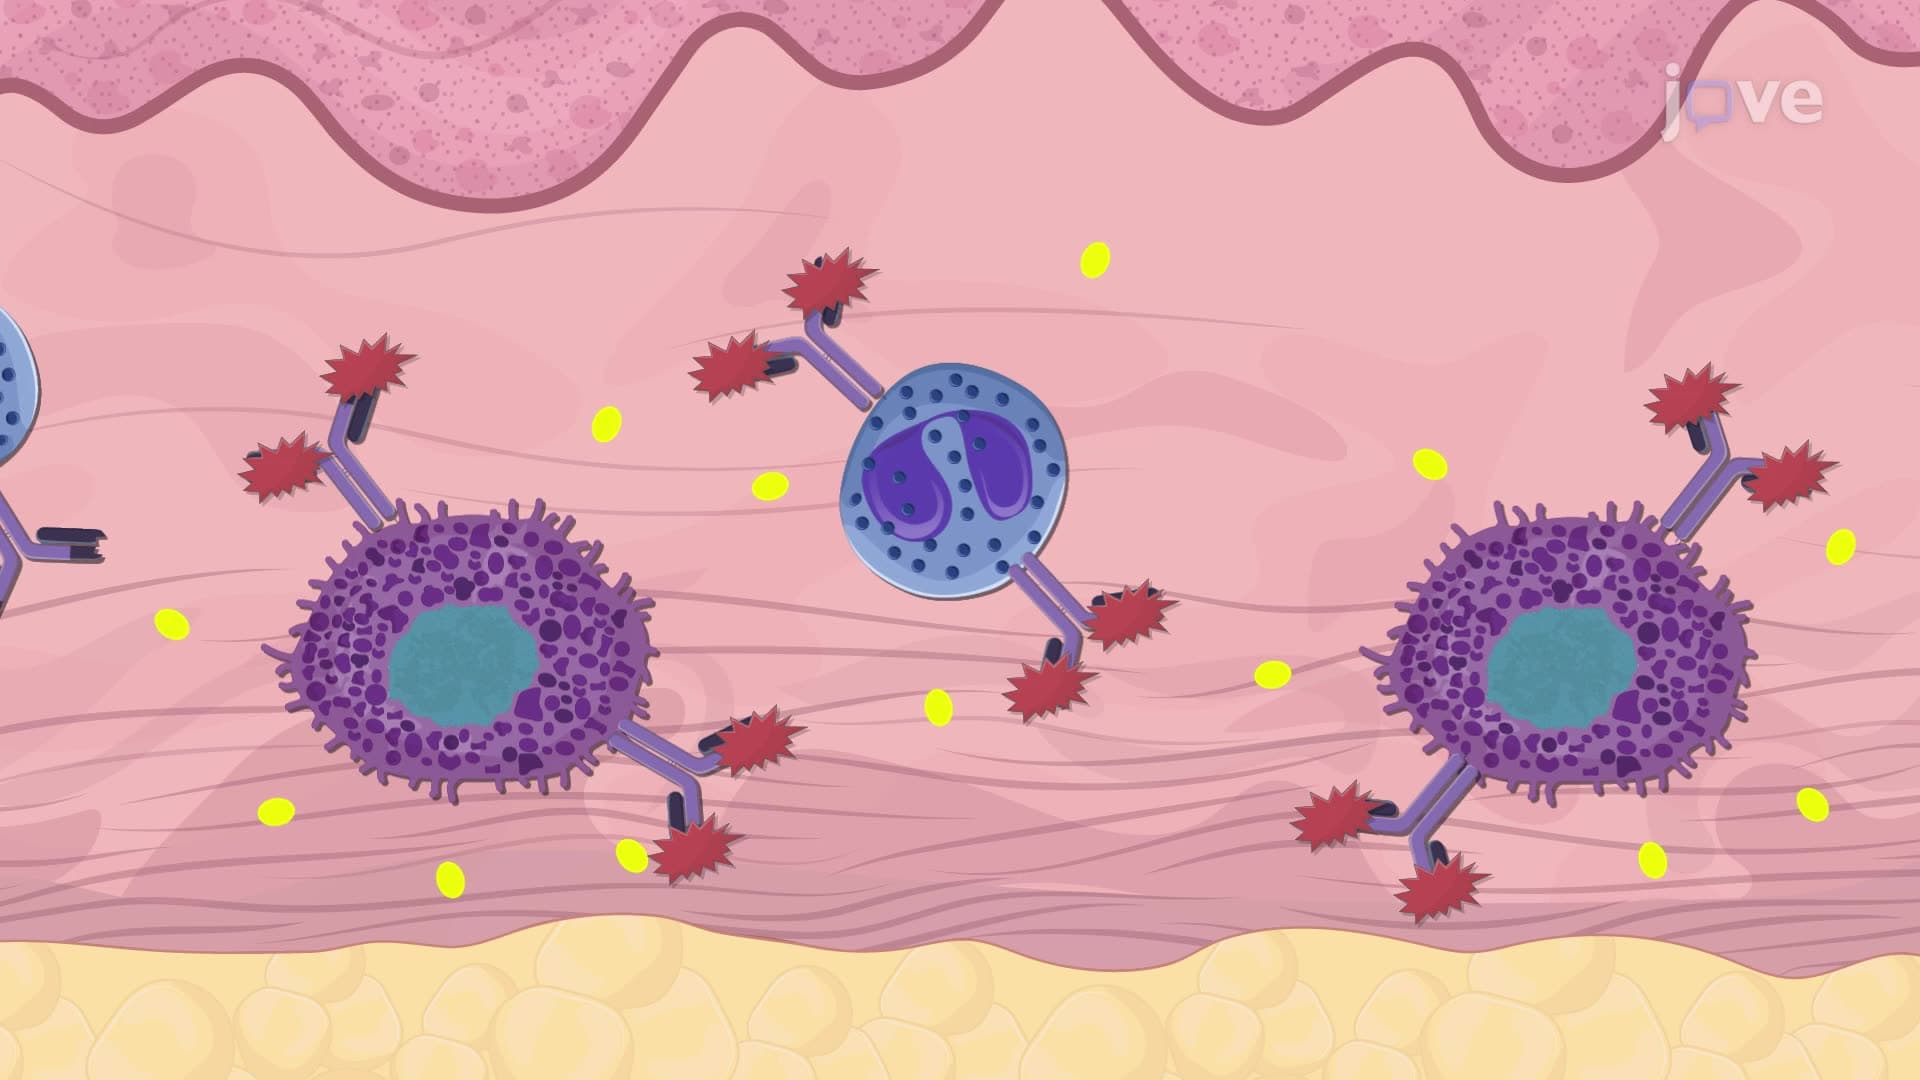
Hypersensitivities
Types of Hypersensitivities
Hypersensitivity reactions are categorized into four types: Type 1, Type 2, Type 3, and Type 4. Each type has a distinct mechanism...
 02:06
Allergic Reactions
 01:13
Seizures: Classification
Seizures are typically classified into two main categories: focal and generalized seizures.
Focal Seizures
Focal seizures originate from specific regions of the brain. These seizures are further sub-classified into two types:
 01:20
Decision Making
Automatic decision-making is fast, intuitive, and relies on gut feelings...
 01:09
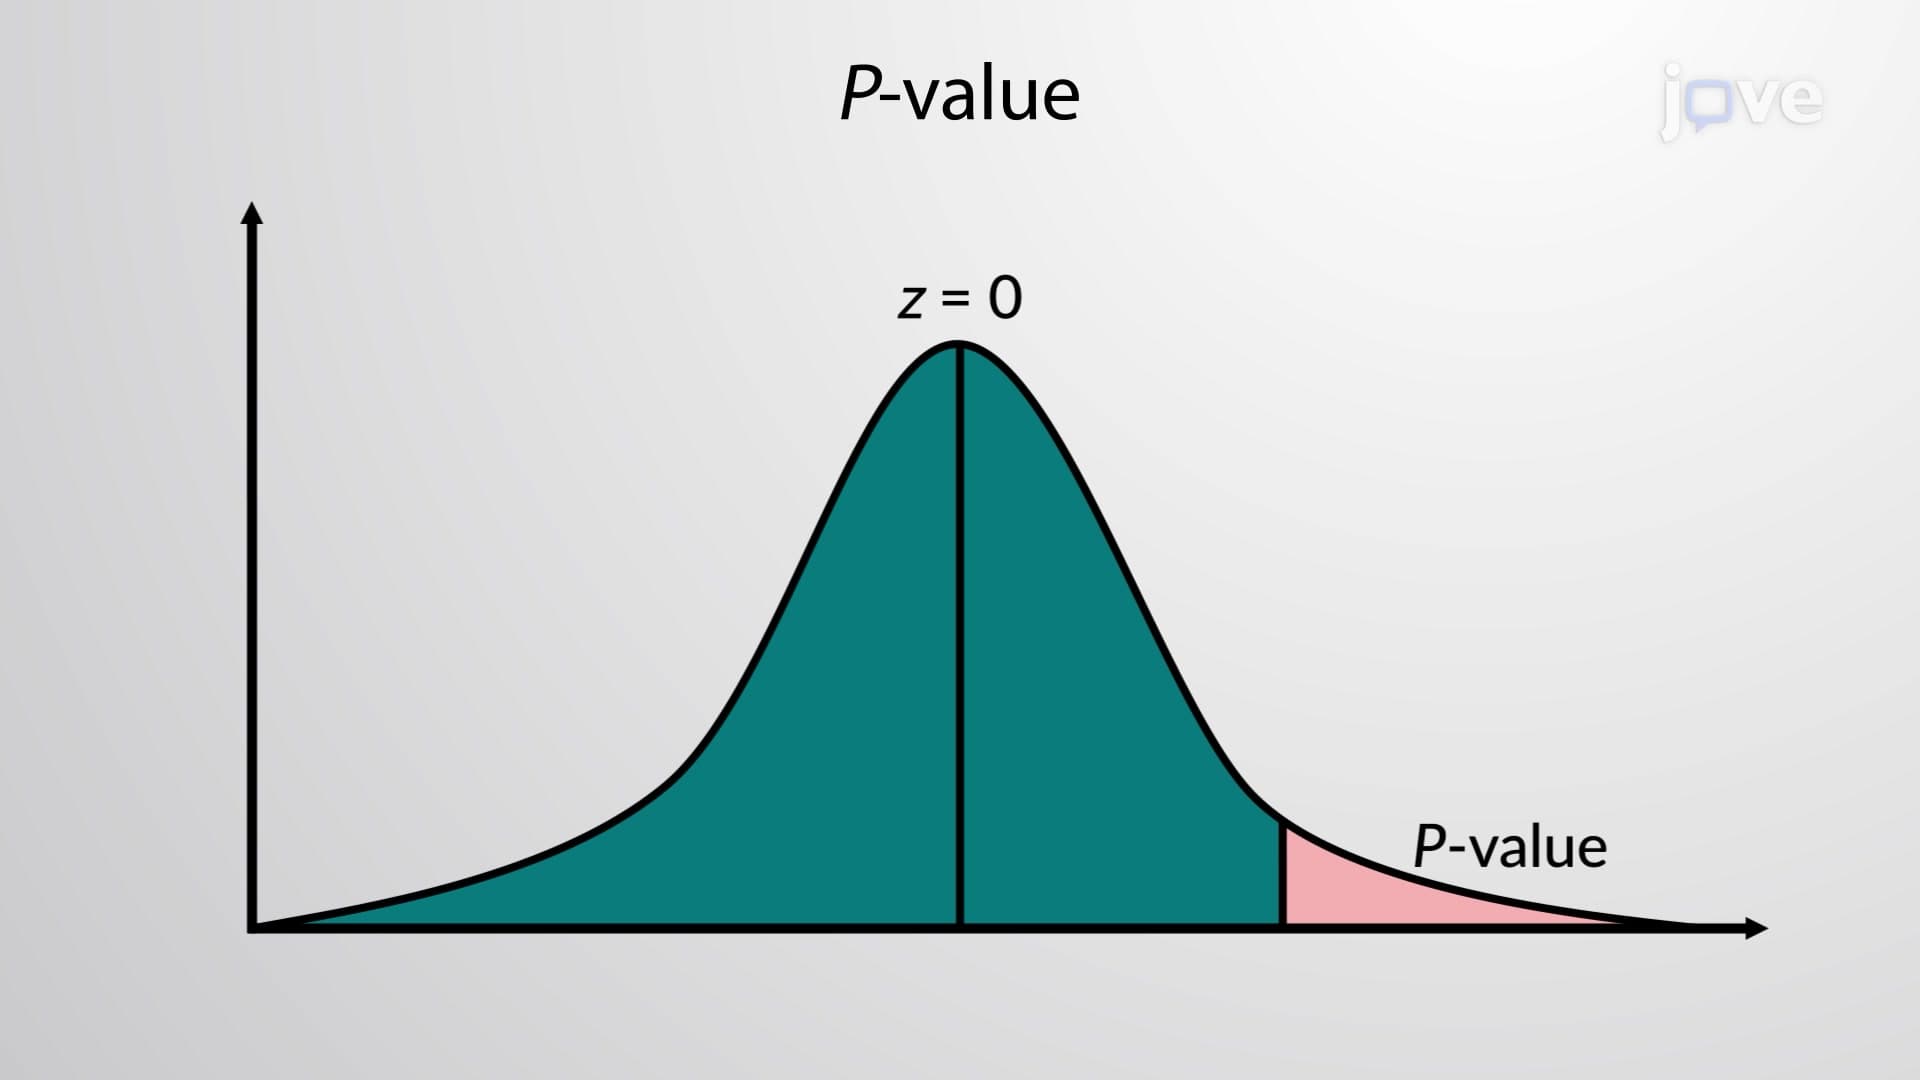
Decision Making: P-value Method
First, a specific claim about the population parameter is proposed. The claim is based on the research question and is stated in a simple form. Further, an opposing statement to the claim is also stated. These statements can act as null and alternative hypotheses: a null hypothesis would be a neutral statement while the alternative hypothesis can...