Related Experiment Video
Updated: Jan 26, 2026


Single Incision Plus One Port Laparoscopic Proximal Gastrectomy with Double Channel Anastomosis for Gastric Cancer Treatment
Published on: December 27, 2024
Additional gastrectomy in early-stage gastric cancer after non-curative endoscopic resection: a meta-analysis
Run-Cong Nie1,2,3, Shu-Qiang Yuan1,2,3, Yuan-Fang Li1,2,3
1Department of Gastric Surgery, Sun Yat-sen University Cancer Center, Guangzhou, Guangdong, P. R. China.

Background And Objective:
The role of additional gastrectomy after non-curative endoscopic resection remains uncertain. The present meta-analysis aimed to explore the risk factors for early-stage gastric-cancer patients after non-curative endoscopic resection and evaluate the efficacy of additional gastrectomy.
Methods:
Relevant studies that reported additional gastrectomy after non-curative endoscopic resection were comprehensively searched in MedLine, Web of Science and EMBASE. We first investigated the risk factors for residual tumor and lymph-node metastasis after non-curative endoscopic resection and then analysed the survival outcome, including 5-year overall survival (OS) and 5-year disease-free survival, of additional gastrectomy.
Results:
Twenty-one studies comprising 4870 cases were included in the present study. We found that residual tumor was associated with larger tumor size (>3 cm) (odds ratio [OR] = 2.81, P < 0.001), undifferentiated tumor type (OR = 1.78, P = 0.011) and positive horizontal margin (OR = 9.78, P < 0.001). Lymph-node metastasis was associated with larger tumor size (>3 cm) (OR = 1.73, P < 0.001), elevated tumor type (OR = 1.60, P = 0.035), deeper tumor invasion (>SM1) (OR = 2.68, P < 0.001), lymphatic invasion (OR = 4.65, P < 0.001) and positive vertical margin (OR = 2.30, P < 0.001). Patients who underwent additional gastrectomy had longer 5-year OS (hazard ratio [HR] = 0.34, P < 0.001), 5-year disease-free survival (HR = 0.52, P = 0.001) and 5-year disease-specific survival (HR = 0.50, P < 0.001) than those who did not. Moreover, elderly patients also benefited from additional gastrectomy regarding 5-year OS (HR = 0.41, P = 0.001).
Conclusions:
Additional gastrectomy with lymph-node dissection might improve the survival of early-stage gastric-cancer patients after non-curative endoscopic resection. However, risk stratification should be performed to avoid excessive treatment.
More Related Videos


Related Concept Videos
 01:27
Conjugate Addition (1,4-Addition) vs Direct Addition (1,2-Addition)
Conjugate addition results in a thermodynamically stable product. The reaction retains the stronger C=O bond at the expense of the weaker C=C π bond. The process is slow as the β carbon is less electrophilic than the carbonyl carbon.
Direct addition products are...
 01:16
Gastric Motility
Peristaltic Waves and Chyme Formation
Upon food entry, the stomach initiates...
 01:08
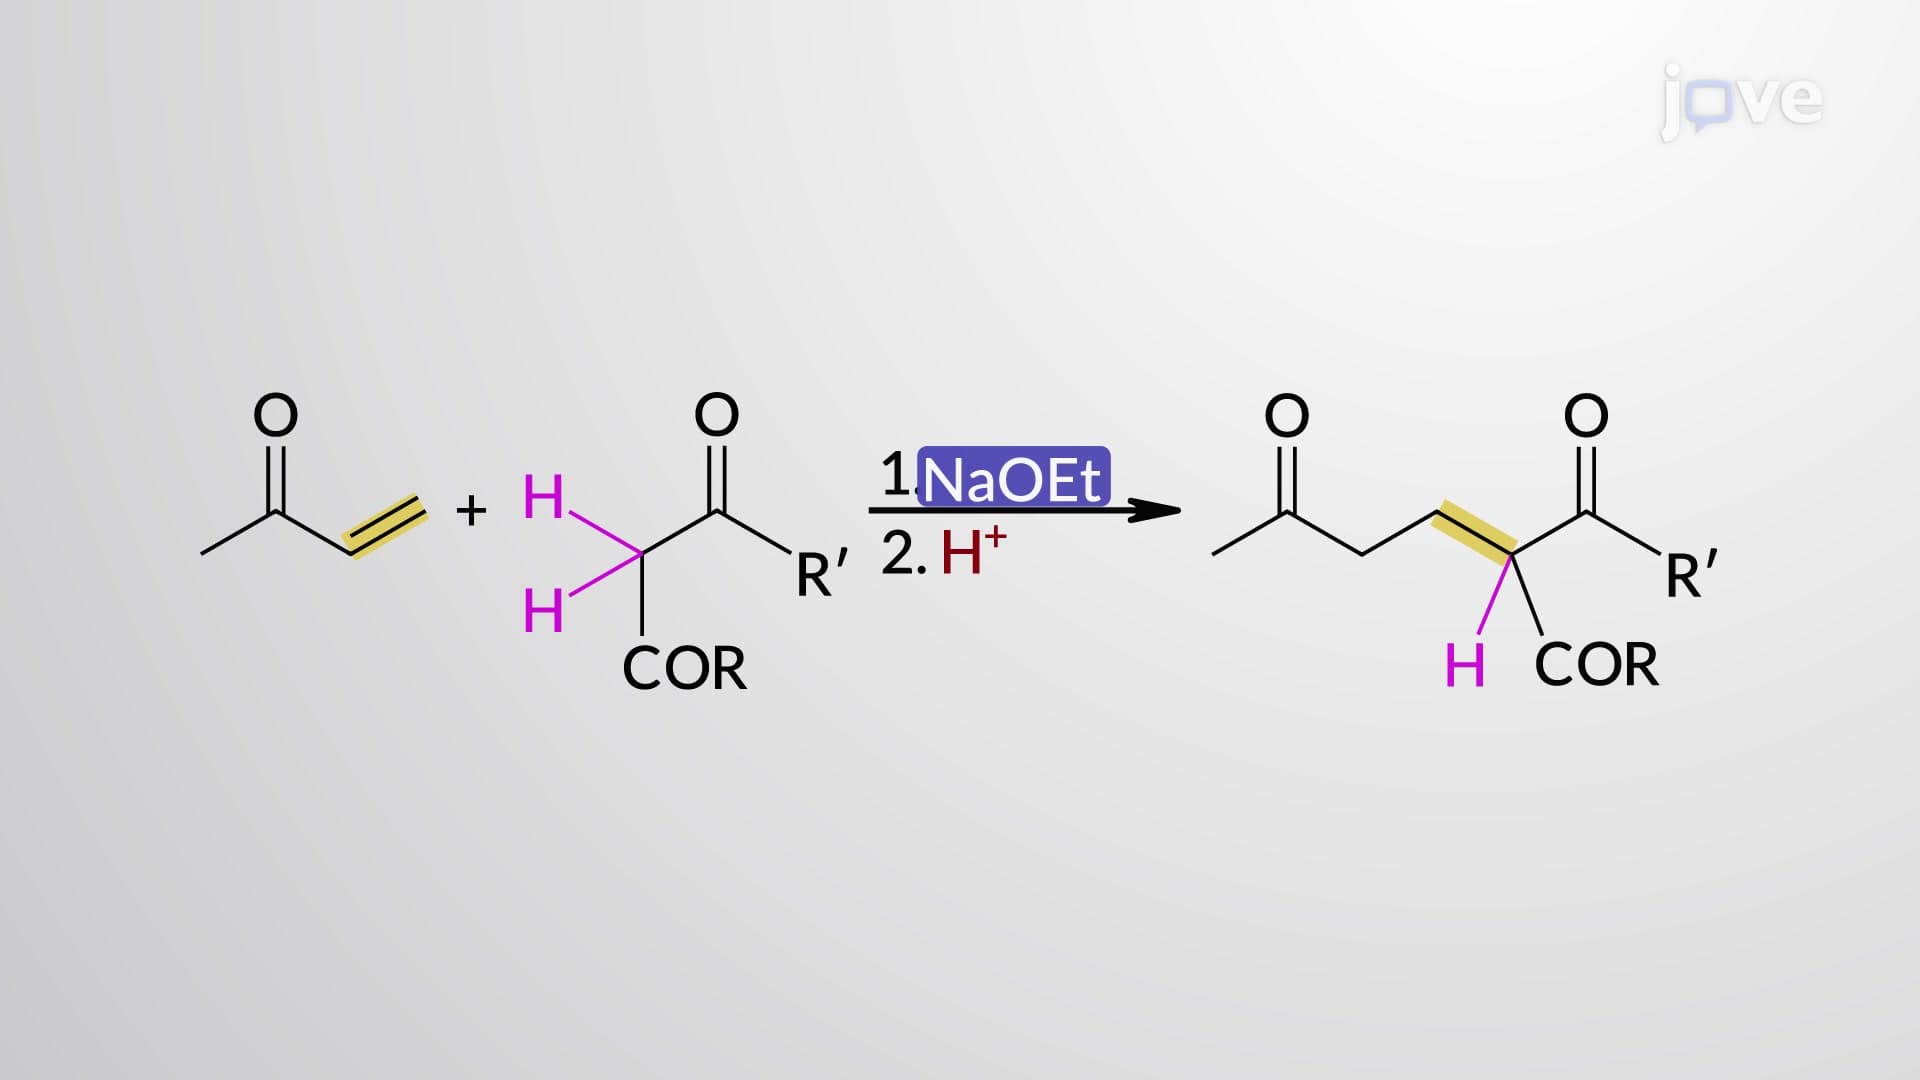
Conjugate Addition of Enolates: Michael Addition
 01:09
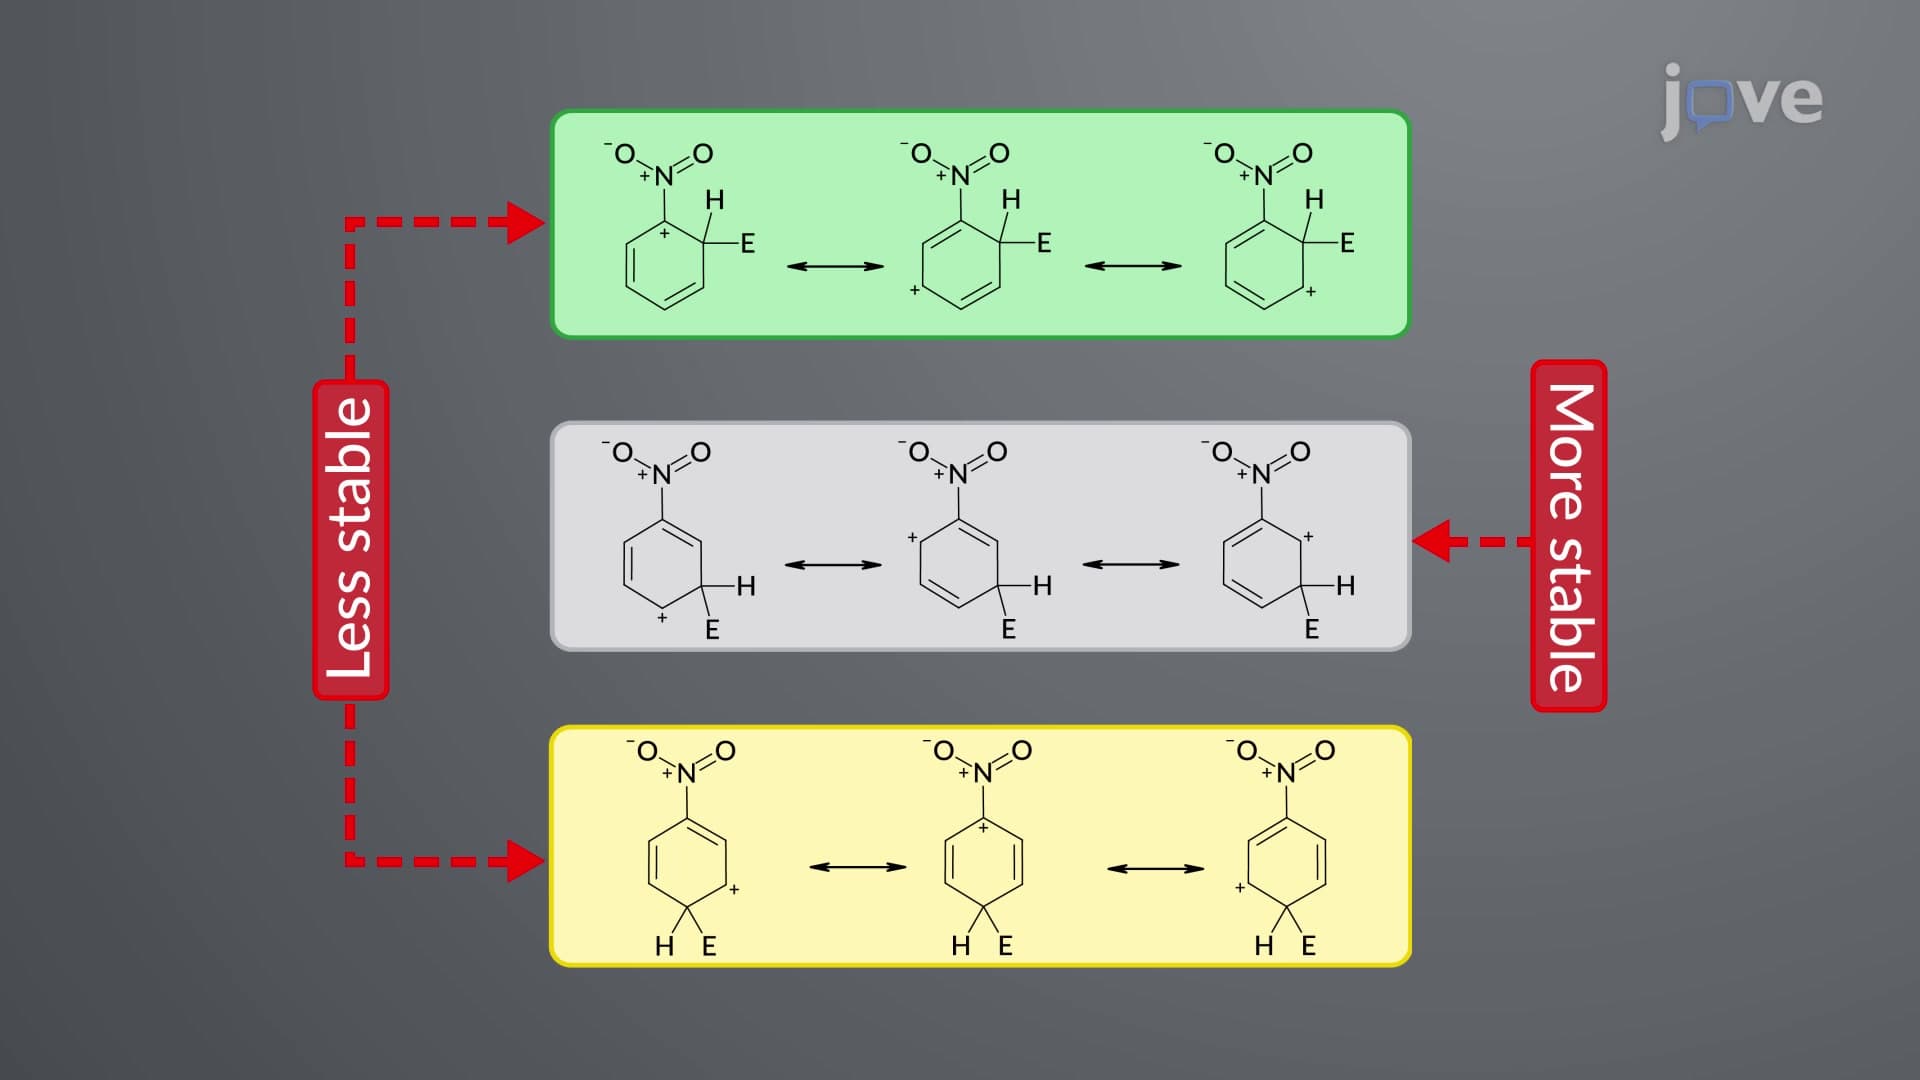
Directing Effect of Substituents: meta-Directing Groups
 02:10
Additional Subnuclear Structures
The nucleus contains many membrane-less subnuclear organelles or nuclear bodies, such as nucleoli, Cajal bodies, speckles,...
 01:21
Cancer Survival Analysis