Related Experiment Video
Updated: Jan 26, 2026
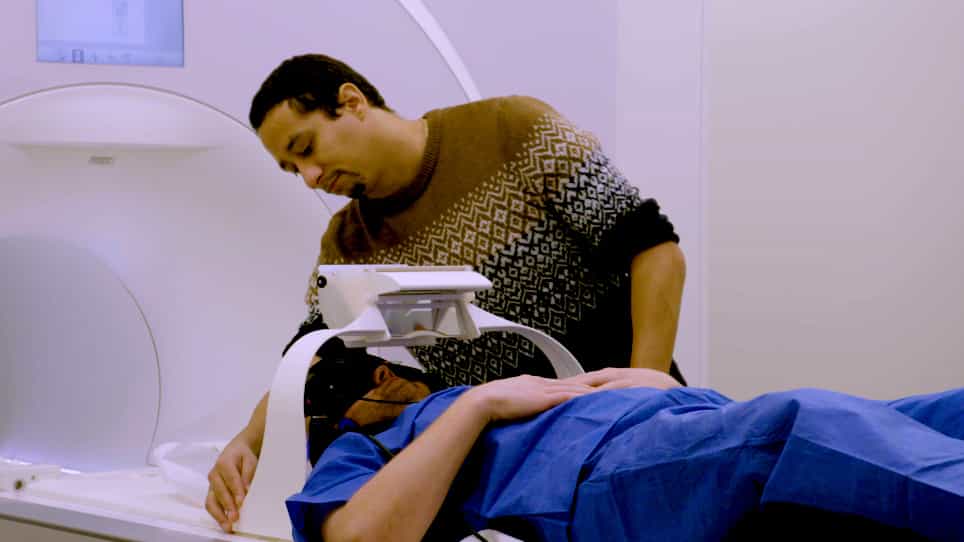

Measuring the Influence of Magnetic Vestibular Stimulation on Nystagmus, Self-Motion Perception, and Cognitive Performance in a 7T MRT
Published on: March 3, 2023
Perception of Verticality and Vestibular Disorders of Balance and Falls
Marianne Dieterich1,2,3, Thomas Brandt1,4
1German Center for Vertigo and Balance Disorders, Ludwig-Maximilians University, Munich, Germany.

Abstract:
Objective: To review current knowledge of the perception of verticality, its normal function and disorders. This is based on an integrative graviceptive input from the vertical semicircular canals and the otolith organs. Methods: The special focus is on human psychophysics, neurophysiological and imaging data on the adjustments of subjective visual vertical (SVV) and the subjective postural vertical. Furthermore, examples of mathematical modeling of specific vestibular cell functions for orientation in space in rodents and in patients are briefly presented. Results: Pathological tilts of the SVV in the roll plane are most sensitive and frequent clinical vestibular signs of unilateral lesions extending from the labyrinths via the brainstem and thalamus to the parieto-insular vestibular cortex. Due to crossings of ascending graviceptive fibers, peripheral vestibular and pontomedullary lesions cause ipsilateral tilts of the SVV; ponto-mesencephalic lesions cause contralateral tilts. In contrast, SVV tilts, which are measured in unilateral vestibular lesions at thalamic and cortical levels, have two different characteristic features: (i) they may be ipsi- or contralateral, and (ii) they are smaller than those found in lower brainstem or peripheral lesions. Motor signs such as head tilt and body lateropulsion, components of ocular tilt reaction, are typical for vestibular lesions of the peripheral vestibular organ and the pontomedullary brainstem (vestibular nucleus). They are less frequent in midbrain lesions (interstitial nucleus of Cajal) and rare in cortical lesions. Isolated body lateropulsion is chiefly found in caudal lateral medullary brainstem lesions. Vestibular function in the roll plane and its disorders can be mathematically modeled by an attractor model of angular head velocity cell and head direction cell function. Disorders manifesting with misperception of the body vertical are the pusher syndrome, the progressive supranuclear palsy, or the normal pressure hydrocephalus; they may affect roll and/or pitch plane. Conclusion: Clinical determinations of the SVV are easy and reliable. They indicate acute unilateral vestibular dysfunctions, the causative lesion of which extends from labyrinth to cortex. They allow precise topographical diagnosis of side and level in unilateral brainstem or peripheral vestibular disorders. SVV tilts may coincide with or differ from the perception of body vertical, e.g., in isolated body lateropulsion.


Related Concept Videos
 01:29
Disorder of Water Balance
Dehydration
Dehydration occurs when the body loses fluids (particularly water).
Causes:
The major causes of dehydration include excessive sweating, fever, vomiting, diarrhea, and diuresis.
Signs and Symptoms:
Symptoms primarily include intense...
 01:29
Disorders of Acid-Base Balance
Respiratory Acidosis and Alkalosis
Respiratory acidosis occurs due to an increase in the partial pressure of carbon dioxide PCO2 in the blood. It often arises from shallow breathing or impaired gas exchange caused by...
 01:05
Free-falling Bodies: Example
The...
 02:58
Balancing Redox Equations
 01:15
Subliminal Perception
 01:25
Factors Affecting Perception
An illustrative example of a perceptual set is the scenario where an airline pilot told...