Related Experiment Video
Updated: Jan 25, 2026

Occlusion of the Great and Small Saphenous Vein Using Copolymeric Glue Based on N-Butyl Cyanoacrylate and Methacryloxy Sulfolane
Published on: December 9, 2022
Ablation therapy with cyanoacrylate glue and laser for refluxing great saphenous veins - a prospective randomised
Eyüp Serhat Çalık1, Ümit Arslan1, Bilgehan Erkut1
1Ataturk University, Faculty of Medicine, Erzurum, Turkey.

Abstract:
Background: Endovenous cyanoacrylate ablation is a new technique for the treatment of clinically symptomatic venous insufficiency. The results of a prospective comparative study of cyanoacrylate glue versus endovenous laser ablation for the management of incompetent great saphenous veins are presented. Patients and methods: A total of 400 subjects were treated with cyanoacrylate ablation or endovenous laser ablation between April 2014 and April 2016. The preprocedural, procedural, postprocedural, and follow-up data were recorded and compared. Results: There were 208 procedures in cyanoacrylate ablation group (CAA) and 204 in endovenous laser ablation group (EVLA). Operative time was 13 ± 3.4 minutes in the CAA and 31.7 ± 8.8 minutes in the EVLA (< 0.001). All procedures in both groups were successful, and the target vein segments were fully occluded at the end of the procedure. Periprocedural pain was less in the CAA (< 0.001). Enduration, ecchymosis, and paresthesia rates were significantly higher in the EVLA (< 0.001). The mean length of follow-up was 14 months (range 10-16). The 3, 6 and 12 months closure rates were 97.4%, 95.6%, and 94.1% for EVLA and 98.6%, 97.1% and 96.6% for CAA respectively. In both groups, the Venous Clinical Severity Score and Chronic Venous Insufficiency Quality of Life Questionnaire with declined significantly with no difference between groups. Conclusions: Management of incompetent great saphenous veins both endovenous cyanoacrylate ablation and laser ablation results in high occlusion rates. Endovenous cyanoacrylate ablation technique is fast and simple with low periprocedural pain that does not require tumescent anesthesia and compression stockings.

Related Concept Videos
 01:26
Varicose Veins II: Diagnostic Studies and Interprofessional Care
 01:29
Gastroesophageal Reflux Disease I: Meaning and Pathophysiology
 01:17
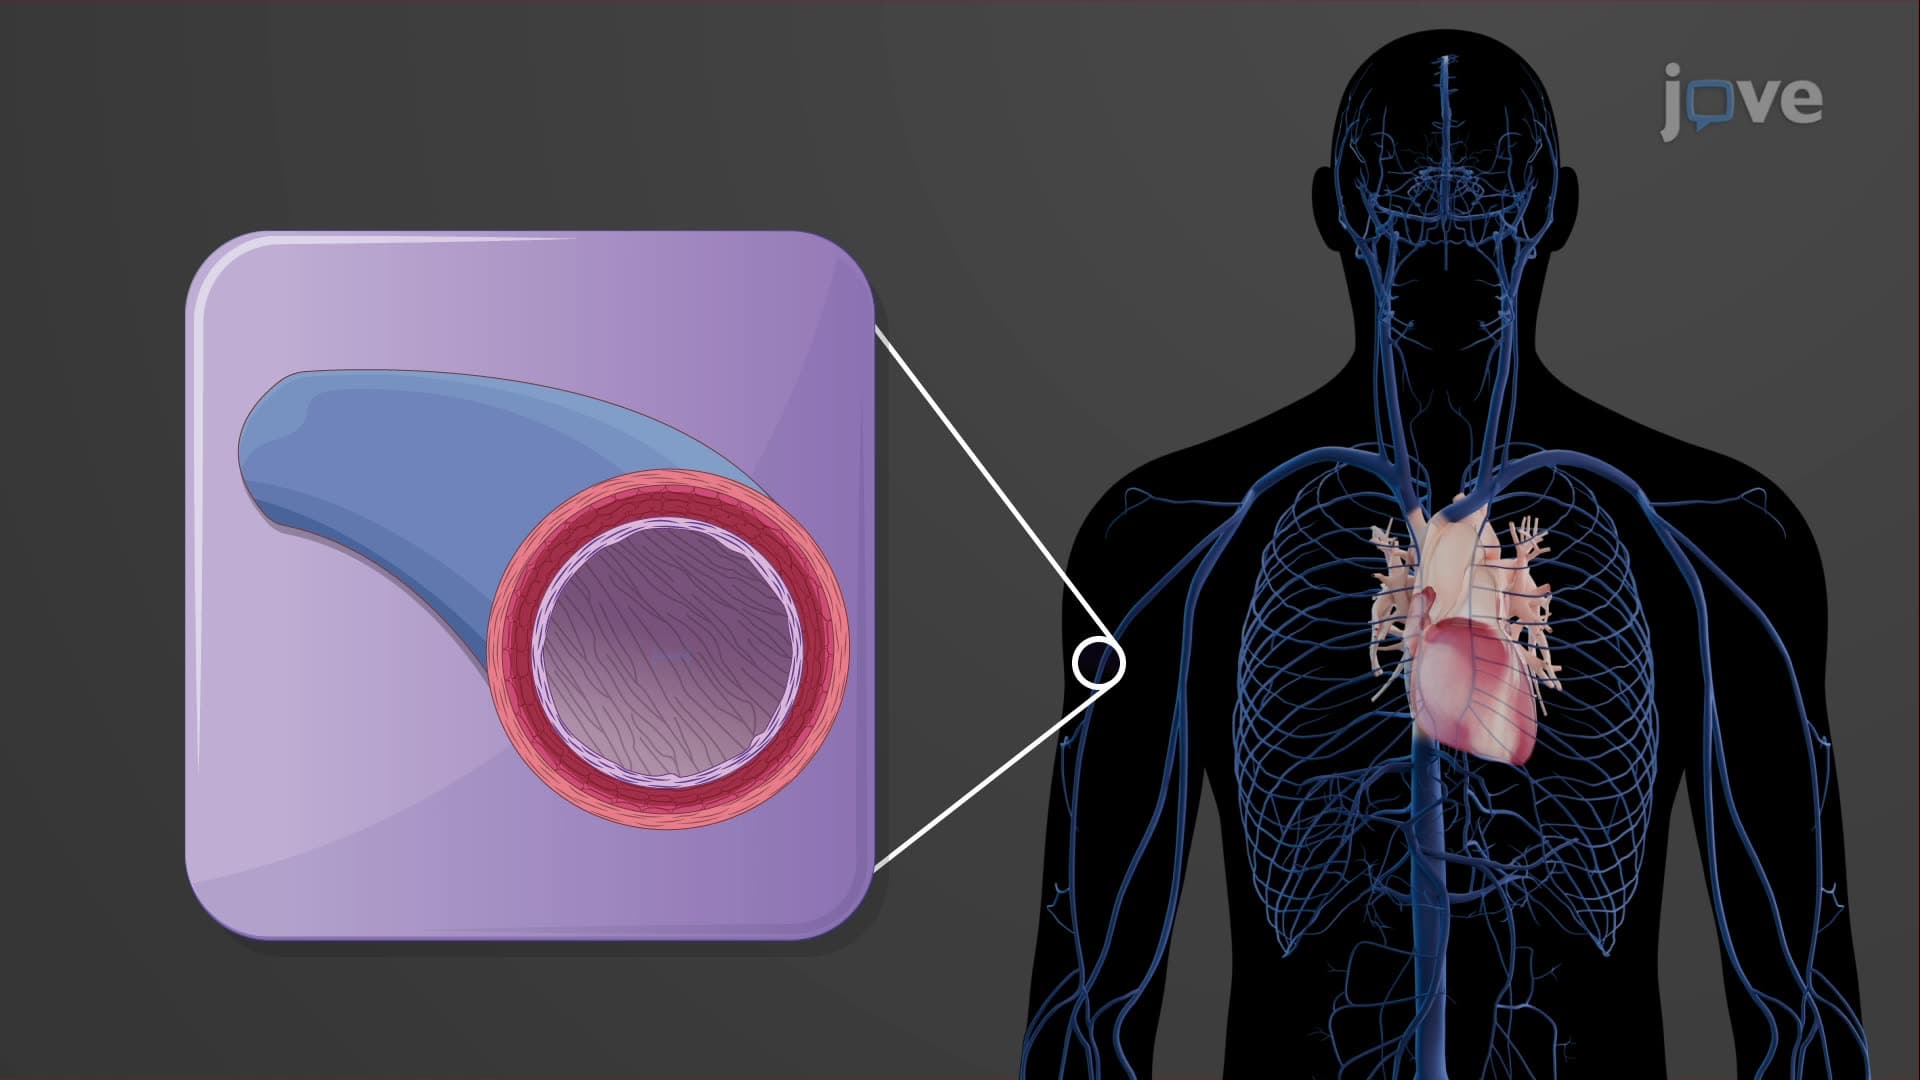
Veins
Structure of Veins:
The structure of veins is specifically designed to assist in the low-pressure transportation of...
 01:29
Gastroesophageal Reflux Disease II: Clinical Features and Management
Clinical Manifestations
GERD presents itself in a multitude of ways, with symptoms varying from person to person. The hallmark symptoms are...
 00:59
Gene Therapy
 01:19
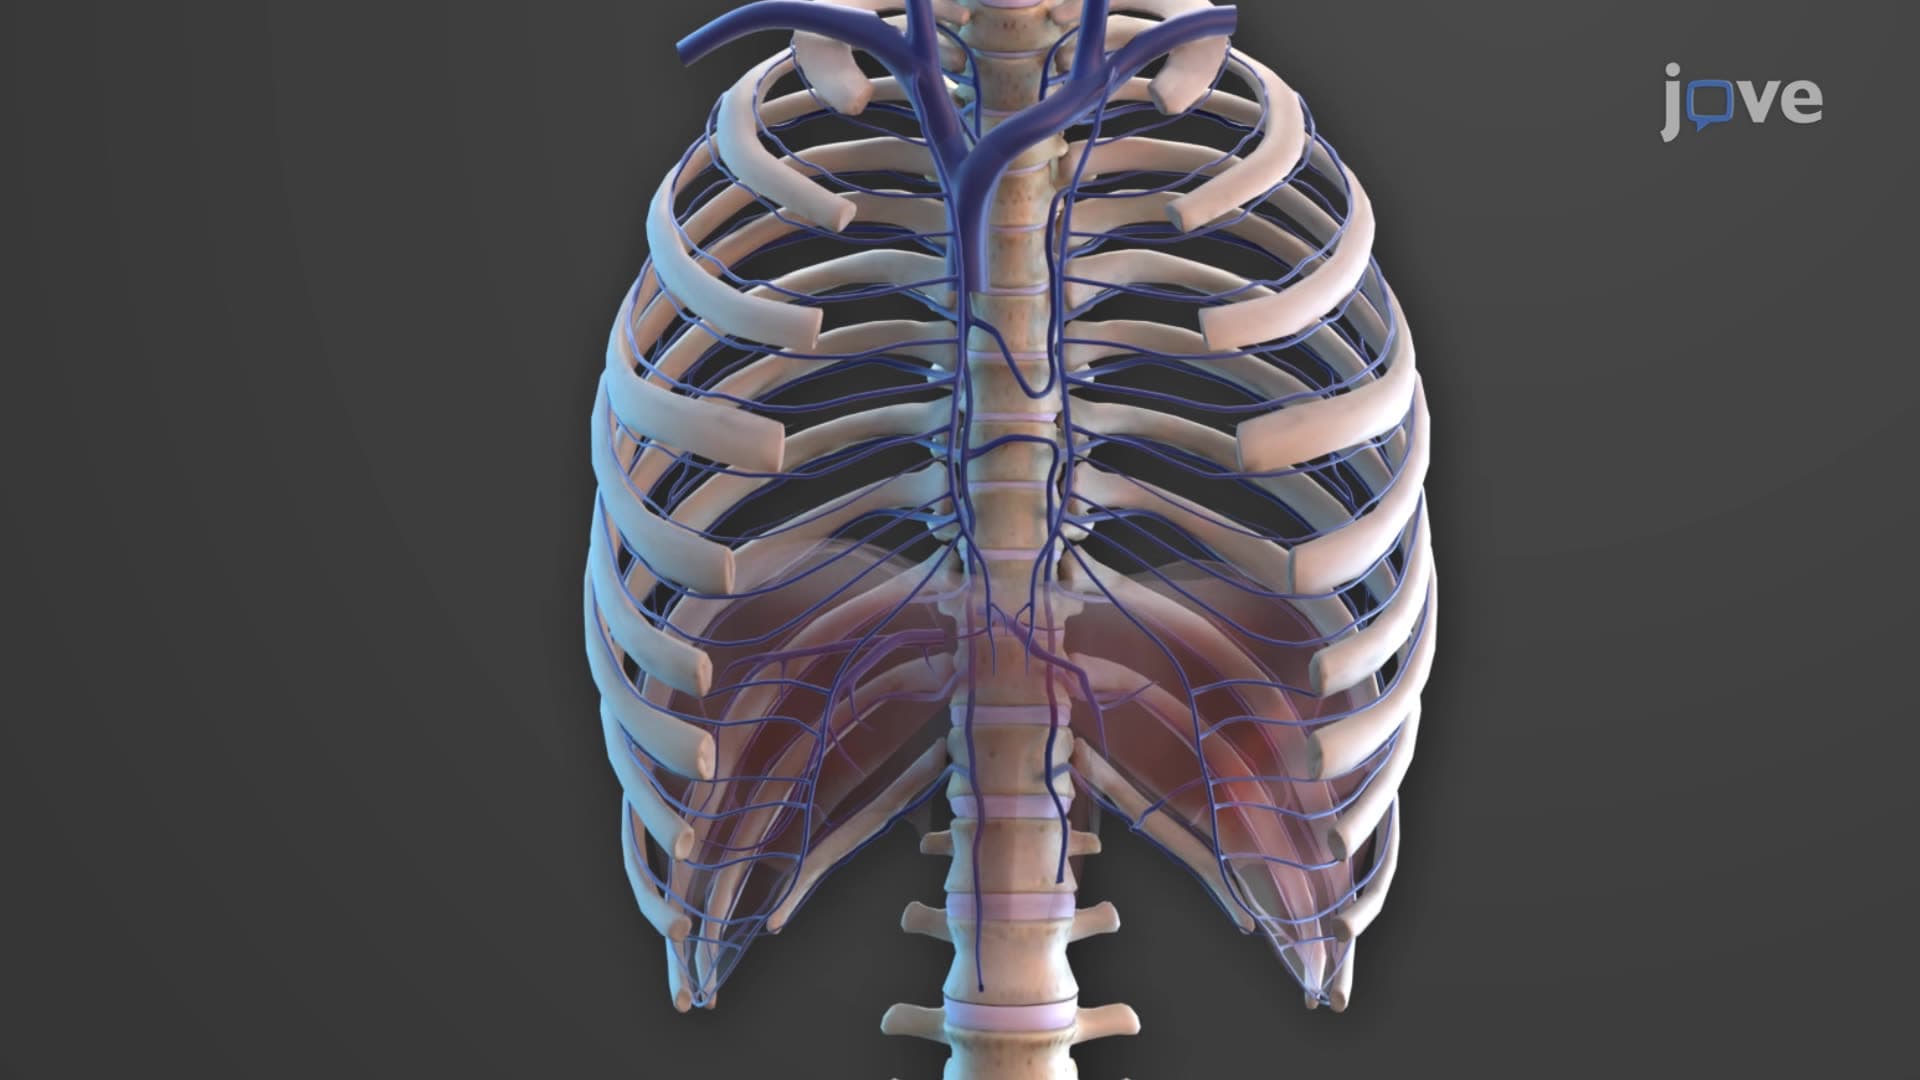
Veins of Thorax
The azygos vein, positioned just right of the midline and anterior to the vertebral column, begins at the junction of the right ascending lumbar and subcostal veins, terminating in the superior vena cava. This vein drains blood from the right side of the thoracic wall, thoracic viscera, and posterior abdominal wall.
The...