Related Experiment Video
Updated: Jan 25, 2026
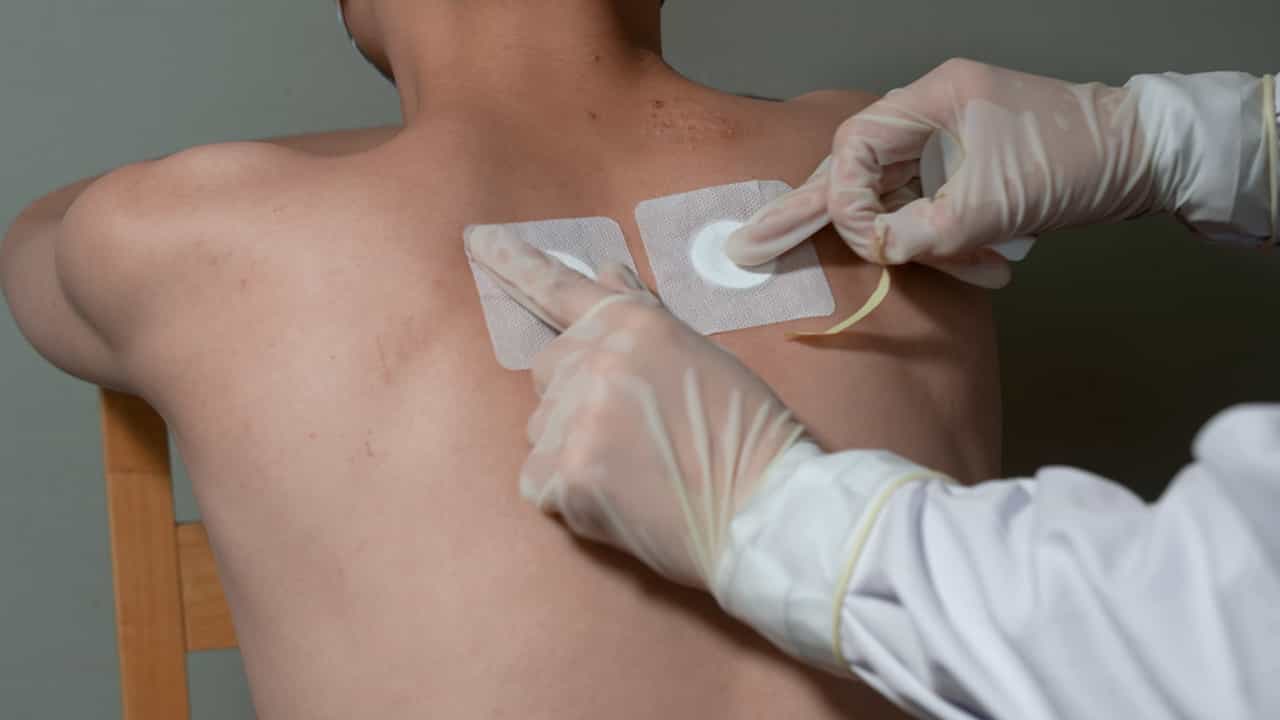

Author Spotlight: Traditional Chinese Medicine for Sleep Disorders in Acute COPD — A Safe, Cost-Effective Approach
Published on: October 18, 2024
Procalcitonin, C-reactive protein, PaCO2, and noninvasive mechanical ventilation failure in chronic obstructive
Jinrong Wang1, Huimian Shang, Xiaoya Yang
1Department of Critical Care Medicine, Harrison International Peace Hospital, Hengshui, Hebei, China.

Abstract:
It is unclear whether procalcitonin (PCT) is correlated with noninvasive ventilation (NIV) failure. This retrospective case-control study aimed to compare PCT levels, C-reactive protein (CRP) levels, and PaCO2 in patients (05/2014-03/2015 at the Harrison International Peace Hospital, China) with acute exacerbation of chronic obstructive pulmonary disease (AECOPD) and NIV failure/success.This was a retrospective case-control study of patients with AECOPD who required NIV between May 2014 and March 2015. All consecutive patients with AECOPD admitted at the Department of Critical Care Medicine and transferred from the general ward were included in the study. Hemogram, PCT, erythrocyte sedimentation rate (ESR), arterial blood gas (ABG), and CRP levels were measured ≤1 hour before NIV was used. NIV was considered to have failed if at least one of the following criteria was met: cardiac arrest or severe hemodynamic instability; respiratory arrest or gasping; mask intolerance; difficulty in clearing bronchial secretions; or worsening of ABGs or sensorium level during NIV. The factors associated with NIV failure were determined.A total of 376 patients were included: 286 with successful NIV and 90 wither NIV failure. The multivariate analysis showed that PCT (OR = 2.0, 95%CI: 1.2-3.2, P = .006), CRP (OR = 1.2, 95%CI: 1.1-1.3, P < .001), and PaCO2 (OR = 1.1, 95%CI: 1.1-1.2, P < .001) ≤1 hour before NIV were independently associated with NIV failure. The optimal cutoff were 0.31 ng/mL for PCT (sensitivity, 83.3%; specificity, 83.7%), 15.0 mg/mL for CRP (sensitivity, 75.6%; specificity, 93.0%), and 73.5 mm Hg for PaCO2 (sensitivity, 71.1%; specificity, 100%). The area under the curve (AUC) was 0.854 for PCT, 0.849 for CRP, and 0.828 for PaCO2. PCT, CRP, and PaCO2 were used to obtain a combined prediction factor, which achieved an AUC of 0.978 (95%CI: 0.961-0.995).High serum PCT, CRP, and PaCO2 levels predict NIV failure for patients with AECOPD. The combination of these three parameters might enable even more accurate prediction.

Related Concept Videos
 01:22
Chronic Obstructive Pulmonary Disease
Smoking is a primary risk factor for COPD, with over 80% of patients having a history of it. Patients typically experience progressive dyspnea or labored breathing, frequent coughing, and recurrent pulmonary infections. Many eventually succumb to respiratory failure, characterized by...
 01:20
Chronic Obstructive Pulmonary Disease-I: Introduction
 01:29
Chronic Obstructive Pulmonary Disease-V: Management
Smoking Cessation
 01:20
Chronic Obstructive Pulmonary Disease-II: Pathophysiology
Chronic Inflammation
 01:23
Mechanical Ventilation III: Noninvasive Ventilation
Noninvasive Positive-Pressure Ventilation...
 01:30
Chronic Obstructive Pulmonary Disease-V: Nursing Management
Assessment