Related Experiment Video
Updated: Jan 25, 2026


Postconditioning with Lactate-enriched Blood for Cardioprotection in ST-segment Elevation Myocardial Infarction
Published on: May 28, 2019
Efficacy of postprocedural anticoagulation after primary percutaneous coronary intervention for ST-segment elevation
Pil Sang Song1, Min Jeong Kim1, Ki-Hyun Jeon1
1Division of Cardiology, Cardiovascular Center, Mediplex Sejong General Hospital, Incheon.

Insights
Prolonged anticoagulation after primary PCI for STEMI did not significantly reduce infarct size or improve left ventricular function. Extended anticoagulation therapy offers no clear benefit over brief treatment in STEMI patients post-PCI.
Area of Science:
- Cardiology
- Interventional Cardiology
- Cardiovascular Imaging
Background:
- Controversy exists regarding the optimal duration of anticoagulation following primary percutaneous coronary intervention (PCI) for ST-elevation myocardial infarction (STEMI).
- Understanding the impact of anticoagulation duration on cardiac outcomes is crucial for patient management.
Purpose of the Study:
- To evaluate the effect of prolonged (>24 hours) versus brief (<24 hours) postprocedural anticoagulation on infarct size, left ventricular ejection fraction (LVEF), and left ventricular (LV) remodeling after primary PCI in STEMI patients.
Main Methods:
- The INNOVATION trial enrolled 114 STEMI patients undergoing primary PCI.
- Patients received either prolonged (median 72.6 hours) or brief (median 5 hours) anticoagulation.
- Infarct size was assessed by cardiac magnetic resonance (CMR) at 30 days.
- LVEF and LV remodeling were evaluated by 2D-echocardiography at 9 months.
Main Results:
- No significant differences were observed in infarct size (15.6% vs. 19.8%, P=.100) or microvascular obstruction (50.7% vs. 52.9%, P=.830) between prolonged and brief anticoagulation groups.
- Adjusted analyses did not show a reduction in larger infarcts with prolonged anticoagulation (OR: 0.435; P=.204).
- Follow-up LVEF and LV remodeling rates were similar between the groups (LVEF <35%: 3.2% vs. 7.4%, P=.352; LV remodeling: 37.1% vs. 18.5%, P=.234).
Conclusions:
- Prolonged postprocedural anticoagulation does not appear to offer significant benefits in terms of infarct size, LVEF, or LV remodeling after successful primary PCI in STEMI patients.
- These findings suggest that brief anticoagulation may be sufficient, challenging current practices.
- Further research is warranted to confirm these results and refine anticoagulation strategies in STEMI management.
Abstract:
There exists controversy on whether and for how long anticoagulation is necessary after primary percutaneous coronary intervention (PCI) for ST-segment elevation myocardial infarction (STEMI).We aimed to study the impact of prolonged (>24 h) or brief (<24 h) postprocedural anticoagulation on infarct size assessed by cardiac magnetic resonance (CMR) after 30 days as well as on left ventricular ejection fraction (LVEF) and left ventricular (LV) remodeling evaluated by 2D-echocardiography after 9 months from the INNOVATION trial (Clinical Trial Registration: NCT02324348).Of the 114 patients (mean age: 59.5 years) enrolled, 76 (66.7%) received prolonged anticoagulation therapy (median duration: 72.6 h) and 38 (33.3%) patients received brief anticoagulation therapy (median duration: 5 h) after primary PCI. There was no significant difference in infarct size (mean size: 15.6% after prolonged anticoagulation versus 19.8% after brief anticoagulation, P = .100) and the incidence of microvascular obstruction (50.7% versus 52.9%, P = .830) between the groups. Even after adjusting, prolonged anticoagulation therapy could not reduce larger infarct (defined as >75 percentile of infarct size; 19.7% versus 35.3%; adjusted odd ratio [OR]: 0.435; 95% confidence interval [CI]: 0.120-1.57; P = .204). Similar results were observed in subanalyses of major high-risk subgroups. Moreover, follow-up LVEF <35% (3.2% versus 7.4%; adjusted OR: 0.383; 95% CI: 0.051-2.884; P = .352) and LV remodeling (defined as >20% increase in LV end-diastolic volume; 37.1% versus 18.5%; adjusted OR: 2.249; 95% CI: 0.593-8.535; P = .234) were similar between groups.These data suggest that prolonged postprocedural anticoagulation may not provide much benefit after successful primary PCI in patients with STEMI. However, further studies are needed.


Related Concept Videos
 01:18
Anticoagulant Drugs: Vitamin K Antagonists and Direct Oral Anticoagulants
Warfarin, a prominent vitamin K antagonist family member, exerts its effect by inhibiting the enzyme VKORC1 (vitamin K epoxide reductase complex 1). By hindering this enzyme, warfarin...
 03:12
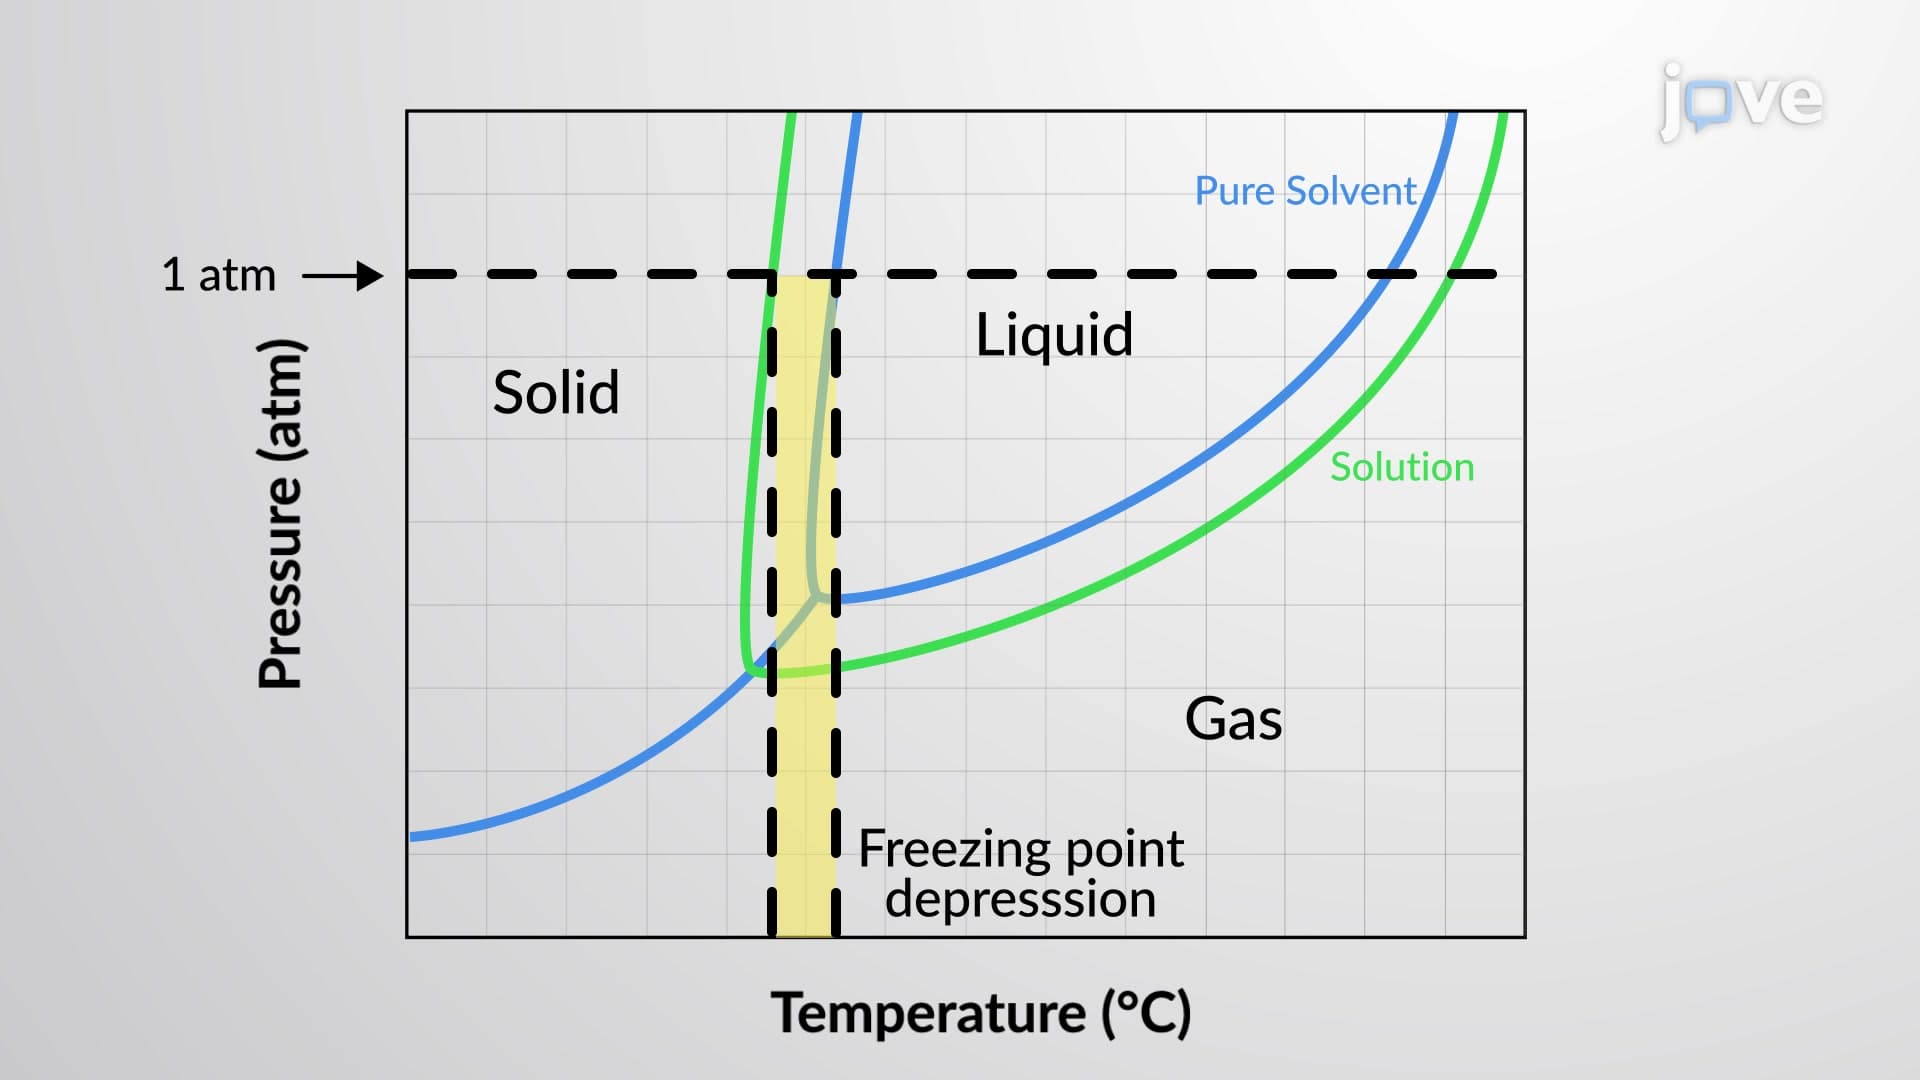
Freezing Point Depression and Boiling Point Elevation
The boiling point of a liquid is the temperature at which its vapor pressure is equal to ambient atmospheric pressure. Since the vapor pressure of a solution is lowered due to the presence of nonvolatile solutes, it stands to reason that the solution’s boiling point will subsequently be increased. Vapor pressure increases with temperature, and so a solution will require a higher temperature than will pure solvent to achieve any given vapor pressure, including one...
 01:12
Statistical Software for Data Analysis and Clinical Trials
 01:03
Nursing Interventions I: Taxonomy of Nursing Interventions
A nursing intervention is a treatment or action based on scientific concepts and knowledge from the nursing, behavioral, and physical sciences. Identifying and prioritizing nursing interventions based on the desired outcome...
 01:16
Clinical Trials
There are four phases in a clinical trial. A phase one...
 01:11
Clinical Trials: Overview