Related Experiment Video
Updated: Jan 25, 2026
Measurements of Motor Function and Other Clinical Outcome Parameters in Ambulant Children with Duchenne Muscular Dystrophy
Published on: January 12, 2019
Clinical Profile, Response to Therapy, and Outcome of Children with Primary Intestinal Lymphangiectasia
Durga Prasad1, Anshu Srivastava2, Anil Tambe1
1Department of Pediatric Gastroenterology, Sanjay Gandhi Postgraduate Institute of Medical Sciences, Lucknow, India.

Insights
Primary intestinal lymphangiectasia (PIL) in children often presents with edema and diarrhea. Most children improve with dietary therapy, but chylous ascites indicates severe disease requiring close monitoring for relapse and complications.
Area of Science:
- Pediatric Gastroenterology
- Gastrointestinal Motility Disorders
- Gastrointestinal Oncology
Background:
- Intestinal lymphangiectasia (IL) is a significant cause of protein-losing enteropathy.
- Primary IL (PIL) diagnosis and management in children require careful evaluation of clinical and laboratory profiles.
Purpose of the Study:
- To evaluate the clinical and laboratory characteristics of children diagnosed with primary intestinal lymphangiectasia (PIL).
- To assess the response to therapy, complications, and outcomes in pediatric patients with PIL.
Main Methods:
- A retrospective analysis of consecutive children (≤18 years) diagnosed with PIL between 2007 and 2017.
- Diagnosis was confirmed via small bowel histopathology, excluding secondary causes of IL.
Main Results:
- Twenty-eight children with PIL presented with pedal edema (93%), chronic diarrhea (78.6%), and ascites (64%).
- Hypoproteinemia, hypoalbuminemia, and hypocalcemia were common laboratory findings.
- Chylous ascites was associated with more severe disease, including lymphedema and pleural effusion, and a higher need for additional therapy.
Conclusions:
- Dietary therapy is effective for the majority of children with PIL, with only 20% requiring additional interventions.
- Chylous ascites signifies a more severe disease presentation in pediatric PIL.
- Long-term follow-up is crucial for monitoring symptom recurrence and potential complications such as Budd Chiari Syndrome and lymphoma.
Objective:
Intestinal lymphangiectasia (IL; primary or secondary) is an important cause of protein-losing enteropathy. We evaluated the clinicolaboratory profile, response to therapy, complications, and outcome of children with primary IL (PIL).
Methods:
Consecutive children (≤18 years) diagnosed with PIL (clinical setting, typical small bowel histopathology, and exclusion of secondary causes) from 2007 to 2017 were evaluated.
Results:
Twenty-eight children with PIL (16 boys, age at symptom onset-12 [1-192] months and at diagnosis 8 [1-18] years) were studied. Pedal edema (93%), chronic diarrhea (78.6%), and recurrent anasarca (64%) were the common presentations. Ascites, pleural, and pericardial effusion were seen in 64 (n-18; chylous-5, non-chylous-13), 18, and 18% cases, respectively. Hypoproteinemia, hypoalbuminemia, hypocalcemia, and lymphopenia were present in 82, 82, 75 and 39% cases, respectively. Duodenal biopsy established the diagnosis in 86% cases, while 14% required distal small bowel biopsies. Dietary therapy was given in all and 6 cases required additional therapy (octreotide-6, tranexamic acid-3, and total parenteral nutrition-1). Lymphedema (3/5 vs. 1/23), pleural effusion (4/5 vs. 1/23), and the need for additional therapy (4/5 vs. 2/23) were significantly more in patients with chylous ascites (n = 5) than those without chylous ascites (n = 23). Twenty-four cases in follow-up (39 [6-120] months) showed improvement; however, 8 required readmission (symptom recurrence-6 [25%], complication-2 [8.3%], Budd Chiari Syndrome-1, and abdominal B cell lymphoma-1).
Conclusion:
Presence of chylous ascites suggests severe disease in children with PIL. Majority of PIL children respond to dietary therapy; only 20% need additional therapy. Long-term follow-up is essential to monitor for symptoms relapse and complications.
More Related Videos
Related Concept Videos
 01:23
Anatomy of the Intestines
Small Intestines
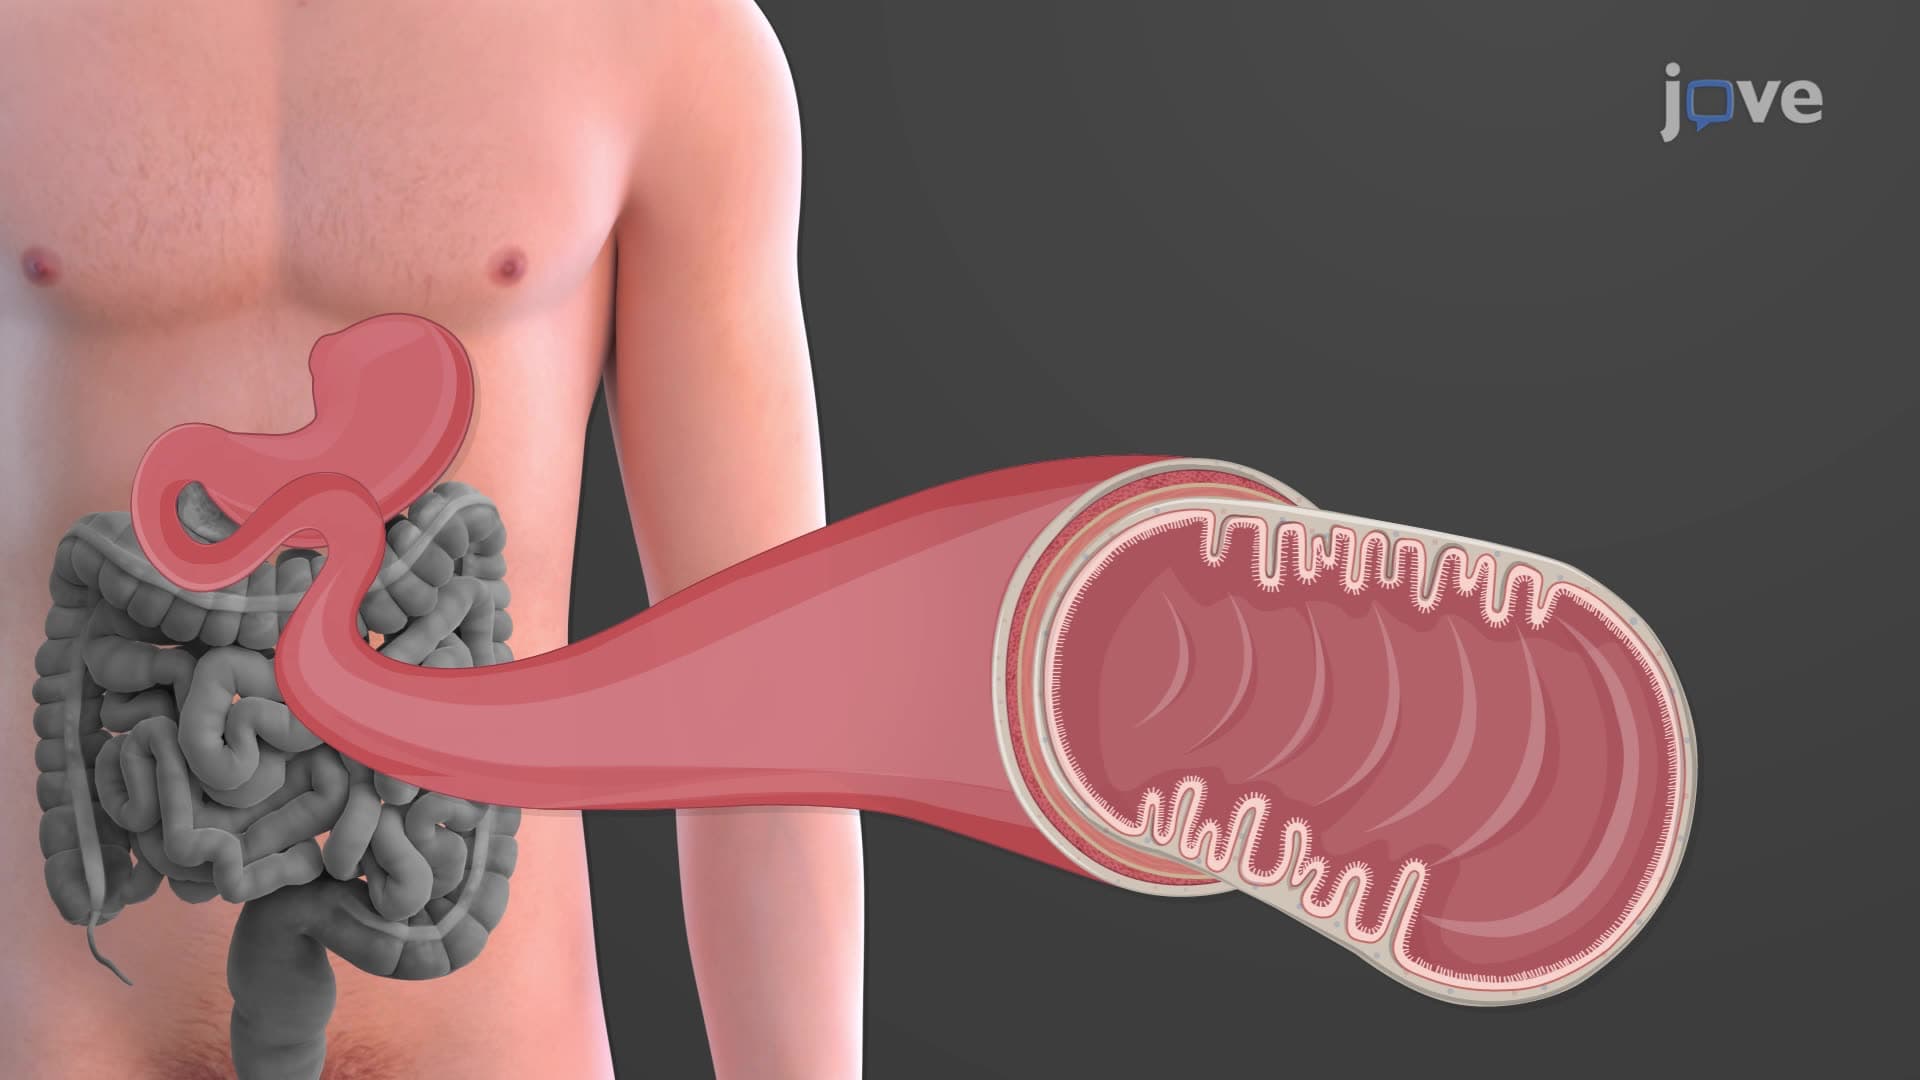
The small intestine is an ~7 meter-long tube with an inner diameter of just 2.5 cm. Since most nutrients are absorbed here, the inner lining of the...
 02:24
Predicting Reaction Outcomes
 01:13
Outcomes of Glycolysis
Cellular respiration can occur aerobically (with oxygen) or anaerobically (without oxygen). In the presence of oxygen, cellular respiration starts with glycolysis and continues with pyruvate...
 01:11
Guidelines for Writing Outcome
Patient outcomes reflect the patient's response to the goal rather than what the nurse aims to achieve. Terminology should be observable and measurable to avoid the reader's interpretation. The desired outcome should be realistic and achievable in the designated care timeframe. Expected outcomes should align with adjunctive therapies. The outcome should enhance care...
 00:59
Gene Therapy
 01:15
Small Intestine
The small intestine is divided into three main sections - the duodenum, jejunum, and ileum. The duodenum, approximately 25 cm long, is nearest the stomach. It acts as a 'mixing bowl,' where chyme (partially digested food) blends with digestive enzymes from the pancreas and liver. The duodenum's unique...