Related Experiment Video
Updated: Jan 25, 2026
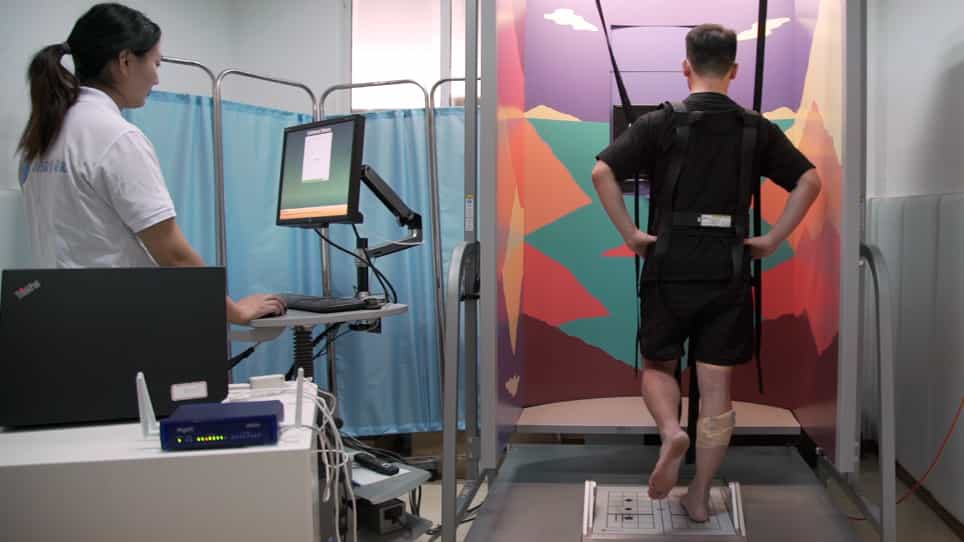

Evaluating Postural Control and Lower-extremity Muscle Activation in Individuals with Chronic Ankle Instability
Published on: September 18, 2020
Altered movement strategies during jump landing/cutting in patients with chronic ankle instability
Hyunsoo Kim1, Seong Jun Son2, Matthew Kirk Seeley3
1Department of Kinesiology, West Chester University, West Chester, Pennsylvania.

Abstract:
Centrally mediated changes in sensorimotor function have been reported in patients with chronic ankle instability (CAI). However, little is known regarding supraspinal/spinal adaptations during lower-extremity dynamic movement during a multiplanar, single-leg landing/cutting task. The purpose of this study was to investigate the effect of CAI on landing/cutting neuromechanics, including lower-extremity kinematic, electromyography (EMG) activation, and ground reaction force (GRF) characteristics. One hundred CAI patients and 100 matched healthy controls performed five trials of a jump landing/cutting task. Sagittal- and frontal-plane ankle, knee and hip kinematics, EMG activation in eight lower-extremity muscles, and 3D GRF were collected during jump landing/cutting. Functional analyses of variance (FANOVA) were used to evaluate between-group differences for dependent variables throughout the entire ground contact of the task. Relative to the control group, the CAI group revealed (a) reduced dorsiflexion, increased knee and hip flexion angles, (b) increased inversion and hip adduction angles, (c) increased EMG activation of medial gastrocnemius, peroneus longus, adductor longus, vastus lateralis, gluteus medius, and gluteus maximus, and (d) increased posterior and vertical GRF during initial landing, and reduced medial, posterior, and vertical GRF during mid-landing and mid-cutting. CAI patients demonstrated alterations in landing/cutting movement strategies as demonstrated by a higher susceptibility of foot placement for lateral ankle sprains, and more flexed positions of the knee and hip with higher EMG activation of knee and hip extensors to modulate GRF to compensate for the unstable ankle. This apparent compensation may be due to mechanical (limited dorsiflexion angle) and/or sensorimotor deficits in the ankle.


Related Concept Videos
 02:22
The Colonization of Land
 01:10
Ankle Joint
 02:17
Microtubule Instability
 01:16
Hydraulic Jump: Problem Solving
 01:29
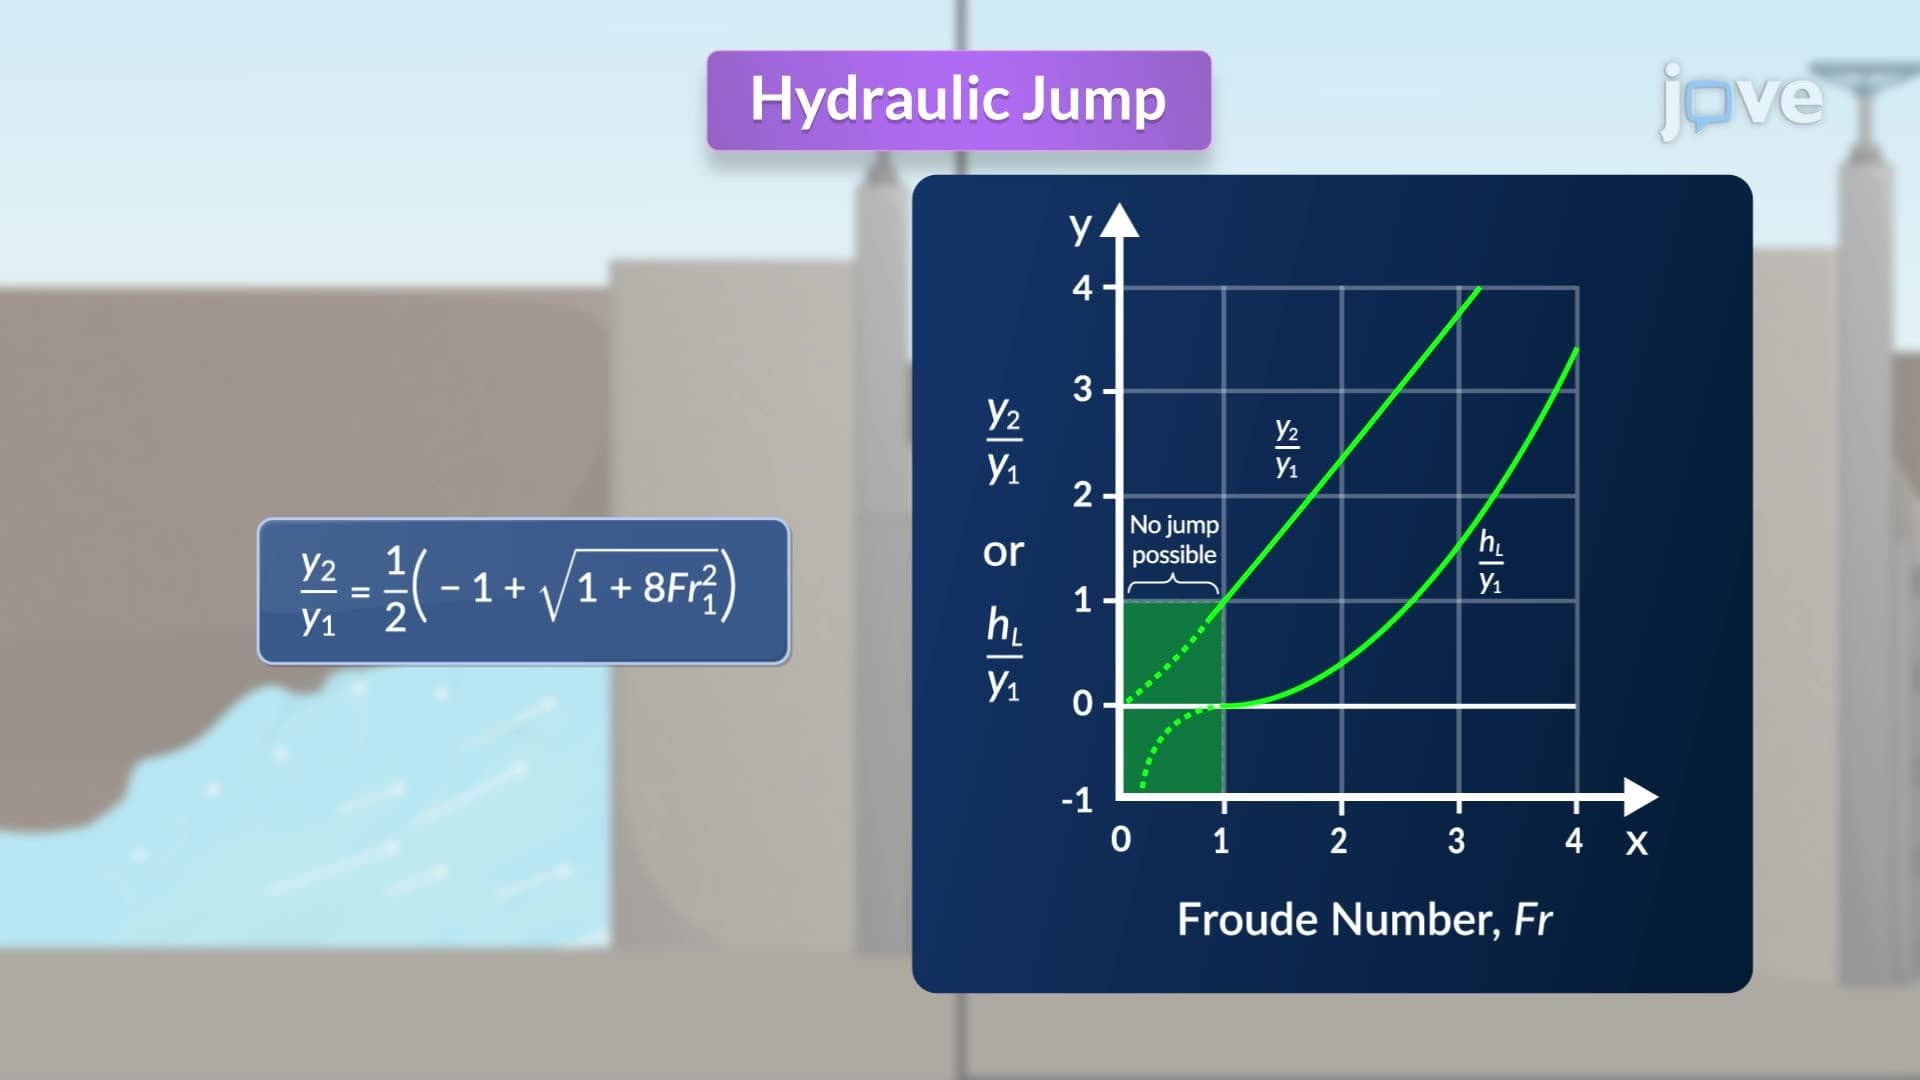
Hydraulic Jump
 01:30
Alterations in Respiration II
In Biot's breathing, the respiratory rate and depth are irregular, alternating between periods of deep gasping and apnea. Common causes...