Related Experiment Video
Updated: Jan 25, 2026


Neuronavigation and Laparoscopy Guided Ventriculoperitoneal Shunt Insertion for the Treatment of Hydrocephalus
Published on: October 14, 2022
Risk Factors and Preoperative Risk Scoring System for Shunt-Dependent Hydrocephalus Following Aneurysmal Subarachnoid
Joo Hyun Kim1, Jae Hoon Kim1, Hee In Kang1
1Department of Neurosurgery, Eulji University Eulji Hospital, Seoul, South Korea.

Objective:
Shunt-dependent hydrocephalus (SdHCP) is a well-known complication of aneurysmal subarachnoid hemorrhage (SAH). The risk factors for SdHCP have been widely investigated, but few risk scoring systems have been established to predict SdHCP. This study was performed to investigate the risk factors for SdHCP and devise a risk scoring system for use before aneurysm obliteration.
Methods:
We reviewed the data of 301 consecutive patients who underwent aneurysm obliteration following SAH from September 2007 to December 2016. The exclusion criteria for this study were previous aneurysm obliteration, previous major cerebral infarction, the presence of a cavum septum pellucidum, a midline shift of >10 mm on initial computed tomography (CT), and in-hospital mortality. We finally recruited 254 patients and analyzed the following data according to the presence or absence of SdHCP : age, sex, history of hypertension and diabetes mellitus, Hunt-Hess grade, Fisher grade, aneurysm size and location, type of treatment, bicaudate index on initial CT, intraventricular hemorrhage, cerebrospinal fluid drainage, vasospasm, and modified Rankin scale score at discharge.
Results:
In the multivariate analysis, acute HCP (bicaudate index of ≥0.2) (odds ratio [OR], 6.749; 95% confidence interval [CI], 2.843-16.021; p=0.000), Fisher grade of 4 (OR, 4.108; 95% CI, 1.044-16.169; p=0.043), and an age of ≥50 years (OR, 3.938; 95% CI, 1.375-11.275; p=0.011) were significantly associated with the occurrence of SdHCP. The risk scoring system using above parameters of acute HCP, Fisher grade, and age (AFA score) assigned 1 point to each (total score of 0-3 points). SdHCP occurred in 4.3% of patients with a score of 0, 8.5% with a score of 1, 25.5% with a score of 2, and 61.7% with a score of 3 (p=0.000). In the receiver operating characteristic curve analysis, the area under the curve (AUC) for the risk scoring system was 0.820 (p=0.080; 95% CI, 0.750-0.890). In the internal validation of the risk scoring system, the score reliably predicted SdHCP (AUC, 0.895; p=0.000; 95% CI, 0.847-0.943).
Conclusion:
Our results suggest that the herein-described AFA score is a useful tool for predicting SdHCP before aneurysm obliteration. Prospective validation is needed.
Related Concept Videos
 01:26
Factors Affecting the Risk of Infection
The integrity and count of the white blood cells help the body resist pathogens and fight infection. When impaired, it reduces the body's resistance to pathogens. The acidic pH levels of the gastrointestinal, genitourinary tracts, and skin...
 01:12
Relative Risk
 01:17
Design Example: Analyzing Capacity Contours for Flood Risk Assessment
 01:26
Shunt Admittances
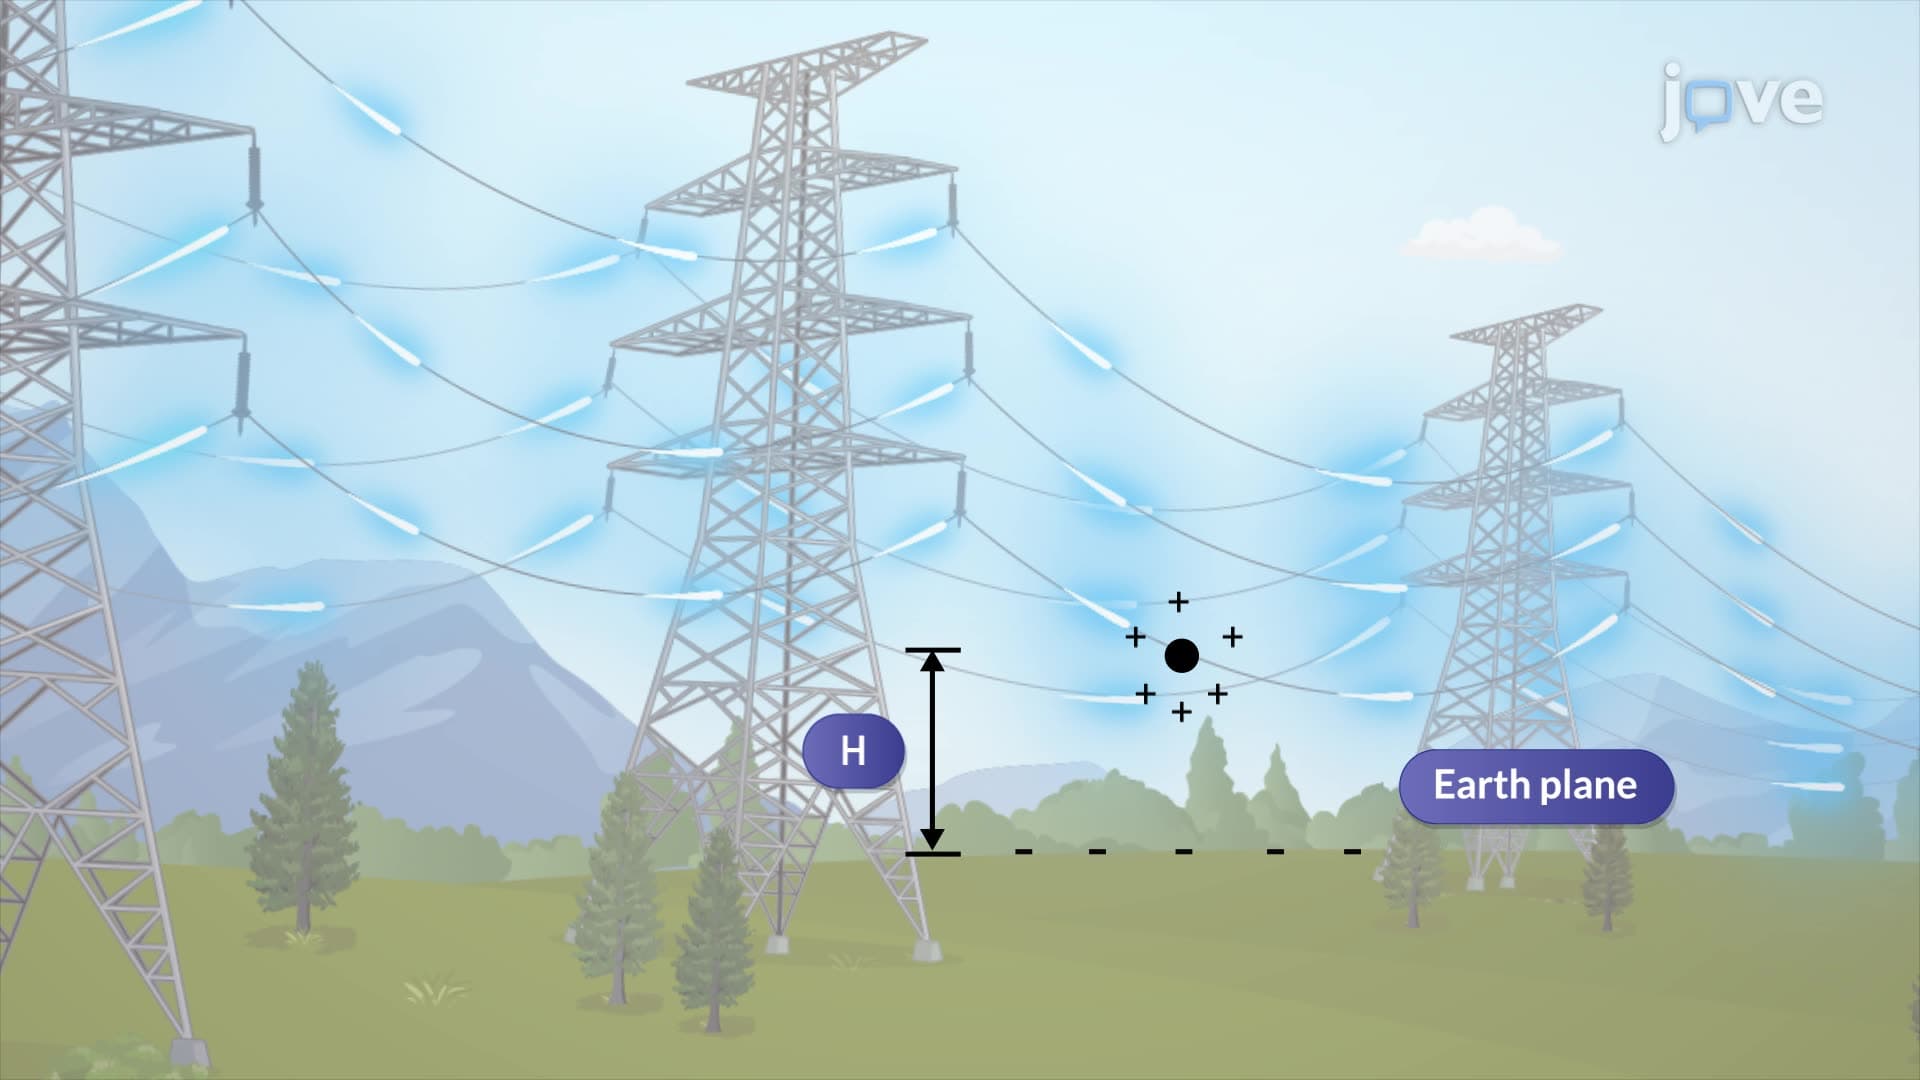
To model this effect, the method of images is employed. This method involves replacing the Earth with an image conductor that mirrors the original...
 01:06
Introduction to z Scores
z scores...
 01:05
Introduction to z Scores
z scores...