
Cirrhotic Cardiomyopathy: The Interplay Between Liver and Cardiac Muscle. How Does the Cardiovascular System React
Spyros P Dourakis1, Eleni Geladari2, Charalampia Geladari2
12nd Department of Internal Medicine and Research Laboratory, Medical School, National and Kapodistrian University of Athens, Hippokration Hospital, Athens, Greece.

Insights
Cirrhotic cardiomyopathy (CCM) involves heart dysfunction in liver cirrhosis patients due to hemodynamic changes. Understanding CCM is crucial for better diagnosis and treatment to prevent complications like heart failure.
Area of Science:
- Cardiology
- Hepatology
- Internal Medicine
Background:
- Liver cirrhosis causes significant hemodynamic alterations, including hyperdynamic circulation and reduced systemic vascular resistance.
- These changes can lead to systolic and diastolic dysfunction, and rhythm disturbances, collectively termed cirrhotic cardiomyopathy (CCM).
- CCM is distinct from alcoholic cardiomyopathy and affects patients without prior cardiac conditions.
Purpose of the Study:
- To comprehensively review the cardiovascular pathological alterations in cirrhotic patients.
- To highlight diagnostic and treatment limitations for CCM.
- To emphasize the need for increased clinical vigilance regarding CCM's impact.
Main Methods:
- Review of existing literature on the pathophysiology and clinical significance of CCM.
- Analysis of diagnostic tools such as electrocardiography, echocardiography, and serum biomarkers.
- Discussion of clinical implications and potential complications.
Main Results:
- CCM is characterized by blunted contractile responsiveness, impaired diastolic relaxation, and QT interval prolongation.
- CCM can precipitate heart failure during procedures like TIPS and liver transplantation.
- CCM is implicated as a factor in hepatorenal syndrome development.
Conclusions:
- Current treatment for CCM is integrated with that for liver cirrhosis and heart failure, lacking specific CCM therapies.
- A deeper understanding of CCM pathophysiology is essential for developing targeted diagnostic tools and treatments.
- Clinicians must enhance observation and recording of cardiovascular changes in cirrhotic patients.
Abstract:
It is widely known that liver cirrhosis, regardless of the etiologies is accompanied by severe hemodynamic changes. The principal pathophysiological mechanisms are the hyperdynamic circulation with increased cardiac output, heart rate along with reduced systemic vascular resistance. Thus, counteractive mechanisms may develop that eventually lead to systolic as well as diastolic dysfunction and rhythm disturbances, in order to keep a steady homeostasis in the human body. Literally, blunted contractile responsiveness to physical or pharmacological stress, impaired diastolic relaxation and electrophysiological changes, primarily QT interval prolongation, do occur progressively in a cirrhotic patient with no known preexisting cardiac disease. This condition is identified as cirrhotic cardiomyopathy (CCM), an entity different from that seen in alcoholic cardiac muscle disease. For the past decades, clinicians did study and attempt to understand the pathophysiology and clinical significance of this process. Indeed, various factors have been identified acting at the molecular and cellular level. Electrocardiography, echocardiography and various serum biomarkers are the main tools that help healthcare practitioners to point to the correct diagnosis. Noteworthy, the subjects that suffer from cirrhotic cardiomyopathy may progress to heart failure during invasive procedures such as surgery, insertion of a transjugular intrahepatic portosystemic shunting (TIPS) and liver transplantation. Besides, several studies have illustrated that CCM is a contributing factor, or even a precipitant, of hepatorenal syndrome (HRS), a conceivable reversible kidney failure in patients with liver cirrhosis and ascites. The treatment is the same as it is in the patients with liver cirrhosis and heart failure and there is no particular treatment for cirrhotic cardiomyopathy. Hence, it is of utmost importance to clearly comprehend the pathophysiology of this disease in order to design more accurate diagnostic tools and definitive treatments in a way to prevent the complications of cirrhosis and overt heart failure. The objective of this review is to describe in a comprehensive way the pathological alterations that occur in the cardiovascular system of cirrhotic patients. It will also point the limitations that remain in the diagnosis and treatment strategies and more importantly, this review will alert the clinicians in the modern era to further observe and record additional pathological changes in this subset of patients.


Related Concept Videos
 01:26
Diseases of the Liver and Gallbladder
Cirrhosis is characterized by the scarring of hepatic lobules in the liver, which are replaced by fibrous tissue, affecting the liver's normal functioning. NAFLD, on the other hand, is caused by an excessive build-up of fat in the liver, not...
 01:22
Effect of Hepatic Disease on Pharmacokinetics: Pathophysiologic Assessment and Liver Function Test
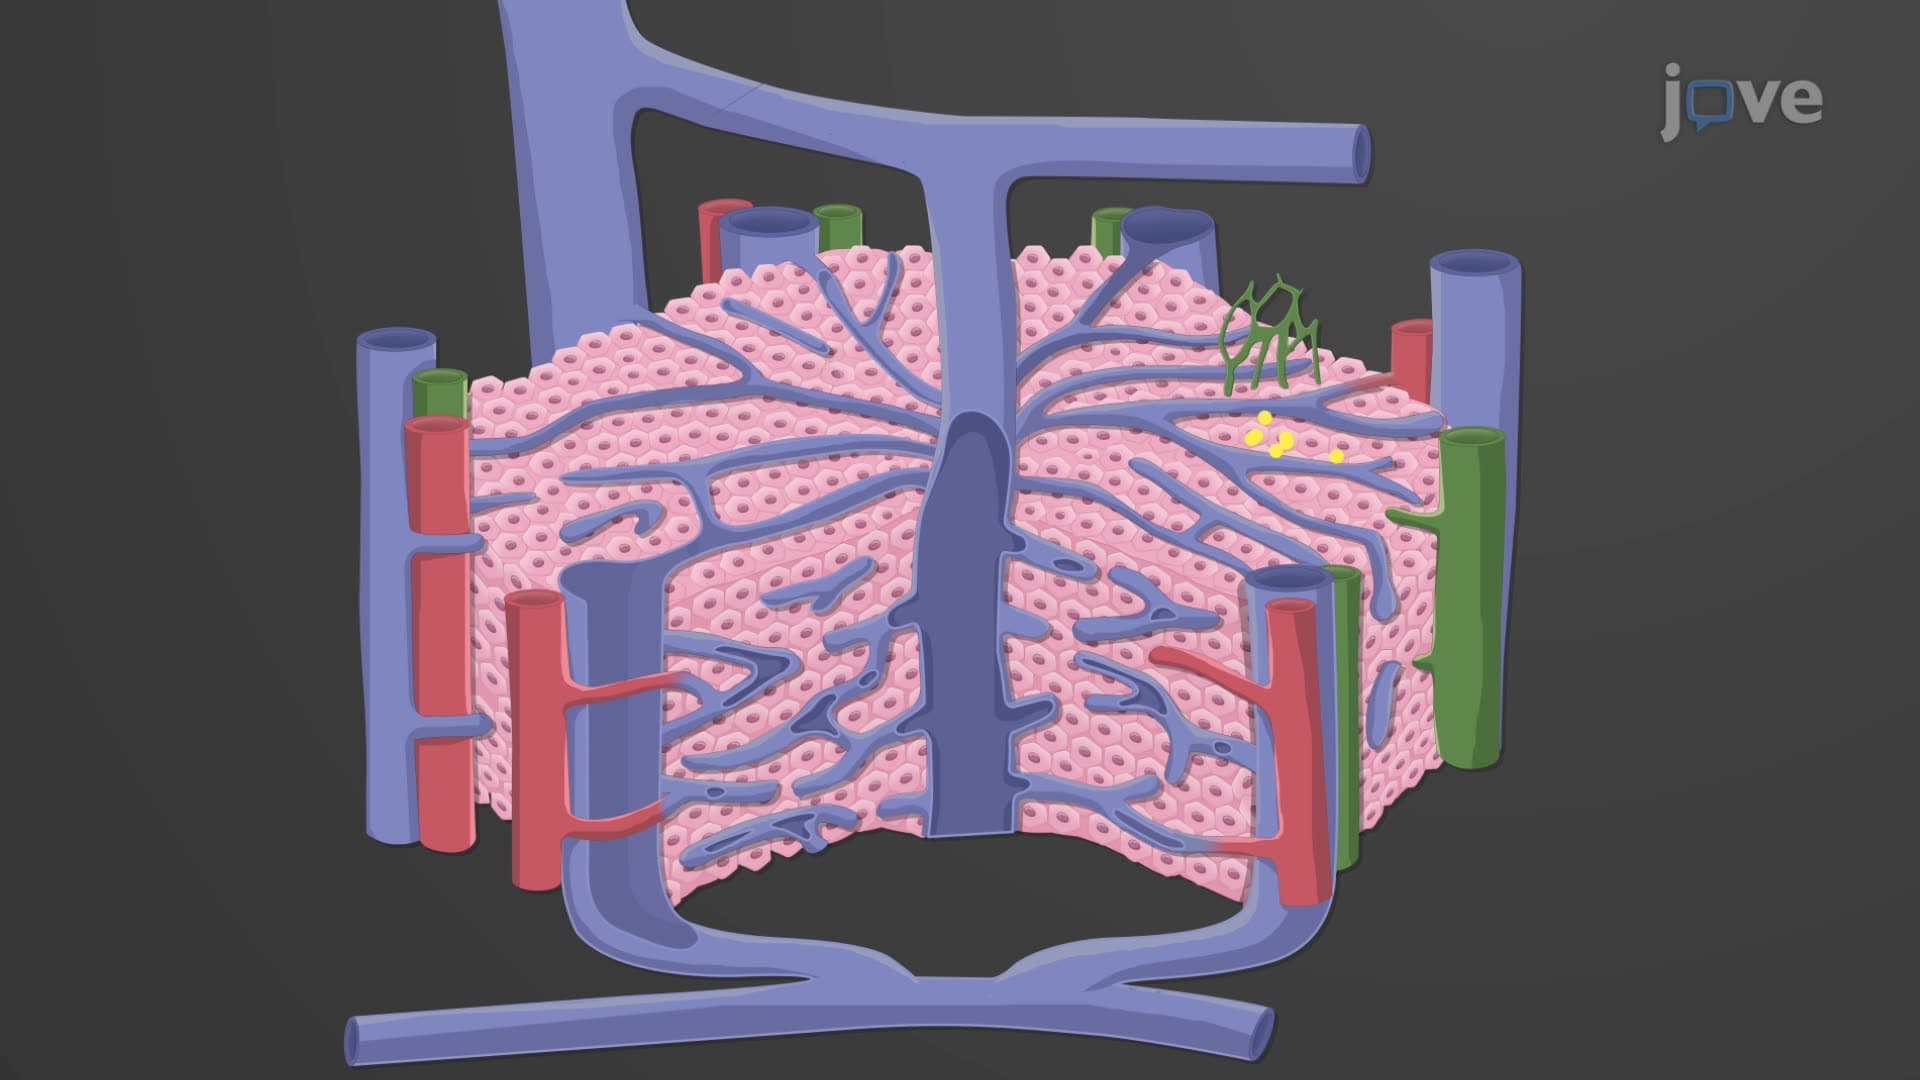 01:27
Liver Histology
Hepatocytes perform a variety of essential functions. They secrete...
 01:30
Liver Physiology
Metabolic Regulation:
The liver is the central organ involved in regulating blood composition. It stabilizes blood glucose levels, maintaining them within the range of 70–110 mg/dL. When these levels drop, the liver breaks down glycogen reserves and releases glucose into the bloodstream. It can...
 01:24
Liver Regeneration
Cells of Liver
The liver comprises four major types of cells— hepatocytes, stellate, Kupffer, and sinusoidal endothelial cells. The hepatocytes are...
 01:17
Gross Anatomy of the Liver
Located under the diaphragm, the liver is almost entirely ensconced within the rib cage, providing it with substantial protection. Except for the superior most bare area, the liver's surface is...